The patient chart — Patient Information
One screen for everything administrative about a patient: open it from the header strip, then work through its tabs — demographics, insurance and eligibility, appointments, questionnaires, prescriptions, forms and letters, prior auth, billing and adjustments, and the outbound communications log.
The patient chart — Patient Information
One screen for everything administrative about a patient: open it from the header strip, then work through its tabs — demographics, insurance and eligibility, appointments, questionnaires, prescriptions, forms and letters, prior auth, billing and adjustments, and the outbound communications log.
One screen for everything administrative about a patient
Coverage, appointments, paperwork, prescriptions, letters, prior authorizations, money, and outbound messages all live on a single screen called Patient Information. It opens from the patient’s name in the chart header strip, and for a physician or an admin it is a full page in its own workspace tab — not a dialog you have to close before you can do anything else.
-
Hover before you click.
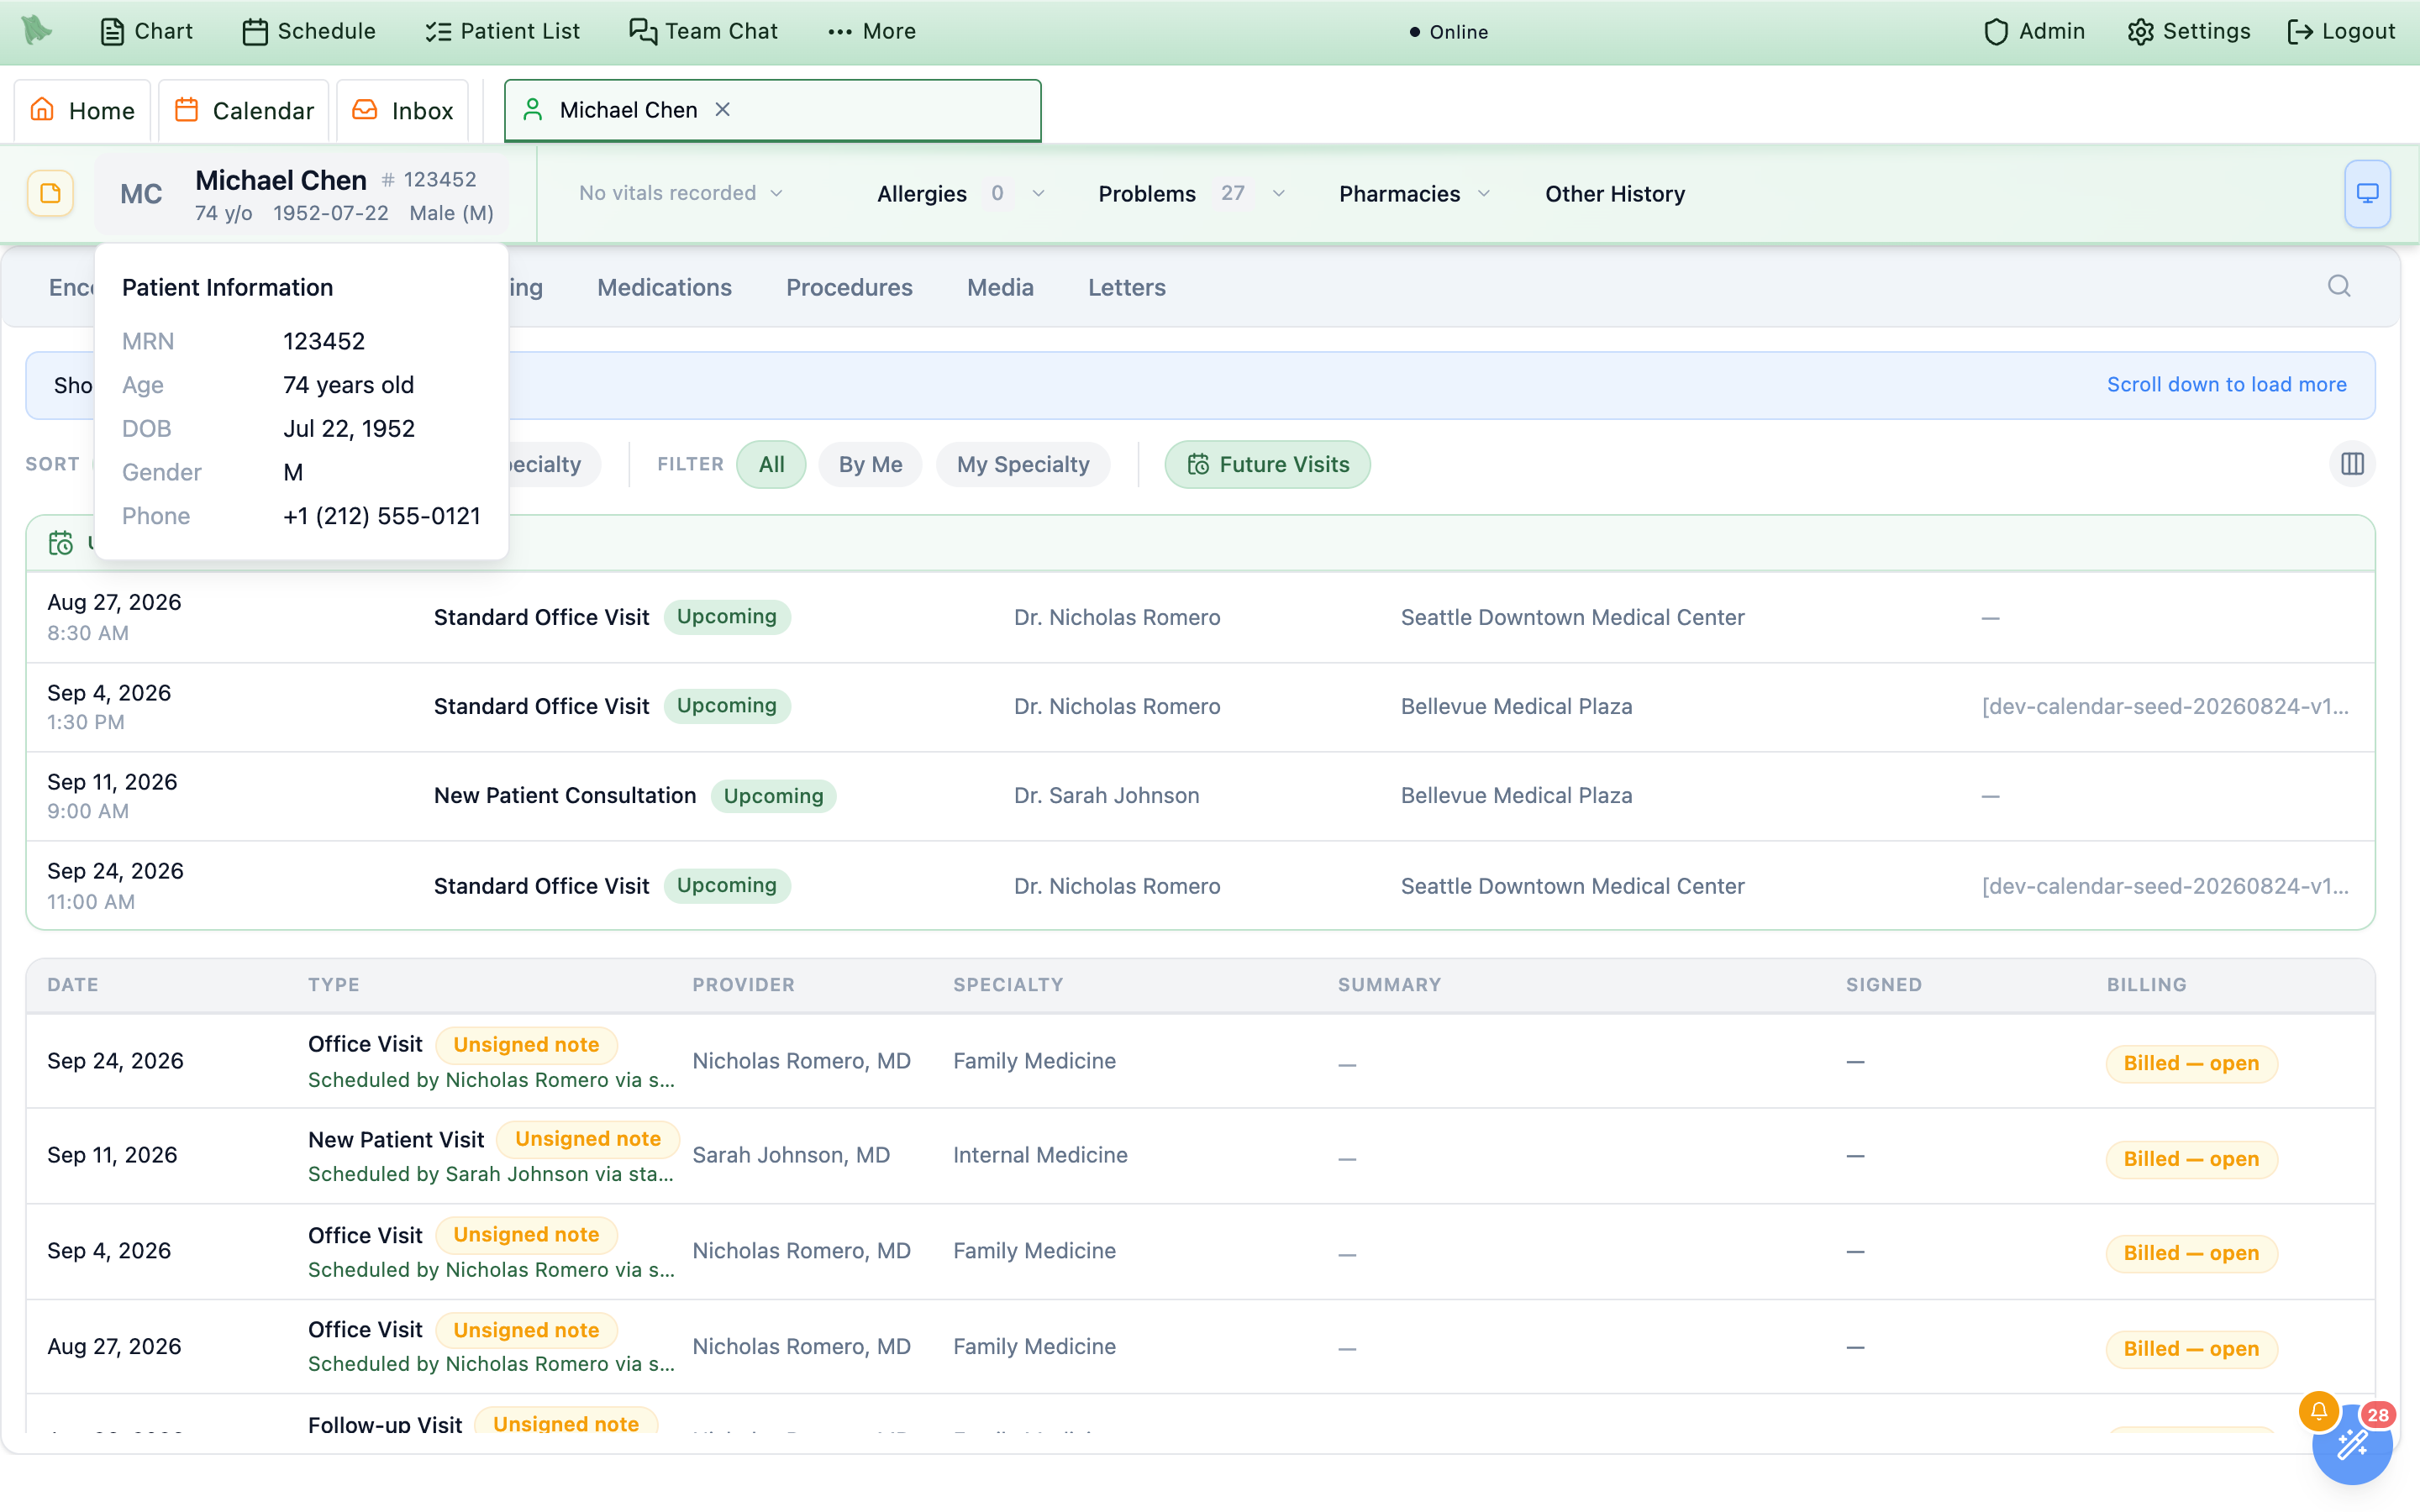
The avatar-and-name block is one button,
Open patient information workspace. Hovering it pops aPatient Informationtooltip withMRN,Age,DOB,Gender,Phone,Secondary, andAddress— rows with nothing on file are left out, so a short tooltip means a thin record. For a quick phone number or date of birth that is usually enough. -
Click to open the workspace.
Physicians and admins land on the page
/dashboard/patient/{id}/info, which registers its own workspace tab titledInfo: Michael Chen. The patient’s chart tab stays open beside it, so you can move between the two without losing either. Staff need a patient-chart permission (patient.vieworpatient.manage) to load that page; without one the same click opens an overlay dialog carrying identical content. There is no keyboard shortcut for it. -
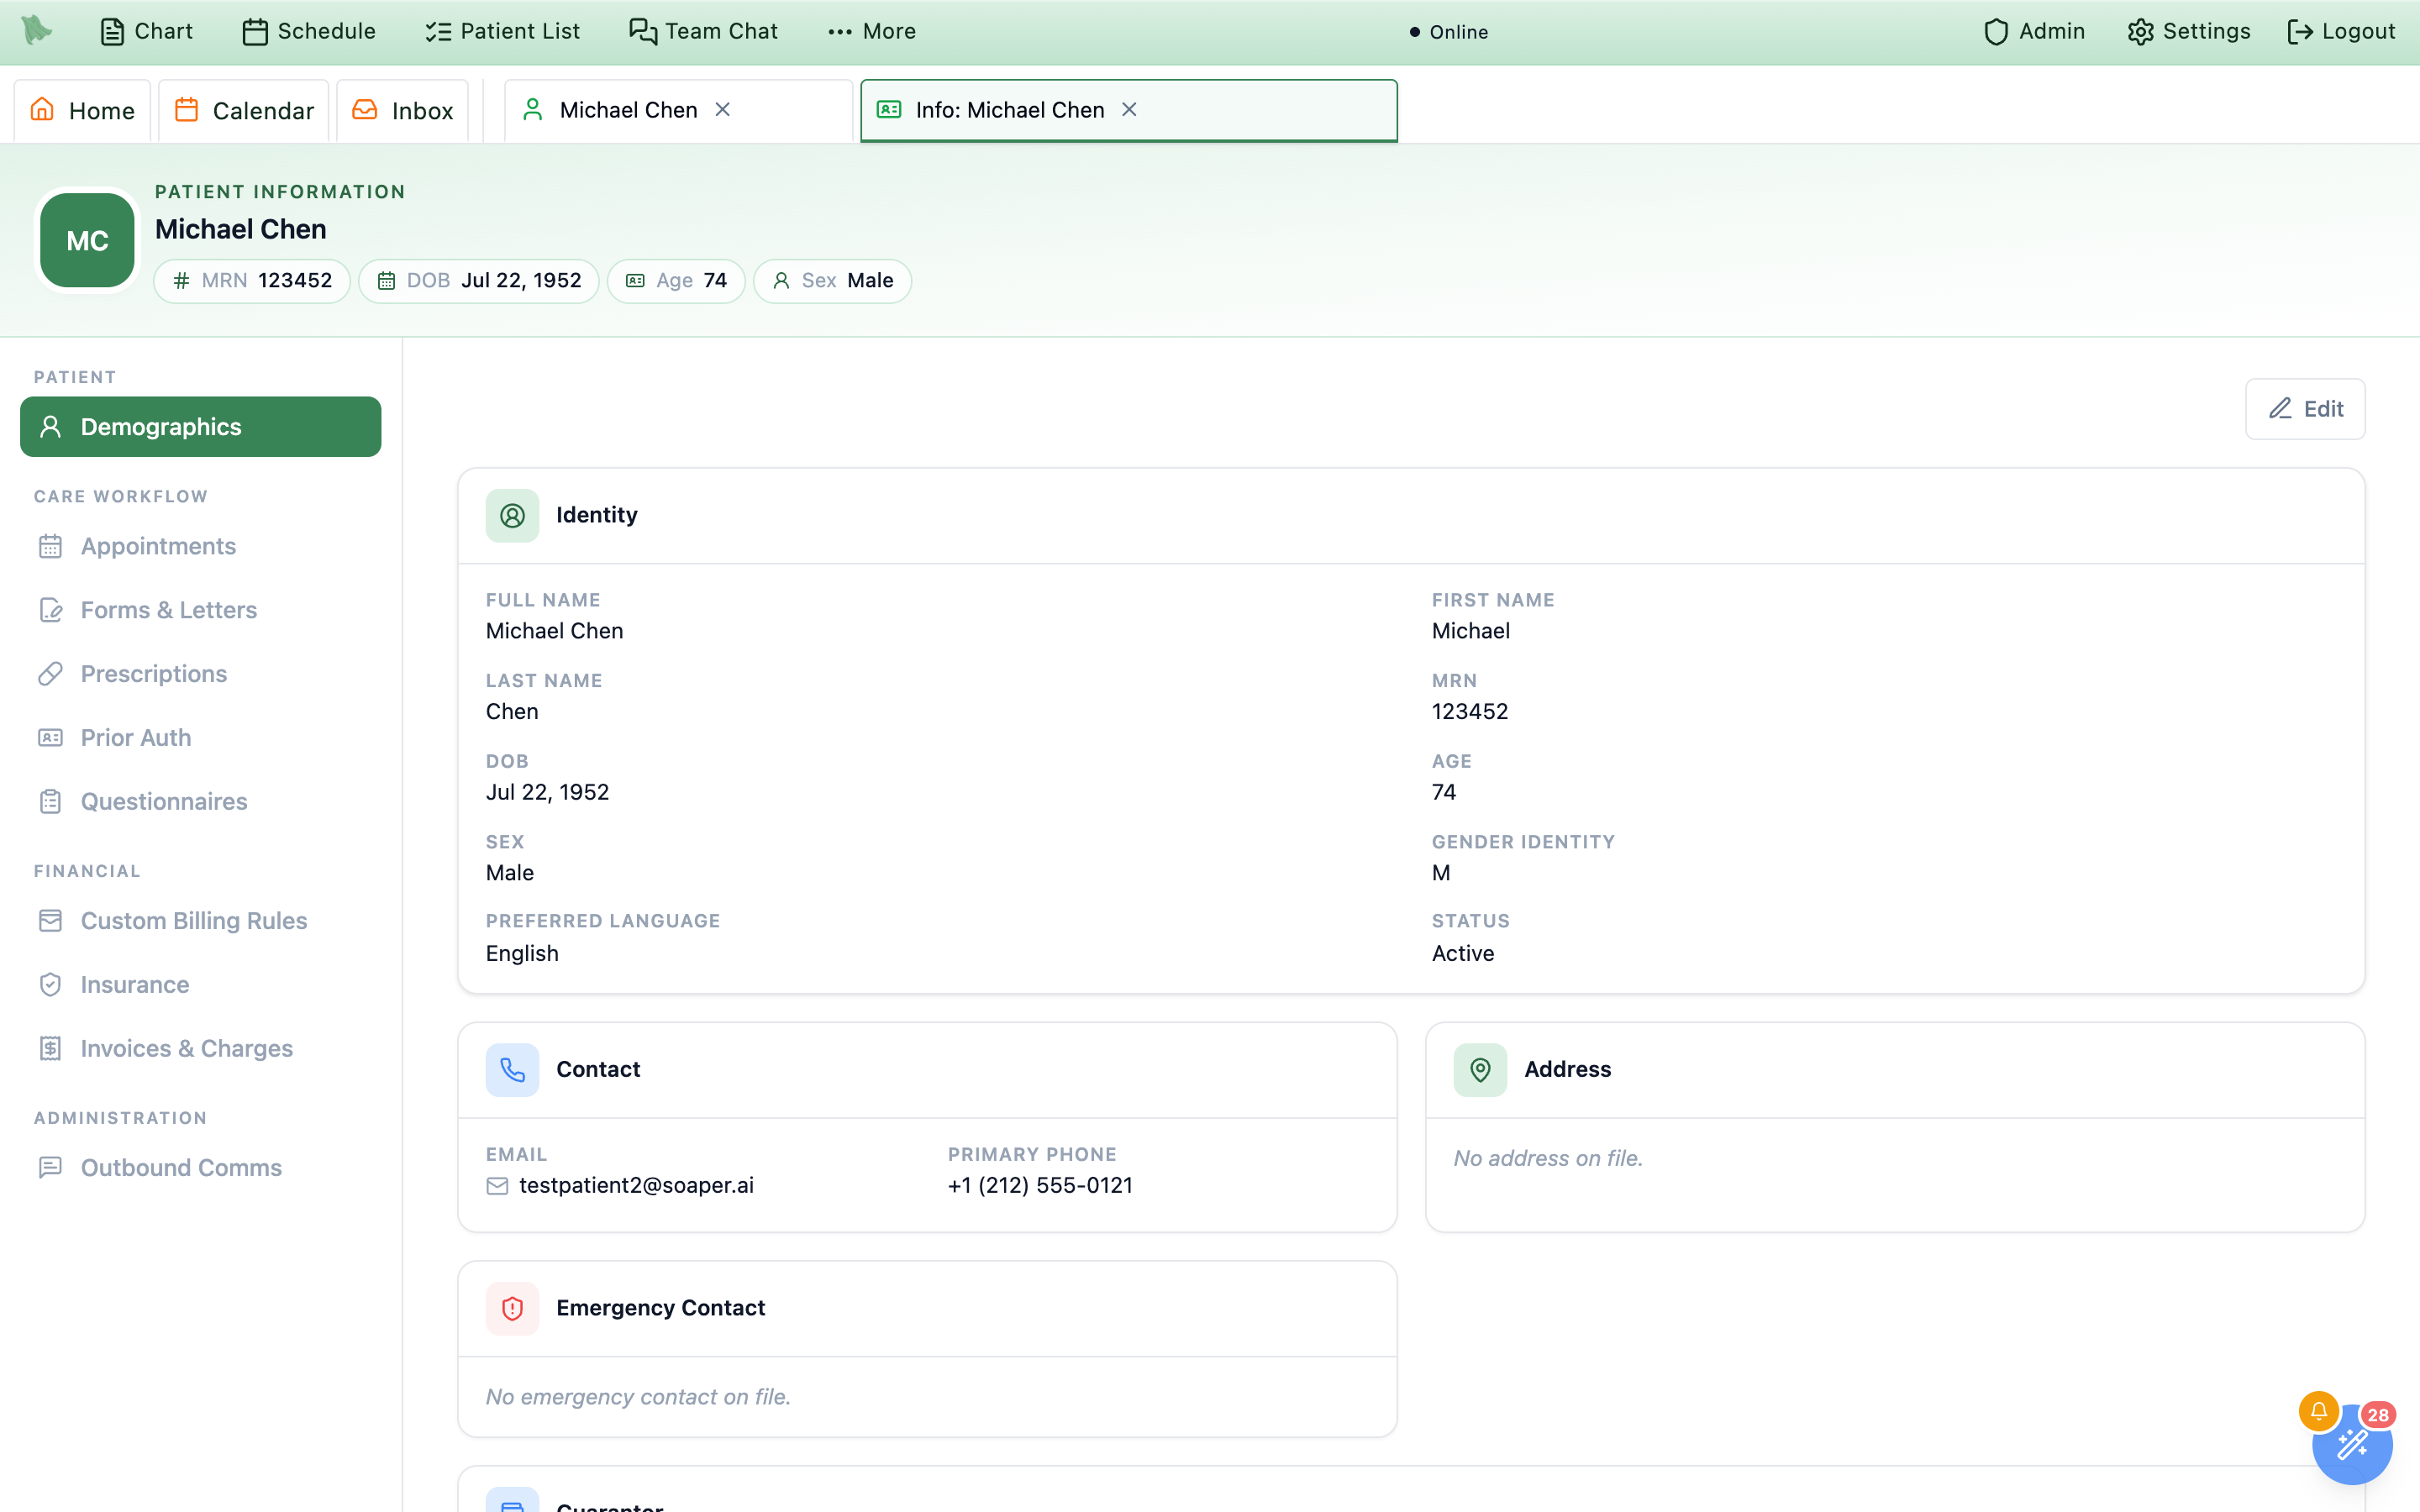
Read the header.
The kicker
PATIENT INFORMATION, the avatar initials, the name, and four chips —MRN,DOB,Age,Sex. A chip is dropped when its field is empty. Save a demographics change and the chips update on the spot, with no reload. -
Navigate with the sidebar.
The page uses a fixed left sidebar under four uppercase headings, in this order:
PATIENT,CARE WORKFLOW,FINANCIAL,ADMINISTRATION. A group is hidden when none of its tabs are available to you; the financial and administration tabs depend on your access. -
Deep-link to a tab with
?section=. The active section is mirrored into the URL, so a link can land on the tab you mean:demographics,more-demographics,implantable-devices,goals-concerns,appointments,chart-sharing,forms-letters,media,prescriptions,prior-auth,questionnaires,custom-billing-rules,insurance,billing-adjustments,health-export,outbound-comms. Onforms-letters,&request=REQ-…also opens one document. Anything else falls back toDemographics, which is also where the screen opens the first time with no?section=, and older links written as?section=billingrewrite themselves tocustom-billing-ruleson arrival. Switching sections replaces the URL rather than pushing it, so Back does not walk you through tabs, and a round trip out to a note or the billing workspace returns you to the section you left. Coming back to a patient’sInfotab later in the same browser tab reopens the section you were last on (for exampleCustom Billing Rules), not Demographics — including a section a link opened, such asCustom Billing Rulesopened from Billing. -
In the overlay dialog it is one tab row.
The dialog shows the same items in the same order, flattened into a single row across the top with no group headings, scrolling sideways when it overflows. Close it with Esc, a backdrop click, or
Close. With unsavedCustom Billing Rulesedits it asks before closing; other open edit forms are not checked, so finish or cancel them before you dismiss it.
Seventeen tabs exist in total. Which you see depends on your role, your permissions, and which optional features your practice has turned on in Admin → Additional Features (four tabs are off until then):
| Tab | Group | ?section= | Who sees it |
|---|---|---|---|
Demographics | Patient | demographics | Everyone. The default tab. Edit shows only for users whose save can succeed. |
Goals & health concerns | Patient | goals-concerns | Only when the practice turns on Goals, health concerns and health status; then physicians, admins, and staff with patient.view. See Goals, health concerns & health status. |
Implantable devices | Patient | implantable-devices | Only when the practice turns on Implantable devices; then physicians, admins, and staff with patient.view. See Implantable devices. |
More demographics | Patient | more-demographics | Only when the practice turns on More demographics; editing needs patient.manage. See More demographics. |
Appointments | Care workflow | appointments | Admins, physicians, or staff with scheduling.view. |
Chart Sharing | Care workflow | chart-sharing | Admins, physicians, or staff with records.share — see Chart Sharing. |
Forms & Letters | Care workflow | forms-letters | Physicians, admins, and staff with patient.view. Starting, releasing and emailing need the Forms & Letters permission (forms_letters.manage); see Forms & Letters. |
Media | Care workflow | media | Physicians and admins; staff with document-viewing, triage, or import permission. |
Prescriptions | Care workflow | prescriptions | Admins, physicians, or staff with prescription.view. |
Prior Auth | Care workflow | prior-auth | Admins, physicians, or staff with billing.prior_auth.manage. |
Homework | Care workflow | — | Everyone. |
Questionnaires | Care workflow | questionnaires | Everyone; sending and rule editing need patient.manage. |
Custom Billing Rules | Financial | custom-billing-rules | Financial access plus admin, or staff with billing.settings.manage. |
Insurance | Financial | insurance | Everyone; the money controls and eligibility tools need financial access. |
Invoices & Charges | Financial | billing-adjustments | Financial access plus admin, or staff with billing.charges.manage, billing.ar.manage, or billing.sensitive. |
Export Health Information | Administration | health-export | Only when the practice turns on Export health information; then physicians, admins, and staff with records.export. See Exporting one patient’s record. |
Outbound Comms | Administration | outbound-comms | Admins, or staff with admin.outbound_comms.view. Never a plain physician. |
A plain physician — not an admin, not a staff profile — therefore works with ten tabs: Demographics, Appointments, Chart Sharing, Forms & Letters, Media, Prescriptions, Prior Auth, Homework, Questionnaires, and Insurance — plus Goals & health concerns, Implantable devices, More demographics and Export Health Information for each of those features the practice has turned on. Within each group the tabs keep the order shown above. Which permission grants what is set per staff member under Staff & assistants. Other places open this same surface as an overlay: the primary insurance cell in a Patient List (it reads the payer name, or Add insurance, and opens onto Insurance), and every patient name in the Billing workspace, which opens it as the Patient billing dialog — billing tabs only (Demographics, Prior Auth, Custom Billing Rules, Insurance, Invoices & Charges, as permissions allow), with an Open chart button for users who can open charts (see the billing workspace). A claim’s Edit demographics quick-fix opens Demographics already in edit mode.
Demographics is the exception — it renders from the record the page already has). Each tab also runs inside its own boundary: if one fails, the sidebar, header, and every other tab keep working, and the failed panel shows {Tab} could not be displayed. with a Retry button — Custom billing rules could not be displayed., Invoices & charges could not be displayed., and so on. While the page itself loads you get a grey skeleton; a patient record that cannot be read at all gives Patient information could not be loaded.Open the patient’s documents without leaving Patient Information
Media under Care workflow opens the same document and image workspace as the chart’s Media tab. Staff need document-viewing, triage, or import access to see it; upload, removal, and insurance-card scanning follow their own permissions. It is not included in the billing-only Patient billing dialog. Eligible payment staff also have Take payment entry points from the patient header and billing information; see Payments & card readers.
Demographics: read the cards, edit the record
Demographics is where Patient Information opens: six read-only cards with a single right-aligned Edit button above them. The edit form replaces those cards in place — it is not a dialog.
-
Read the six cards.
Identity(Full name,First name,Preferred name,Pronounswhen the practice uses them,Middle name,Last name,MRN,DOB,Age,Sex,Gender identity,Marital status,Preferred language,Status, and theSSNrow described below),Contact(Email, both phones, andLast portal login),Address,Emergency Contact,Parent / Guardian, andGuarantor. A field with no value is dropped rather than shown blank, and phone numbers are reformatted for reading as(502) 555-0134. -
Read the empty states carefully.
AddressandEmergency Contactkeep their headings when empty and say so —No address on file.andNo emergency contact on file.Parent / GuardianandGuarantorhave no such hint, so an entirely empty one disappears from the page. A missing card means nothing has been recorded, not that something failed to load. -
Know two vocabularies.
Statusis one ofActive,Inactive,Prospective,Discharged,Transferred out, orDeceased.Marital statusis one ofSingle,Married,Divorced,Widowed,Separated,Annulled,Domestic partner,Unmarried, orUnknown. -
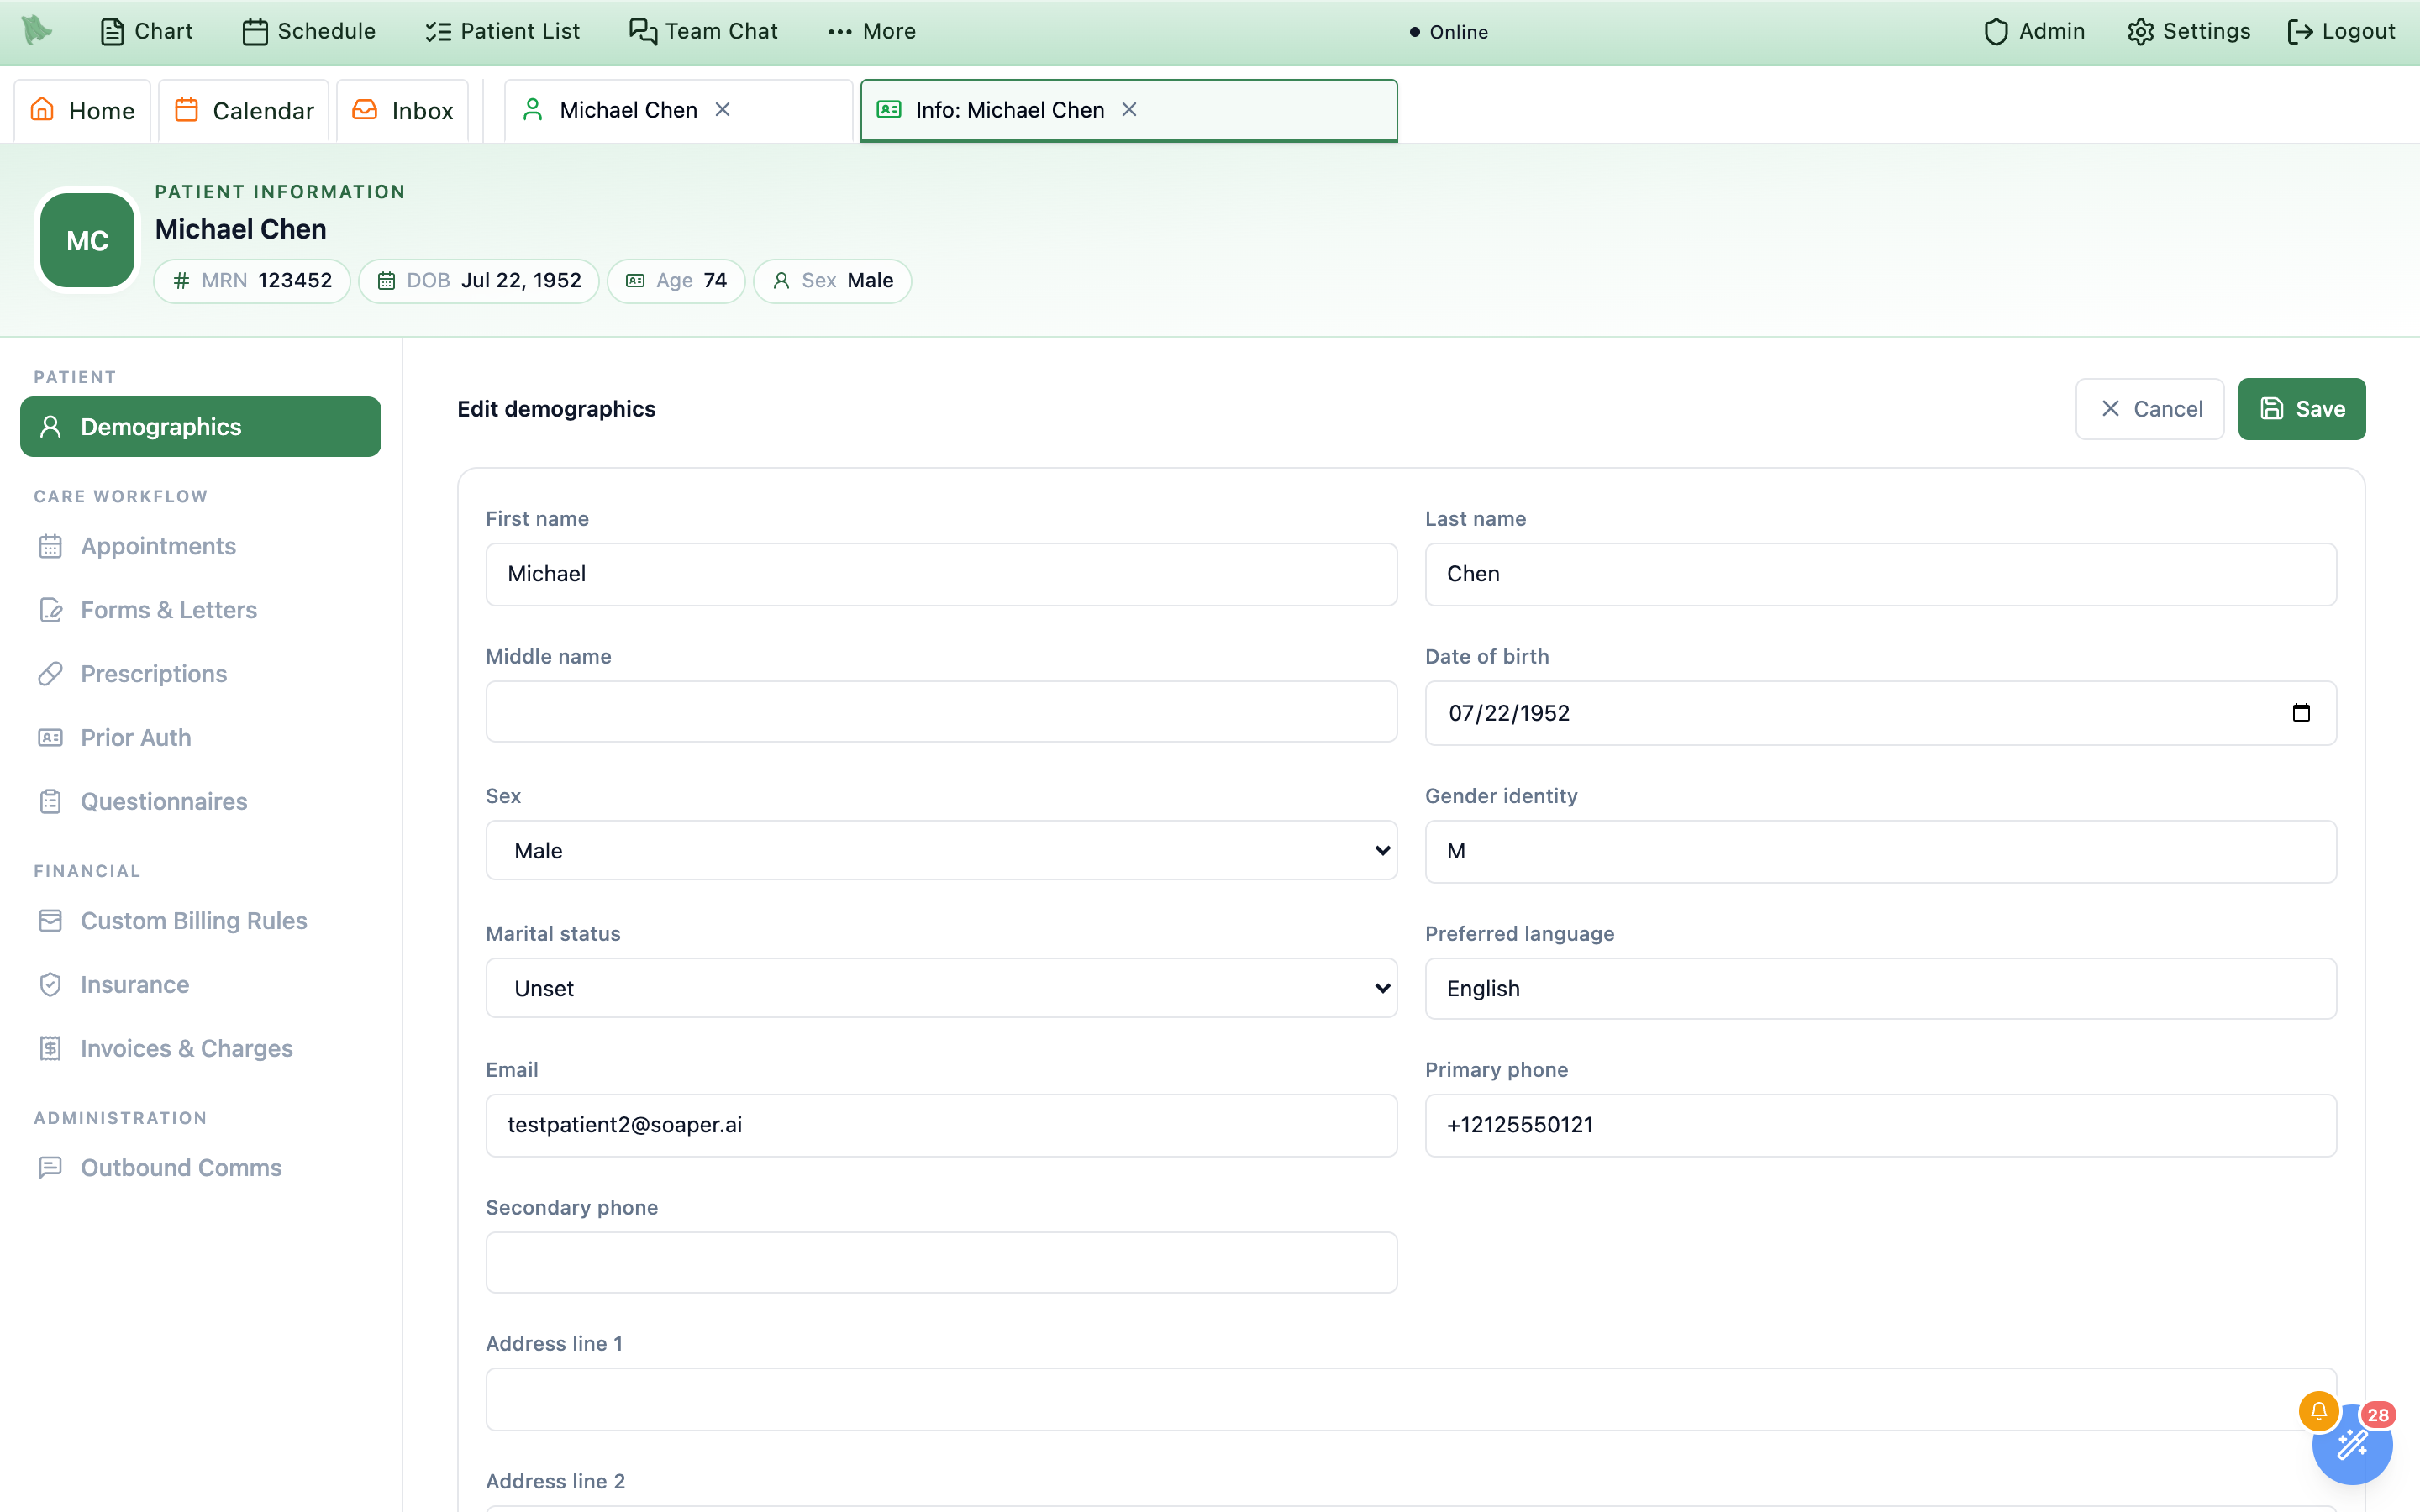
Click
Editto open the form. The button briefly readsOpening…while Hero fetches the latest copy of the record, so you never edit (or save over) an out-of-date one. The heading changes toEdit demographicswithCancelandSaveat the top right. Fields run in order:First name,Preferred name,Pronouns(only with thePatient pronounsfeature on),Last name,Middle name,Date of birth,Sex,Gender identity,Marital status,Preferred language,Email,Primary phone,Secondary phone,Address line 1,Address line 2,City,State,ZIP,Emergency contact,Emergency relationship,Emergency phone, then aParent / Guardianblock (“For a patient under 18 this is where clinic email, texts and portal access go.”) withParent first name,Parent last name,Parent email,Parent phone,Parent date of birthandParent sex. When a minor has no parent or guardian email, an amber note warns that the patient will not receive appointment reminders, forms or portal invitations until one is added. Nothing is required, and the phone fields show the raw stored number rather than the formatted one. The Social Security number is not edited here; it has its own row (below). -
Two fields are validated.
Statemust be a two-letter US state, territory, or military code; case does not matter (orsaves asOR), and anything else is flagged withUse a valid 2-letter US state or territory code.ZIPmust total 5 or 9 digits, elseZIP code must be 5 digits (12345) or 9 digits (12345-6789).— a valid nine-digit entry is tidied on save, so410561234is stored as41056-1234. Both may be left empty. Nothing else is checked: email, phone, and date formats are accepted as typed. -
Save, or back out.
Savebriefly readsSaving...with both buttons disabled, then closes back to the cards. There is no success toast — the confirmation is that the cards and the header chips now show the new values (the one exception, a corrected email that cancelled a pending portal invitation, is below). A rejected change keeps you in the form with the server’s message in a red banner.Cancelrestores the stored values immediately, with no confirmation prompt and no recovery.
State and ZIP are validated before it saves.Who can edit
Editshows only for users whose save can succeed: physicians, admins, and staff withpatient.manageorbilling.claims.manage. Other staff (a referral coordinator, for example) read the cards without anEditbutton.- Physicians and organization admins in the selected practice can change anything.
- Staff need
patient.managefor a full edit. - Staff with only
billing.claims.managemay change the address and guarantor blocks; editing anything else is refused with a message naming the field they touched.
What changes downstream
- The header chips on this screen refresh immediately.
- The mailing address is the address on the claim — an incomplete one blocks submission (see the claims pipeline).
- It is also reused as the policyholder address on a dependent policy whose
Same address as patientbox is checked (next section). - Name and date of birth flow into scheduling, the patient portal, and every eligibility check — which match the payer’s records exactly.
- A changed
Emailcancels the patient’s pending portal invitation to the old address (next callout).
Email cancels it, so its email and text links stop working, and nothing new is sent on its own. Above the cards Hero says Saved. The earlier invite was cancelled. Send a new one. Click Send Invitation to email a new invitation to the corrected address; Hero confirms Portal invitation sent to …. If the send is refused, the reason shows in a red banner and the button stays. The button needs patient-management permission, like any portal invitation.Edit demographics quick-fix on a claim’s readiness issues, and on Correct & refile, opens this tab already in edit mode, and any patient name in Billing opens it in the Patient billing dialog (see the claims pipeline). A staff member whose only relevant grant is the claims permission sees a grey note — Billing role: you can update the patient’s address here. Other demographics need patient-management permission. — and just five fields: Address line 1, Address line 2, City, State, ZIP. Whatever they save lands here in the chart.Save. A mistyped date of birth will start failing eligibility checks at the payer. Read the form back before you save it.The Social Security number row
The Identity card has an SSN row. Some states (Kentucky, for example) need the number for the prescription-monitoring check on controlled-substance prescriptions, and some insurers ask for it to verify coverage. The number is never shown in full by default and never appears in the edit form.
- What it shows.
•••-••-1234(the last four digits) when a number is on file, orNot on file. Show/Hide.Showdisplays the whole number. It hides itself again after 30 seconds, when you switch to another browser tab, or when you leave the tab or patient. EveryShowis recorded in the audit log. Viewing many numbers in a short time is paused for a few minutes: “Too many full numbers viewed recently. Try again in a few minutes.”Add/Replace. Opens aSocial Security number(orNew Social Security number) box that formats as you type (###-##-####).Saveneeds all nine digits (“Enter all nine digits of the Social Security number.”). There is no way to remove a number once saved, only to replace it.
| Who | Sees the last four | Show the whole number | Add / Replace |
|---|---|---|---|
| Practice administrators and owners | Yes | Yes | Yes |
| Physicians | Yes | No, unless also given the sensitive-identifiers permission | Yes |
Staff with patient.sensitive (“Merge, archive, manage portal linkage, and update sensitive patient identifiers.”; the Office Manager preset has it) | Yes | Yes | Yes |
Staff with patient.view or patient.manage only | Yes | No | No |
| Other staff, and anyone in the billing-only Patient billing dialog | The row is not shown. | ||
Patients can also type their own number in the portal, during profile setup, when the practice turns on the Social Security Number card in Admin → Patient Portal Configuration → Features (under Orientation intake; off by default). They can skip the step, and once a number is on file a patient cannot change it from the portal; staff replace it here. The staff row above works whether or not that portal card is on.
Scan a photo ID and add a patient photo
Scan a patient’s driver’s license or other photo ID from the chart or the registration form. Hero reads it, you choose what to copy into the chart, and the ID is filed in the chart’s documents. The patient’s photo, cropped from the ID or taken with a camera, shows at the top of the chart in place of their initials.
Turn it on
A practice administrator, or staff allowed to manage additional features, opens Admin → Specialties & chart sections, switches on Photo IDs and patient photos under Extra chart fields, and clicks Save. It is off by default; while it is off the buttons below don’t appear and charts show initials. Scanning, filing and changing the photo need permission to manage patients (physicians and administrators always can).
Scan a patient’s photo ID
- Open the patient’s
Patient Info → Demographicsand clickScan photo ID. -
Use one of three ways.
Upload a scan or photo: theFront of ID, and theBack of ID (optional), or a scanner’s PDF (a two-page PDF is read as front, then back); thenRead ID.Use this computer's camera: hold the ID up to the camera and take the photo.Take the photos with a phone: scan the QR code with a phone and take the photos there; the link is private, works once, and expires after 15 minutes. -
Choose what to copy.
Hero reads the name, date of birth, sex, address and expiration date and shows them beside the chart’s values. Every field starts on
Keep current; clickUse IDfor each value you want (orUse all ID values). The ID number is never copied, and an X sex marker is not copied because the chart records sex assigned at birth. -
Check the warnings.
Hero warns when the ID has expired (This ID expired on …) or when the name or date of birth doesn’t match the chart. After a mismatch, make sure it is the right patient and tick
I checked that this ID belongs to this patient. -
Optional: use the ID’s picture as the patient photo.
Keep
Use the photo on this ID as the patient's pictureticked and drag the square over the face. -
Click
File photo ID. The values you chose are saved to Demographics, and the ID is filed in the chart’s documents as a photo ID. Earlier photo IDs are kept. If the values were saved but filing failed,Try filing againfiles it without saving the values twice.
If the ID can’t be read, you can still file it and type any changes in Demographics.
Register a new patient from their ID
In Register New Patient (Admin → Patient Registration → Add Patient), click Scan photo ID at the top of Identity, choose the values to fill in, and finish the form. When you create the patient, the ID is filed on the new chart. If filing fails, the patient is still created; click Try again. Closing the form without creating the patient discards the scan.
The patient photo
The photo shows at the top of the chart and in Patient Information in place of the initials. In Demographics, Patient photo offers Take photo, Upload photo, Use a photo ID on file and Remove photo. Removing it brings back the initials; photo IDs stay in the chart’s documents. Staff who can see only billing see the initials.
Remove photo.
Add or change a patient’s guarantor (the person responsible for the bill)
To add a guarantor — a parent, spouse or legal guardian who pays the patient’s bill — edit the patient’s demographics. The guarantor is part of the Edit demographics form on the Demographics tab of Patient Information, and shows afterwards on its own Guarantor card.
- Open the patient’s Patient Information and stay on
Demographics. ClickEdit. - Scroll to
Guarantor(“The person responsible for this patient’s bill. Choose Self when the patient pays.”) and pick theGuarantor relationship:Self,Parent,Spouse,Legal guardianorOther. - For anyone but
Self, fill in the guarantor’s details:Guarantor first name,Guarantor last name,Guarantor date of birth,Guarantor phone,Guarantor emailand the address.Use the patient’s addresscopies the patient’s address into the guarantor address fields. - Optional: send statements to the guarantor. For an adult patient, tick
Send statements to the guarantorso emailed and printed statements and payment reminders go to the guarantor instead of the patient. Because a statement shows the patient’s visits and balance, recordHow the patient agreed(Told us (verbal),Signed form (written)orElectronically) andDate the patient agreed. For a patient under 18, statements already go to the parent or guardian. - Click
Save.
Where to find, enter or ask for a patient’s Social Security number (SSN)
A patient’s Social Security number is on the SSN row of the Identity card, on the Demographics tab of Patient Information. It is not part of the Edit demographics form or the Register New Patient form.
- Open Patient Information →
Demographicsand findSSNon theIdentitycard. It shows the last four digits (•••-••-1234) orNot on file. - To enter it, click
Add(orReplacewhen one is on file), type all nine digits and clickSave. - To read the whole number, click
Show. Each view is recorded in the audit log, and the number hides itself again after 30 seconds. - To ask the patient for it, turn on the
Social Security Numbercard inAdmin → Patient Portal Configuration → Features(under Orientation intake). Patients are then asked for it when they set up their portal profile and can skip it. Otherwise ask them directly and enter it yourself.
Who can see, show and enter the number is set by role; see the table in The Social Security number row.
Add more contacts to a patient: another parent, a grandparent, a caregiver
The chart has one emergency contact, one parent or guardian and one guarantor. To keep more people on file (a teen’s other parent, a grandparent, a coach or caregiver), with several phone numbers and emails each, use Additional contacts at the bottom of Patient Info → Demographics.
Turn it on
A practice administrator, or staff allowed to manage additional features, opens Admin → Specialties & chart sections, switches on Several contacts per patient under Extra chart fields, and clicks Save. It is off by default.
Add, edit or remove a contact
- Open the patient’s
Patient Info → Demographicsand scroll toAdditional contacts, below the guarantor. With none on file it readsNo additional contacts on file. - Click
Add contact. EnterFirst name,Middle name,Last name(a first or last name is required),Relationship to the patient(type your own or pick a suggestion such asGrandparent,CaregiverorLegal guardian) andDate of birth. - Mark what the contact is for, if anything:
Emergency contact,Parent or guardian,Responsible for billing. - Add phones and emails.
Add phoneandAdd emailadd more rows, each with a label (for exampleMobileorPersonal). Phone numbers need an area code (10 digits). Add anyNotes. - Click
Save contact.
Each contact shows its relationship, tags for Emergency contact, Parent/guardian, Responsible for billing or Imported, every phone and email with its label, the date of birth and notes. Use the pencil to edit a contact, the arrows to move it up or down the list, and the remove button to delete it; Hero asks “Remove {name} from this patient’s contacts?” with Keep and Remove. Adding, editing and removing need permission to manage patients. Staff who see only billing don’t see the list.
Emergency Contact, Parent / Guardian and guarantor, even when an additional contact is marked as a parent or responsible for billing. To change who gets those, edit the demographics (Demographics). Charts imported from another system may arrive with their contacts already in the list, tagged Imported.Coverage, eligibility checks, and how this patient is billed
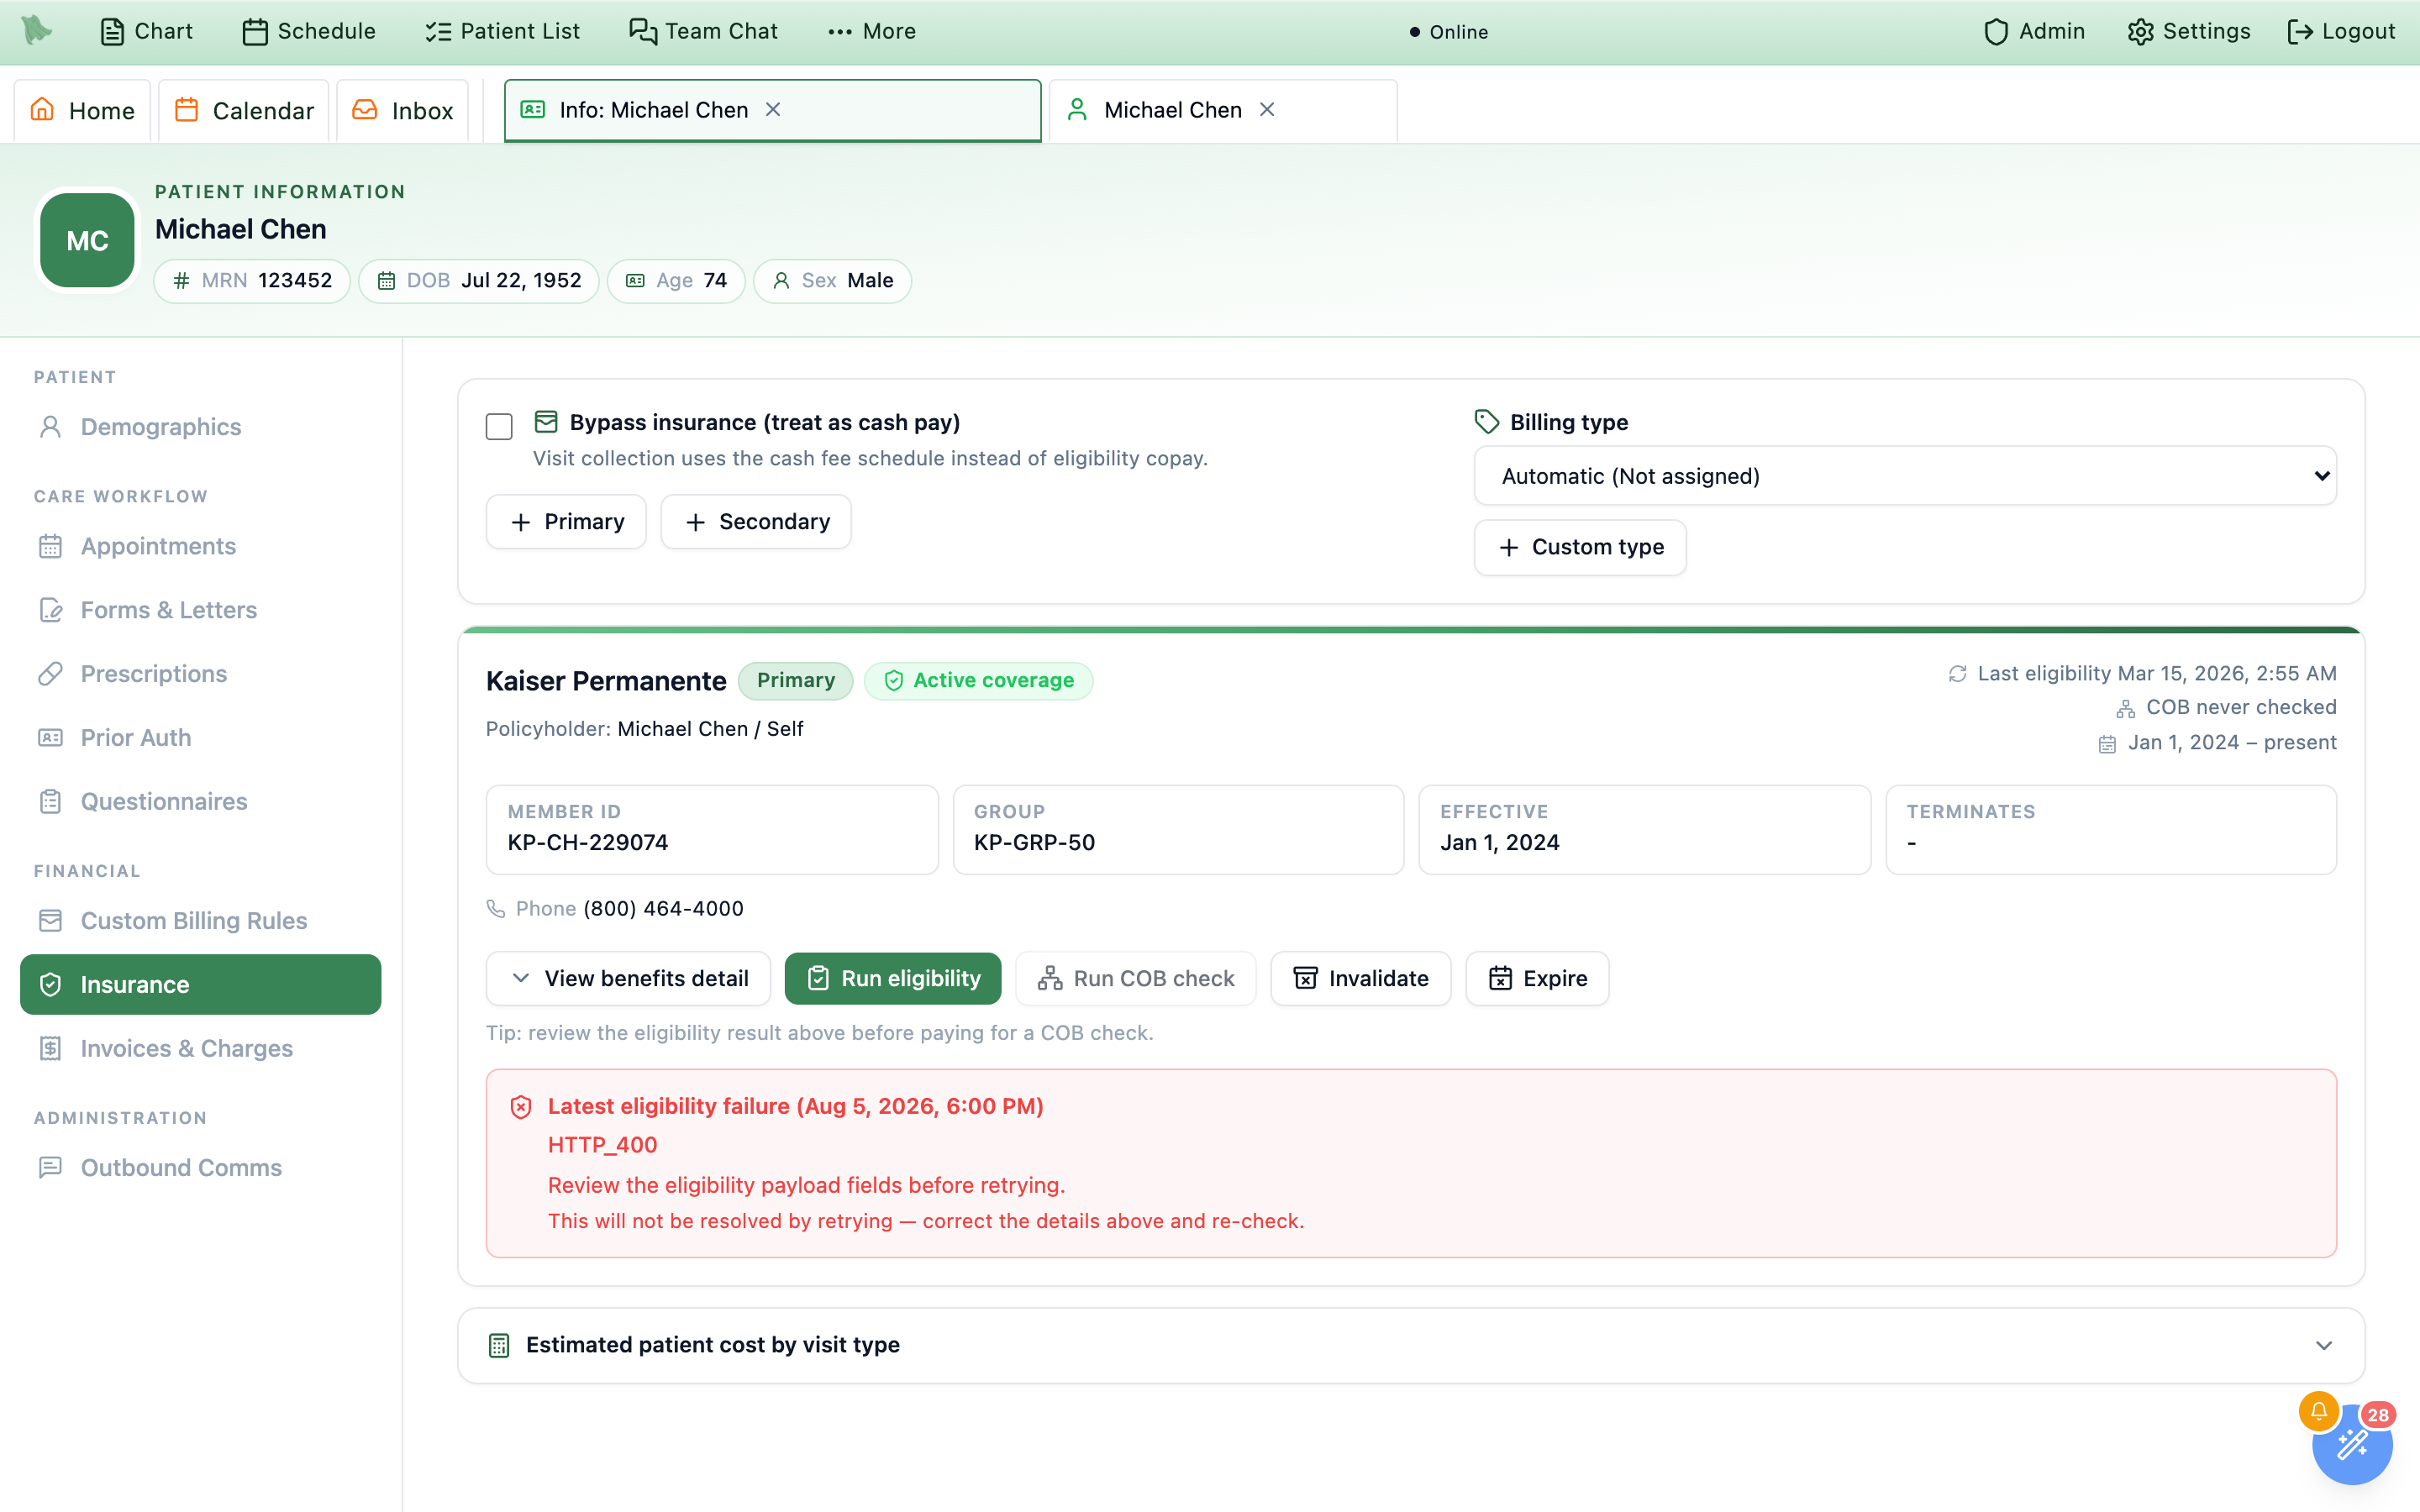
The Insurance tab holds the patient’s policies, the electronic checks you run against them, and the two settings that decide how their visits are billed. It reads top to bottom: the controls card, a card per policy, then a collapsed Estimated patient cost by visit type panel at the very bottom.
-
Start at the controls card.
Bypass insurance (treat as cash pay)is a checkbox, captionedOverride the billing classification and use cash pricing for this patient.(when the patient’s billing type is already Cash Pay, the caption says insurance is bypassed by that classification instead). Beside it,Billing typealways offersAutomatic (based on current coverage)first, then your practice’s own types, and+ Custom typecreates and assigns a new one in a single step. A failed change showsUnable to update billing type. -
Add a policy.
+ Primaryand+ Secondaryopen an inline form headedAdd primary insuranceorAdd additional insurance; once the patient has two active policies the second button reads+ Tertiary / additional coverage.Set coverage order, next to them, lets you put the active policies in the order you verified (Up/Down, then a requiredReason and verification sourceandSave coverage order); it changes which payer future claims go to, and claims already sent keep their payer.Payeris a typeahead (Payer name or Payer ID from the card) that searches the clearinghouse directory after two characters. Abbreviations and card spellings work (BCBS,BCBSTX,UHC,BlueCross BlueShield of Texas, words in any order), and thePayer IDprinted on the card gives an exact match. Each result shows its payer ID, analso known asline when it matched through an alternate name, andEligibility,Claims, andERAchips for what that payer supports; a result markedNot available for electronic eligibility or claimscomes from an older payer list and will fail every check, so pick the clearinghouse entry instead (Medicare Advantage plans usually file under a separateMedicare Advantagepayer). You must pick a result; typing the name and moving on fails withSelect a payer.Member IDis required,Groupoptional (don’t repeat the member ID there; a claim whose member ID is its group number is held), andRelationshipdefaults toSelf. Anything else reveals the policyholder’s name and date of birth plus aSame address as patientcheckbox, ticked by default — leave it to put the demographics address on claims. To have the patient photograph their card instead, the Insurance card requests panel’sRequest insurance cardmakes a short-lived link and QR code the patient opens on their phone; cards read from uploaded documents appear in the same panel. Review the scanned details before saving a policy. -
Read the policy card.
The payer name heads the card with a
Primarybadge and a status chip. Under it,Files to: {payer}withID {payer ID}andEligibility/Claims/ERAchips names the clearinghouse payer the policy actually uses; an amber line instead means the policy cannot be used electronically — either{payer} isn’t set up for electronic eligibility or claimsorNo claims payer selected— and tells you to openEdit policy(a policy linked only to an Office Ally payer is fine at a practice whose claims go through Office Ally SFTP, as long as Hero can match it to one Office Ally claims payer: the line then readsFiles to:with that claims payer ID, which can differ from the eligibility ID), whoseClaims payersection shows the current payer and aChange payersearch; picking a replacement and saving swaps the payer in place and re-checks eligibility (a policy that already has claims or a successful check refuses the swap and asks for a new policy instead). The right column carriesLast eligibility {date}orEligibility never checked,Last COB {date}orCOB never checked, and the coverage date range (a missing end date readspresent). Below sit theMEMBER ID,GROUP,EFFECTIVE, andTERMINATEStiles. -
Use the action row.
View benefits detailexpands the coverage and benefits panel;Policyholder details, on a dependent policy, fills in missing subscriber identity only, since stored fields lock once billing activity exists.Make primarypromotes a secondary policy;Invalidateis for one entered in error andExpirefor coverage that has ended, both confirmed, withExpirerequiring aCoverage end date;Reactivatereturns a historical policy to service with no confirmation. There is no delete — retired policies collapse intoInactive and expired insurance (N)so eligibility, claims, and billing history keep their references. -
Run eligibility — free, and the one to run first.
Run eligibilityis enabled only on an active policy. The result either lands at once or queues, and the notice under the buttons says which:Eligibility check complete.,Eligibility check failed: {reason}, orEligibility check queued. Results may take a little longer; keep this detail open or retry shortly.A stored failure about the patient’s coverage stays on the card underLatest eligibility failurewith the reason in plain words, the recommended action, and a line telling you whether retrying can help. When the insurer only refused the check’s date, there is no red box: a blue notice,The insurer didn't check that date, says it isn’t a problem with the member ID and that Hero re-checks with today’s date (see Eligibility history & payers, which also covers the full list of every check run on a policy). A failure caused by your practice’s setup shows instead as an amber notice — “Eligibility checks aren’t set up · No eligibility clearinghouse is connected for this payer.” (or, for a failure left over from Office Ally, “Office Ally no longer checks eligibility”) — withOpen External Providersfor admins, or “Ask your practice administrator to set this up in External Providers.” for everyone else; retrying won’t fix it. -
Run a COB check when you suspect a second plan.
Run COB checkasks the clearinghouse which plans the patient really has and which one pays first. It costs money — read the callout below before you click. It also needs the COB permission: without it the button is disabled and readsAsk a billing manager or office manager to run a COB check.When the check can’t run, the disabled button says why: “Other-coverage checks aren’t set up for your practice yet. A practice administrator can connect them in Admin → External Providers.”, “Other-coverage checks can’t run while your practice’s clearinghouse connection is in test mode. They work once the connection is live.”, “Other-coverage checks are turned off for your practice. A practice administrator can turn them on in Admin → External Providers.”, “This payer doesn’t accept other-coverage checks.”, or “Other-coverage checks don’t work for traditional Medicare.” After you run one, the card says COB check complete., COB check failed: {reason}, or, after about 30 seconds, “COB check is still running. The result appears here when the clearinghouse answers.”; it keeps refreshing on its own, and one the clearinghouse never answers ends with “The clearinghouse hasn’t answered this COB check. Run it again later.” Once a result lands,View benefits detailshows what came back — eitherNo additional coverage found.or a notice naming the other payers over a card each, carrying the payer ID, the sequence the payer itself reported (Primary Payer,Secondary Payer,Tertiary Payer), and the coordination effective date. -
Apply the coverage order the check proposes.
This is the point of paying for the check. When other coverage turns up,
Review coverage orderopens a dialog headedOther coverage found. It states the finding in one sentence ({payer} pays second.), lists everything the payer reported underReported by the payer— each one marked eitherOn fileagainst a policy you already hold orNot on this patient’s chart— and proposes aNew coverage order: one row per active policy, rankedPrimary,Secondary,Tertiary, each showing where it moved from (↑ was Secondary,↓ was Primary, orUnchanged) and the reason it landed there. Drag a row, nudge it with the arrows, or take the suggestion back withReset to COB suggestion.Apply coverage orderwrites the whole order in one step;Keep current orderchanges nothing. A reported payer that is not on the chart gets its own amber callout with anAdd policyshortcut that opens the add form with the payer name already filled in. -
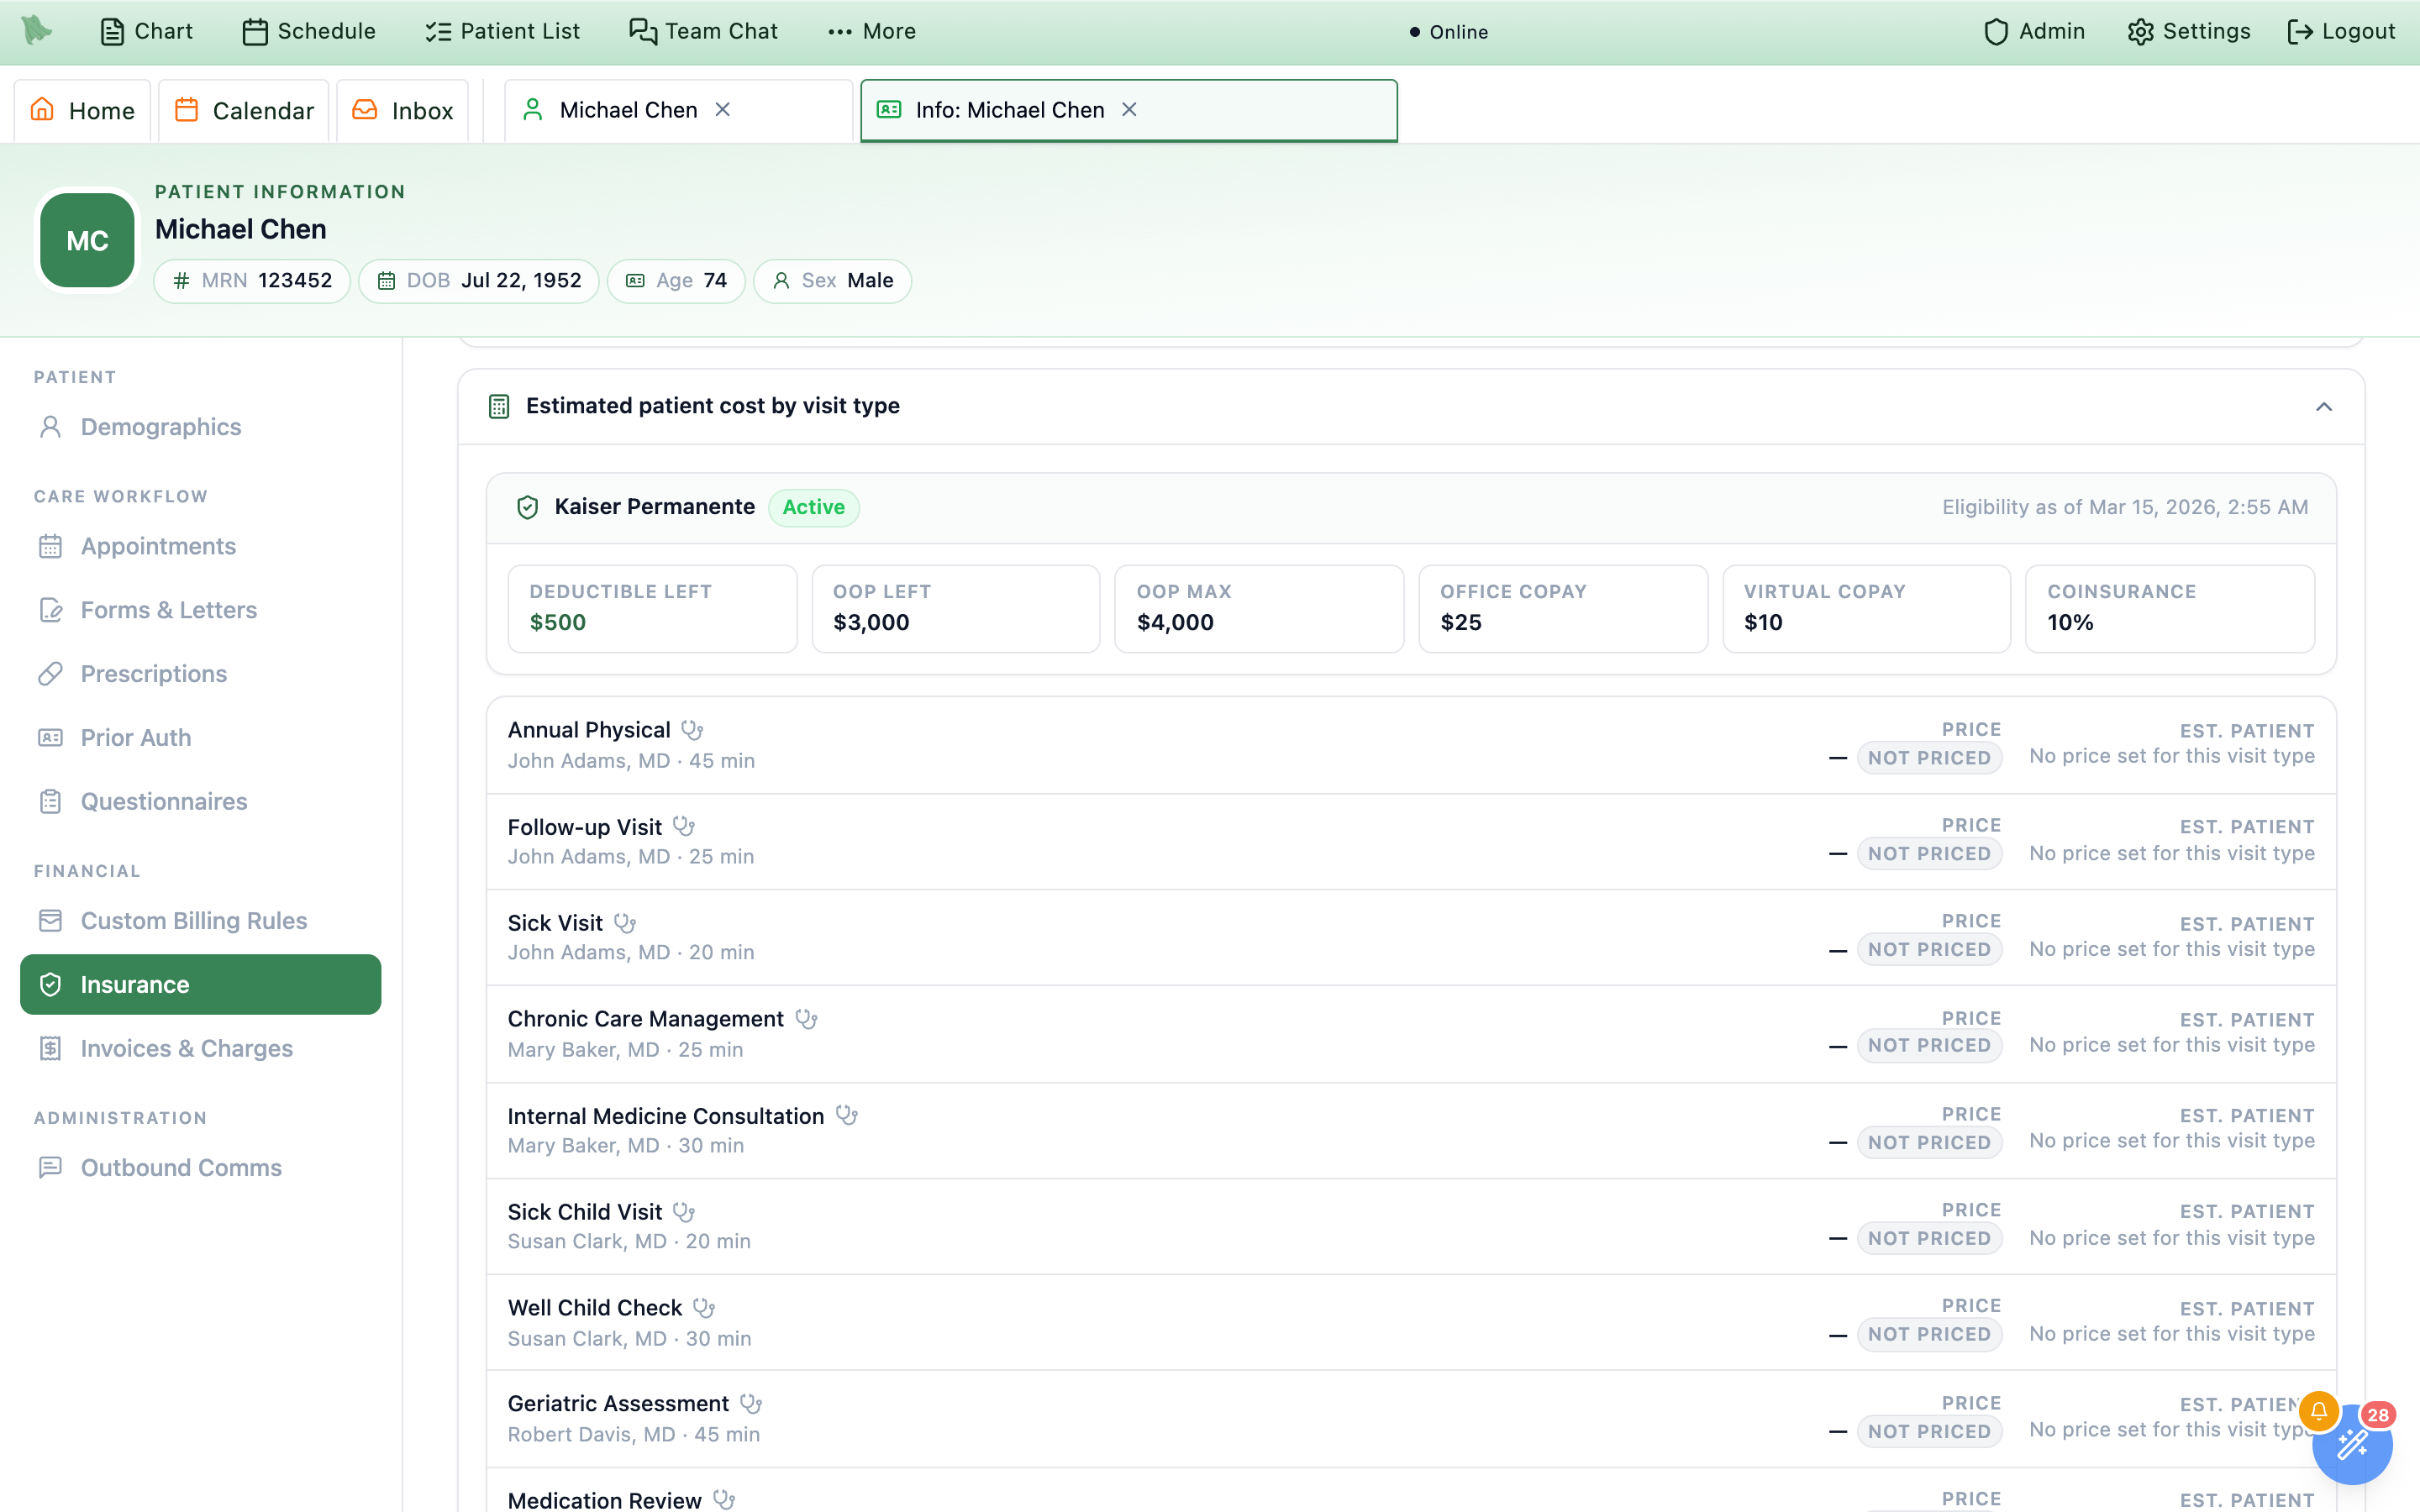
Expand the cost estimate last.
Estimated patient cost by visit typesits at the bottom and starts collapsed. Clicking it is what fetches the estimate, so the tab itself opens fast; once loaded it stays loaded, and collapsing it again does not throw the numbers away. Inside, a coverage summary names the payer with anActive,Inactive, orUnverifiedchip and eitherEligibility as of {date}orEligibility not yet verified, over six tiles —Deductible left,OOP left,OOP max,Office copay,Virtual copay,Coinsurance. Beneath them one row per active visit type shows aPricetaggedNegotiated,Learned rate,Cash rate, orNot priced, and anEst. patientfigure — or the reason there isn’t one, such asRun an eligibility check to estimate. Estimates use the payer’s contract rate, else a rate learned from that payer’s payments (even where claims bill your own list price), else the cash price (see CPT prices & payer rates); a learned-rate estimate is labelled as based on what the payer allowed before, not a contract rate.
| Status chip | What it means |
|---|---|
Active coverage | The policy is active and the last eligibility check confirmed coverage. |
Inactive coverage | The policy is active on your side, but the payer said coverage is not. |
Active | The policy is active and eligibility has never been determined. |
Inactive | Someone invalidated it. |
Expired | Someone expired it with a coverage end date. |
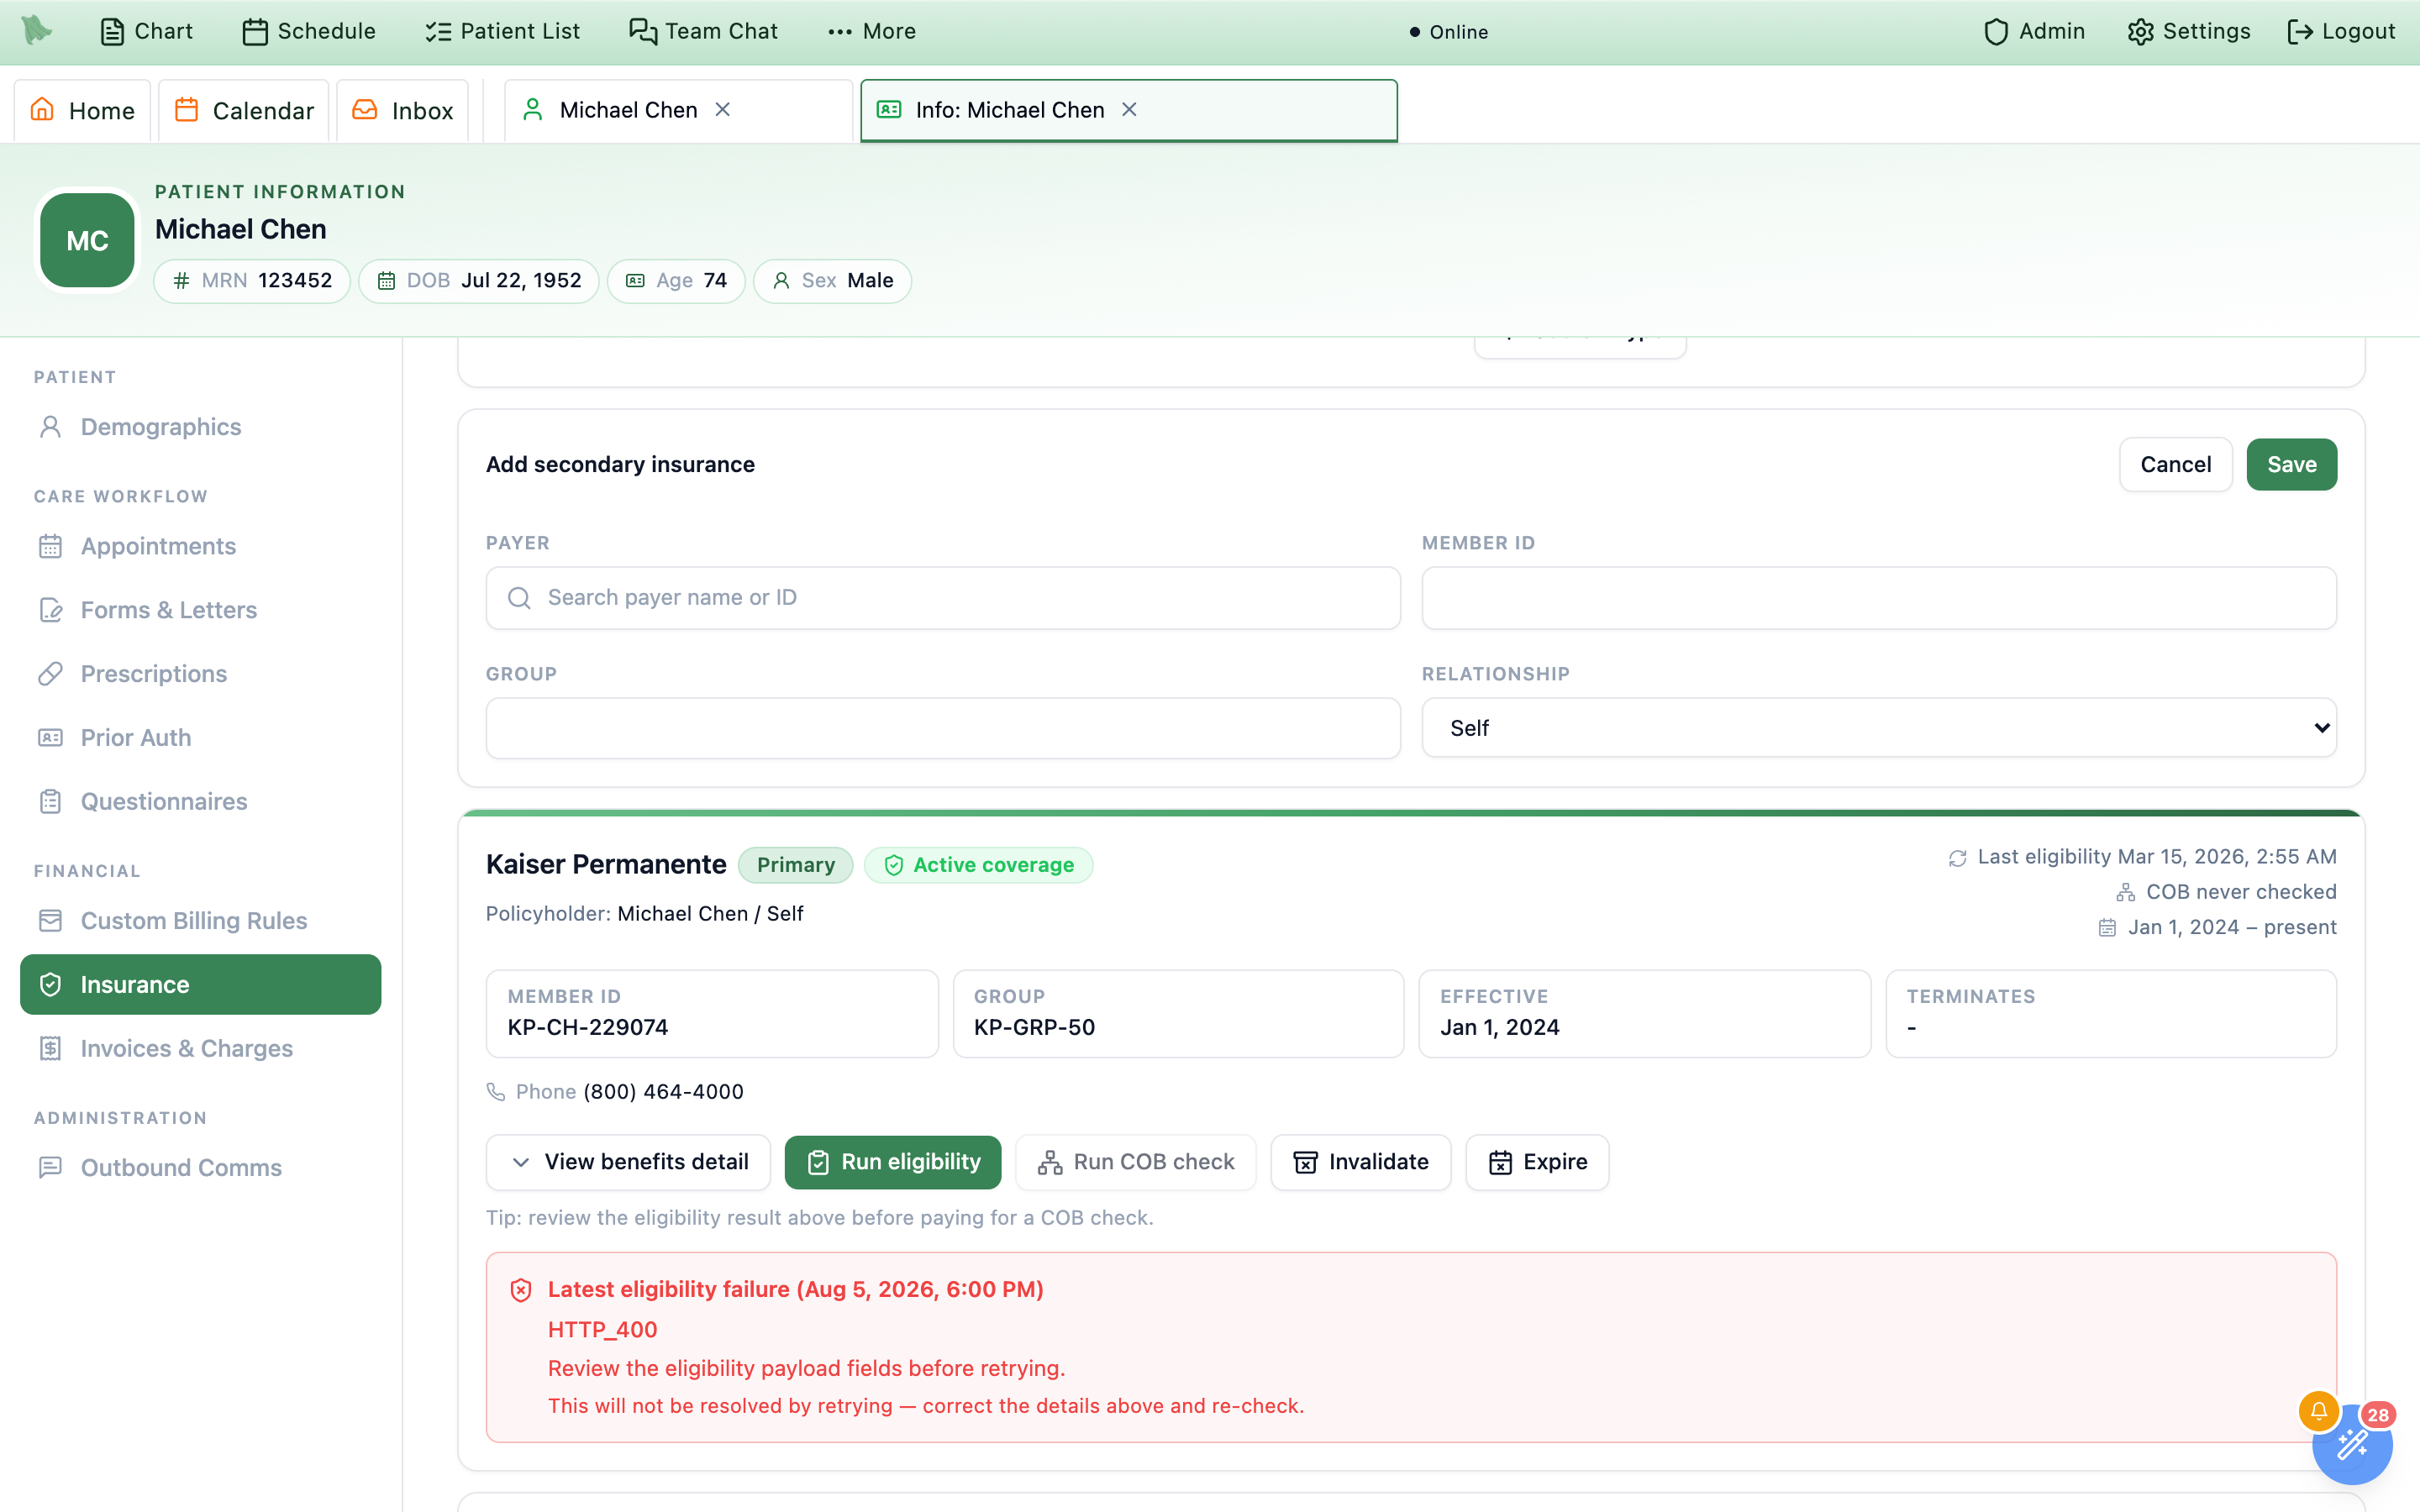
+ Secondary opens the same form as + Primary, now headed Add additional insurance.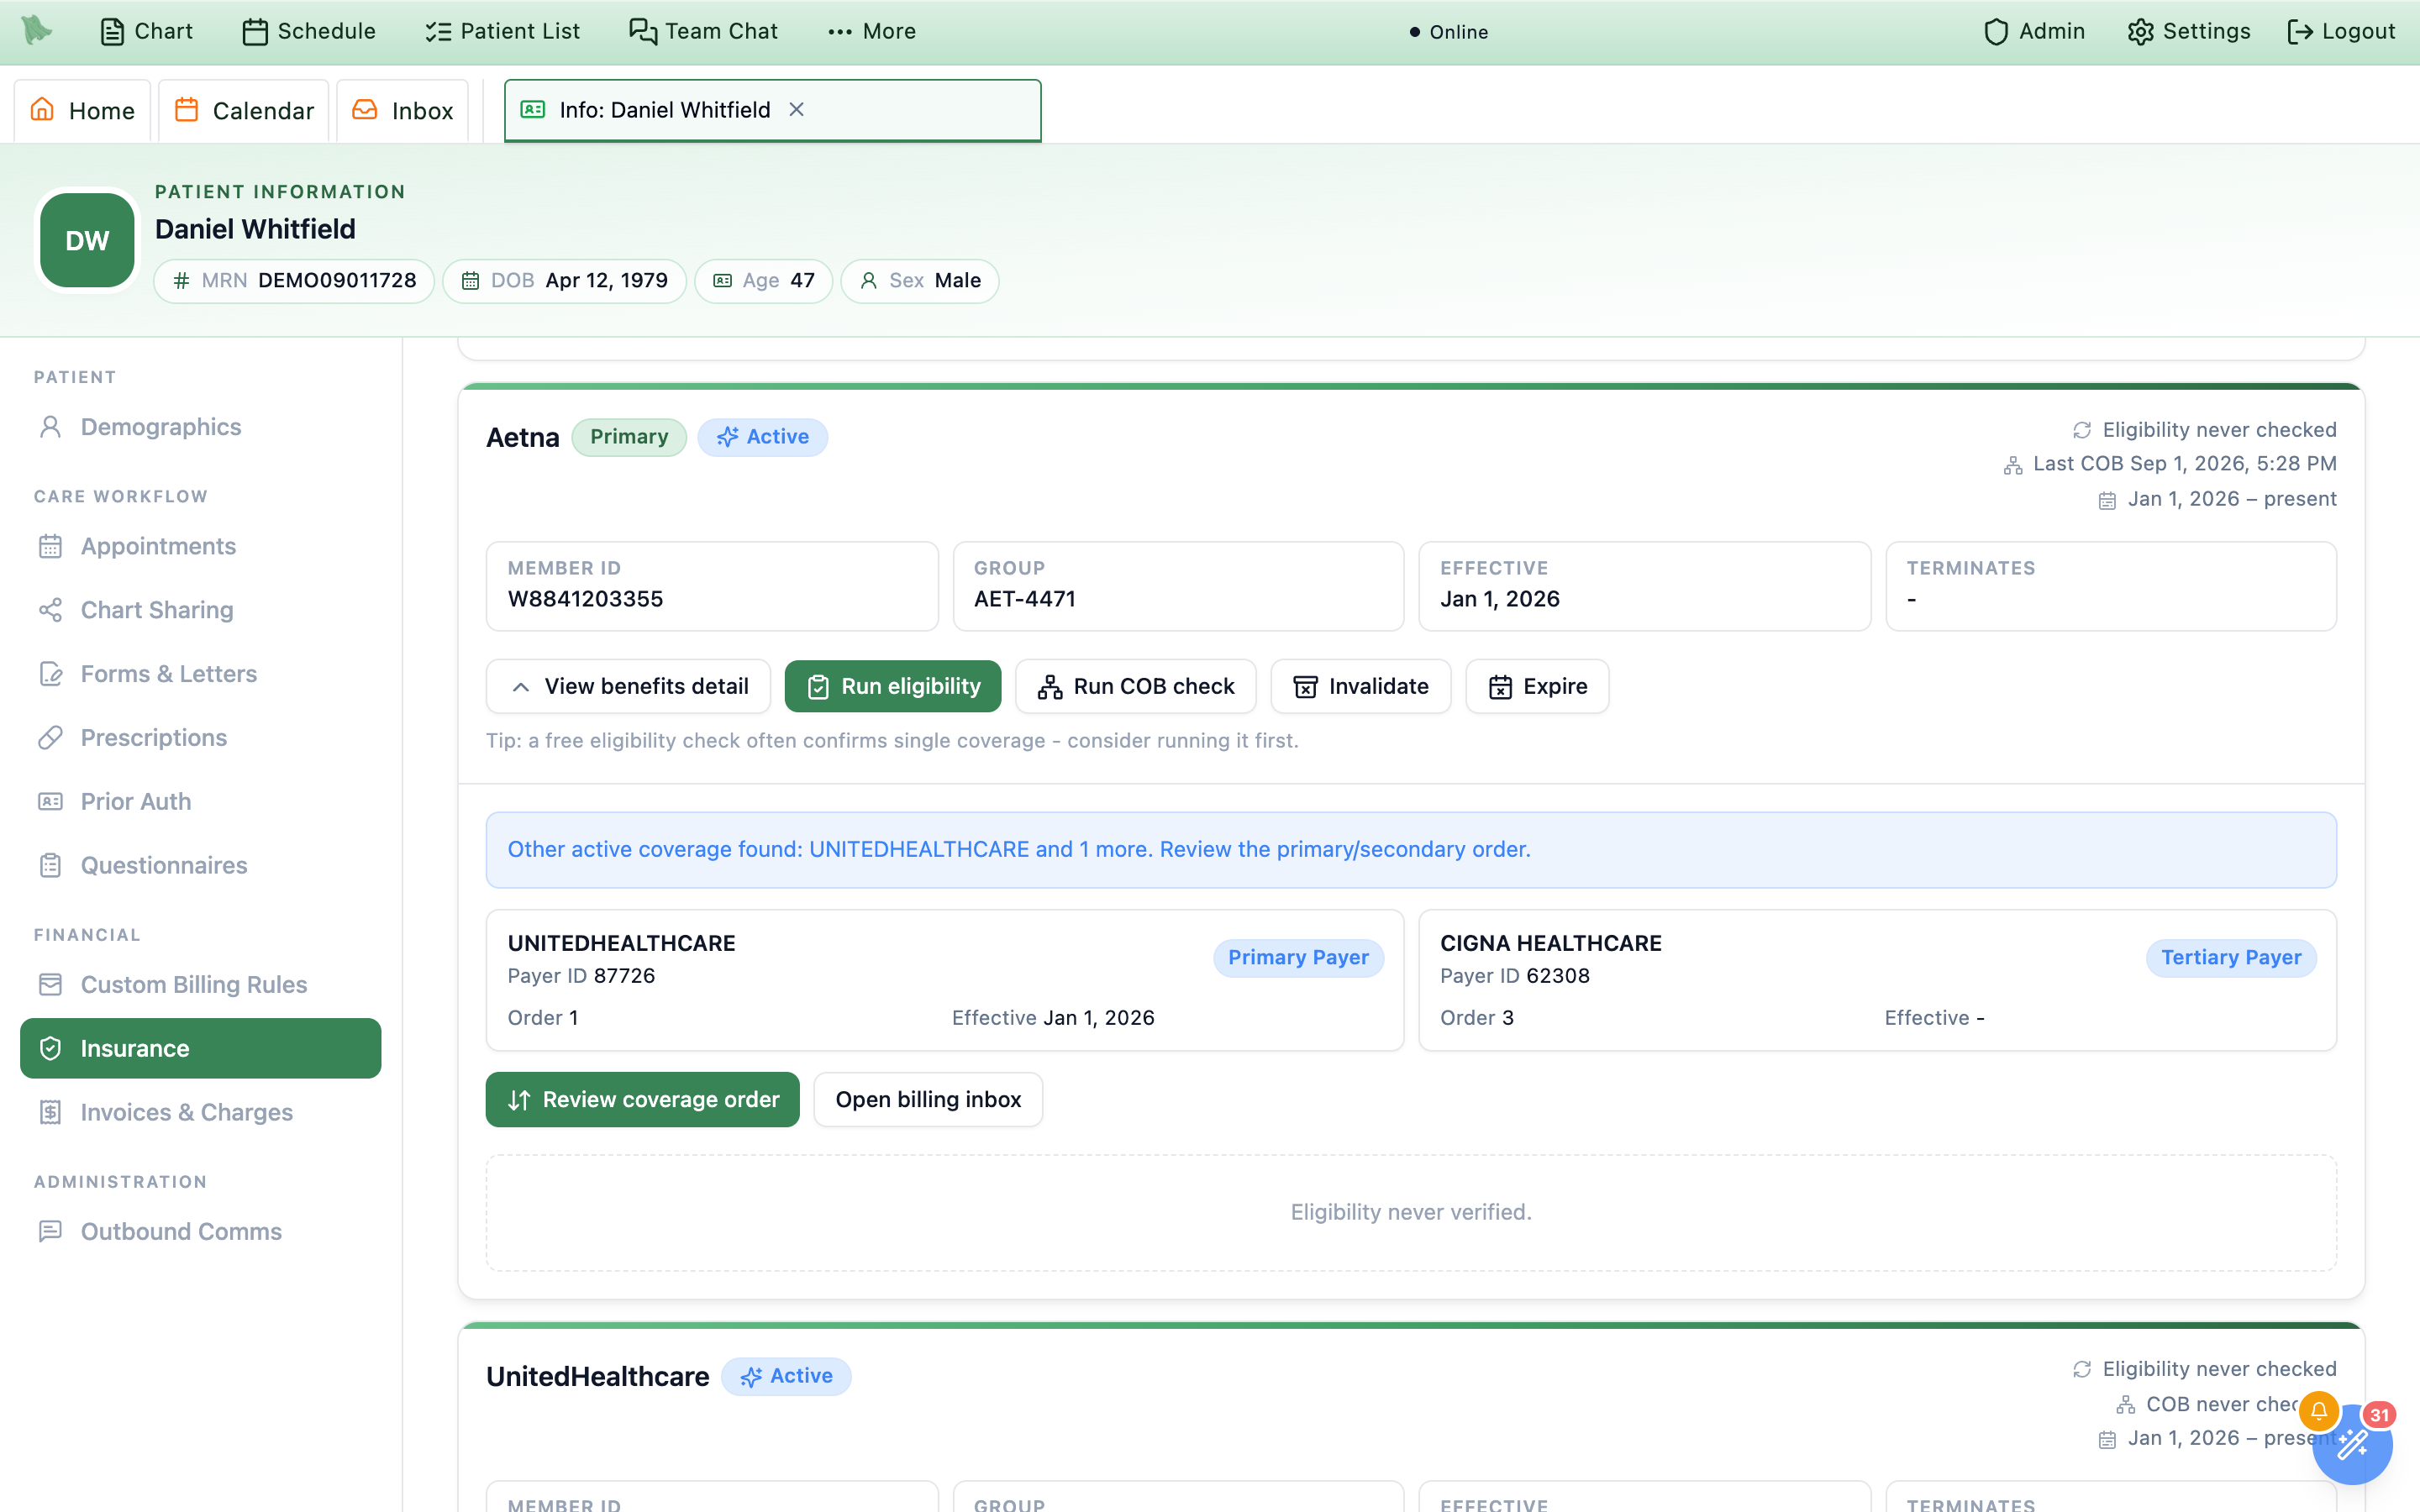
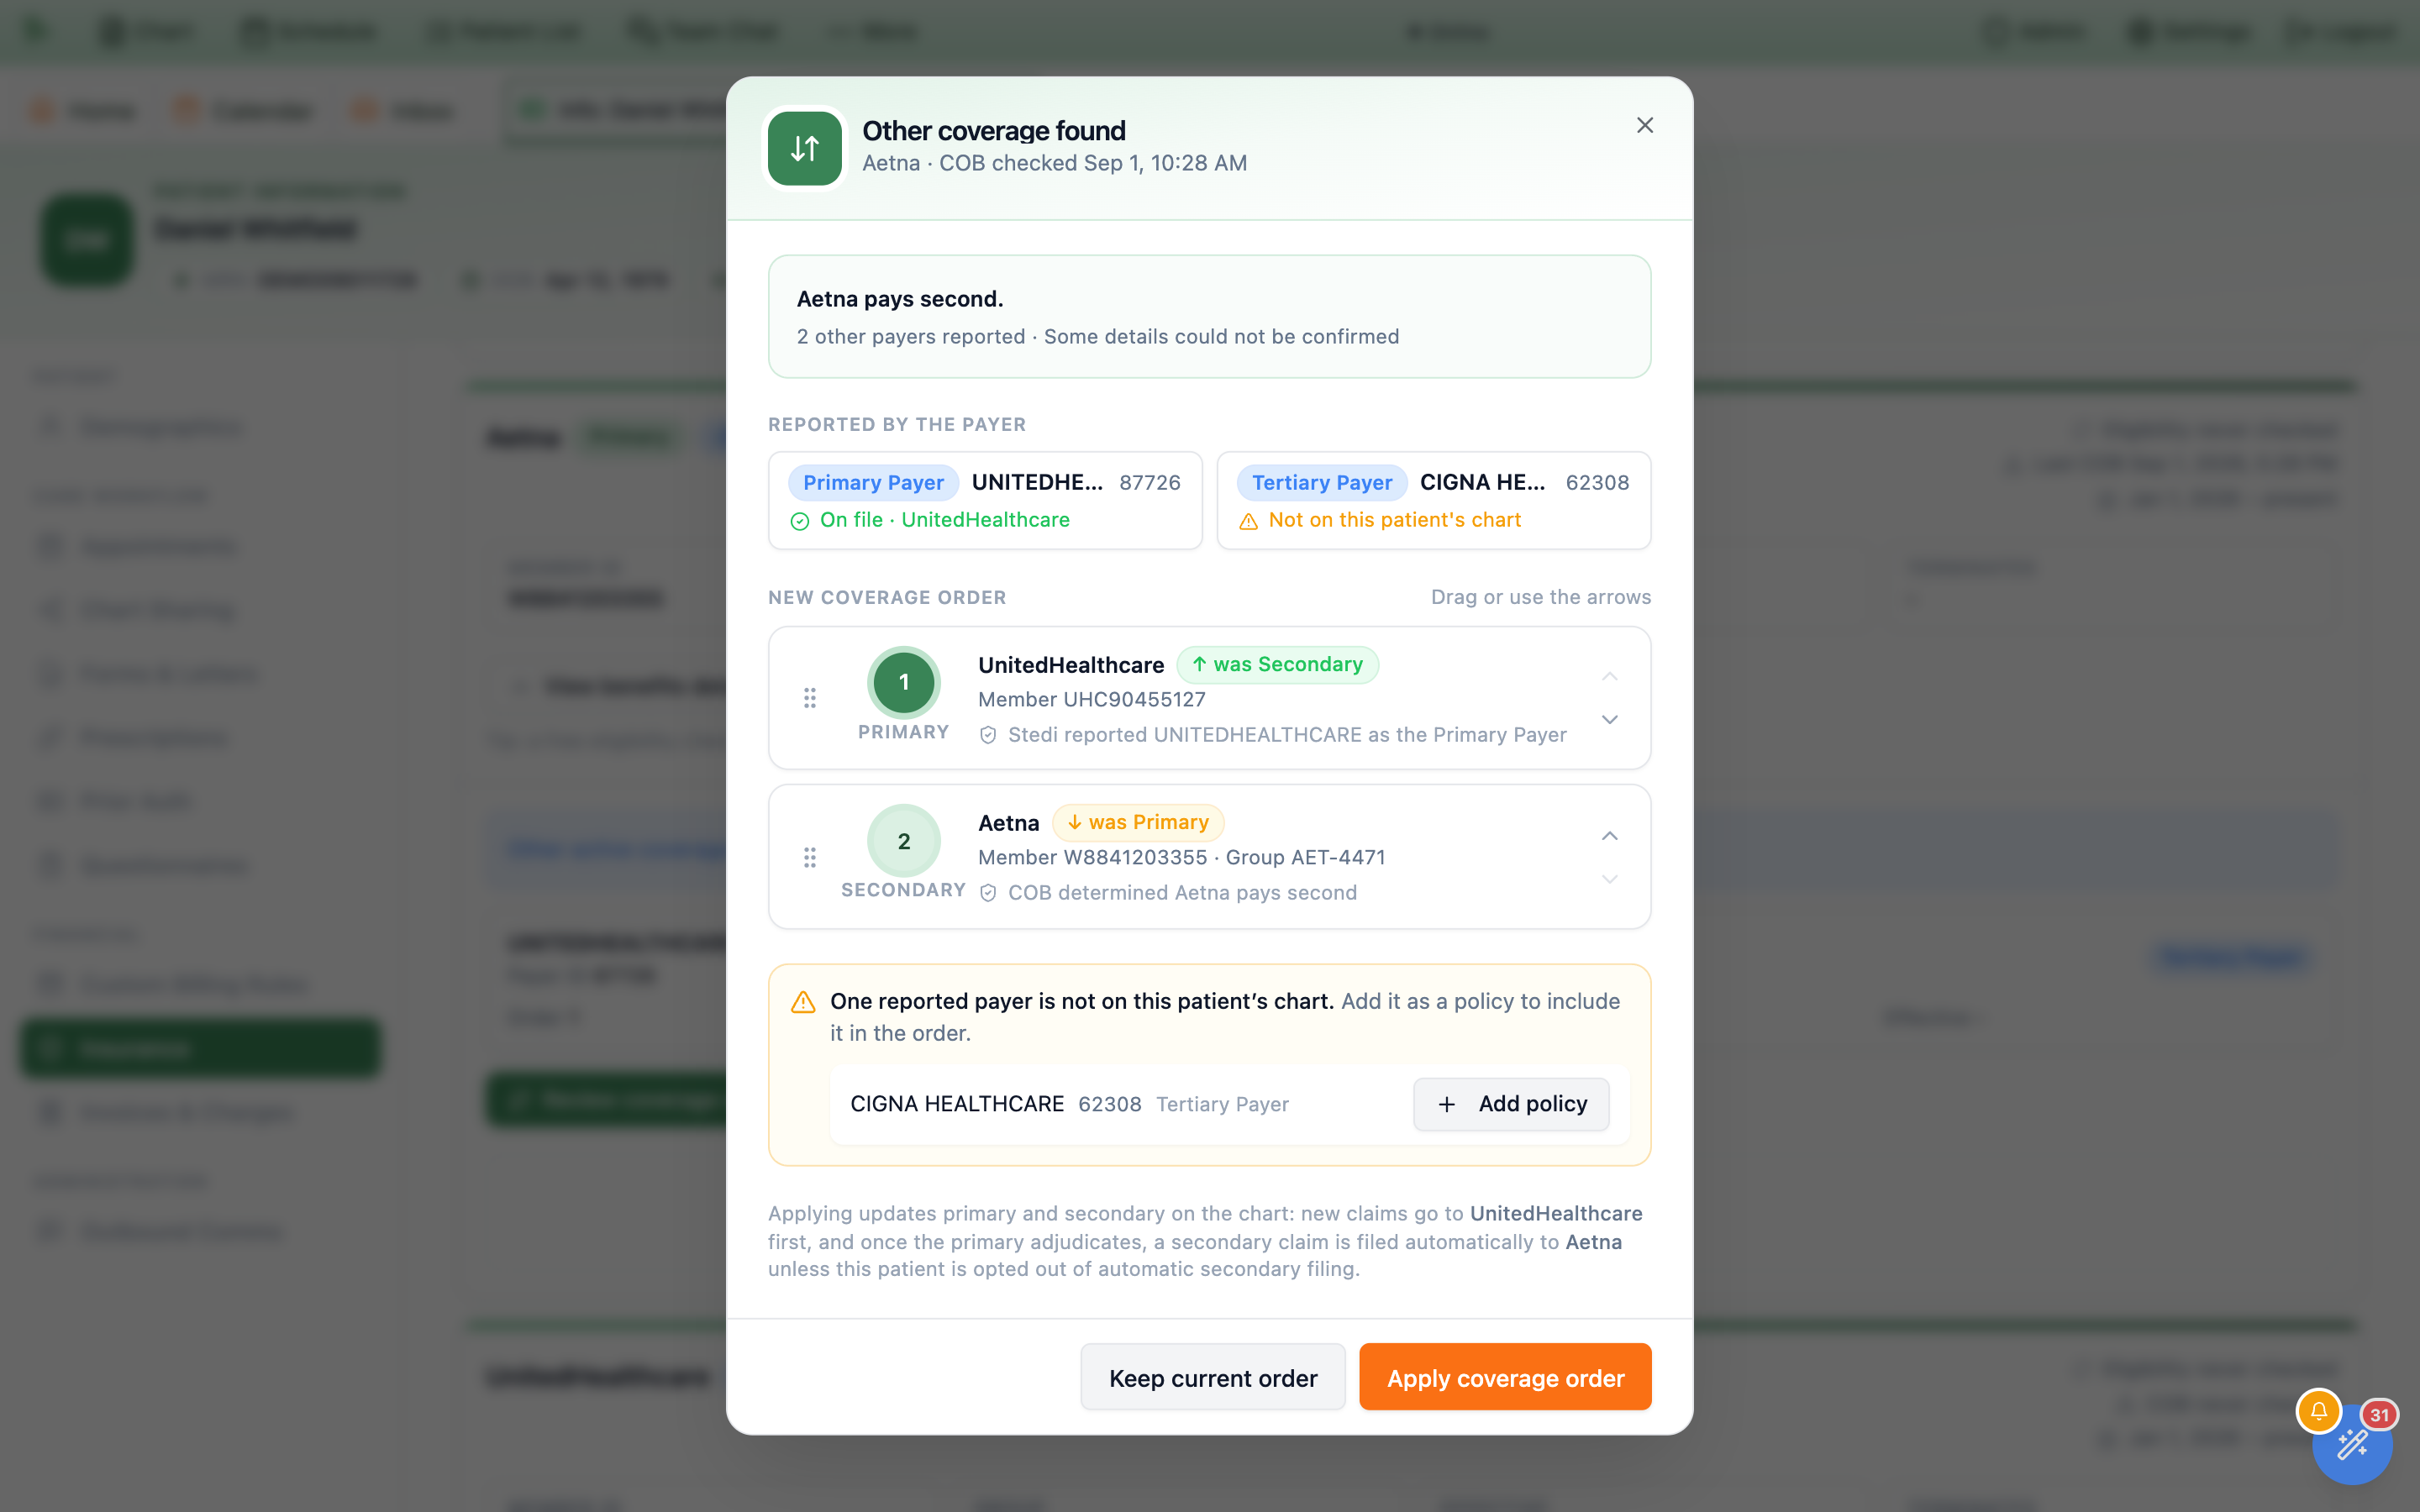
Run COB check costs money. A coordination-of-benefits check asks the clearinghouse for other active coverage and which plan pays first, at about $1 per check — billed whether or not any other coverage is found, roughly three times an eligibility check. Clicking it opens a confirmation headed Run a coordination-of-benefits check? subtitled $1 per check, and the confirm button reads Run COB check ($1). Run the free eligibility check first — the card’s own tip says Tip: a free eligibility check often confirms single coverage - consider running it first. Reserve COB for new patients or a real suspicion of a second plan; it is not supported for traditional Medicare, and the patient’s name and date of birth must match the payer exactly. Not every payer supports the transaction — when one does not, the check comes back refused and you are not billed for it.Primary is who new claims are sent to first, and the dialog spells out the consequence before you confirm. If the practice files secondary claims automatically, the policy you rank second is the one a secondary claim goes to once the primary adjudicates — so an order applied here can put a claim in front of a payer without anyone opening the claim itself. Correcting it later is an ordinary policy edit, but the claims already sent are not recalled. Applying also clears the coordination-of-benefits review item the check raised, provided every payer the check reported is now on the chart.Billing type overrides the classification the system worked out itself. The per-patient exceptions and cash rates live on Custom Billing Rules.billing.claims.manage), so billers can add, edit, and expire policies — staff with neither get Insurance policy changes and clearinghouse checks require patient management or claims permission. The cost estimate, benefits detail, eligibility and COB buttons, and the billing controls need financial access on top; without it that half of the tab is simply absent.When your practice sets a Default Medicare payer in Admin → External Providers → Stedi, a scanned Original Medicare card starts with that Part B payer. Review it before saving; Medicare Advantage still uses its own plan. See Stedi setup.
In Estimate a service by CPT or HCPCS code, select Clinician (optional) when the payer has different clinician rates. The estimate uses the matching contract rate sheet; leaving the clinician blank cannot match a clinician-specific sheet. Payer-rate visibility follows the practice’s rate-access settings.
Add or replace insurance card photos on an existing policy
To add a missing card photo, or replace an old one after the patient brings a new card, attach the photos to the policy you already have instead of creating a new policy. The policy card has Add card photos (or Replace card photos when it already has some). You need permission to manage patients as well as permission to change policies.
- Click
Add card photosorReplace card photoson the policy card.Card photos for this policyopens. -
Get the photos one of three ways.
Under
Upload photos or use this device's camera, choose theFront of cardand, if you have it, theBack of card (optional), then clickRead card photos(on a phone or tablet, choosing a photo also offers the camera). Or clickShow a QR code for a phoneand scan it with a phone; the link works once and is private, and the photos open for review when they arrive. Or, underCard scans waiting for review, clickUse this scanon a card someone already scanned. -
Choose what to copy from the card.
Hero shows the policy’s payer, member ID, group, plan and coverage start date next to what it read on the card. Every field starts on
Keep current; pickUse cardfor any value you want to change. ADouble-checktag marks a value Hero wasn’t sure it read correctly. A new member ID or payer re-checks eligibility, just asEdit policydoes. The policyholder is never changed here; useEdit policyfor that. -
Attach the photos.
Click
Attach card photos(orSave chosen details and attach photoswhen you picked card values). If the policy already has photos, tickReplace the card photosfirst; the button then readsReplace card photos. If the policy change is refused, nothing is attached. A scan with no back photo keeps the back photo the policy already has.
When you click Review scanned card on a scan for a patient who already has policies, Hero first asks Where does this card go?: pick a policy under Add to an existing policy and click Add to this policy, or pick Create a new policy for coverage that isn’t on file yet. A policy with the same member ID or payer is listed first and already selected, with a note saying so, so you don’t end up with a duplicate policy. Photos a scan replaces stay in the chart (see below).
Get back insurance card photos that were replaced
When a new card scan replaces a policy’s card photos, the old ones are kept under Previous card photos on the policy card, where you can restore them. See Previous card photos.
Call the payer
How to reach {payer} on a policy card shows the phone numbers your practice saved for that insurance company. See Payer Phone Book.
Medicare is secondary: choose why Medicare pays second (the Medicare Secondary Payer reason)
When Medicare is not the patient’s first insurance (Medicare secondary, MSP), Medicare refuses the claim unless it says why another plan pays first. Pick that reason on the patient’s Original Medicare policy with Why Medicare pays second on the Insurance tab. Until a reason is chosen, Hero holds those claims instead of sending them.
- Find the policy. A Medicare policy that is not the first insurance and has no reason shows
Pick why Medicare pays secondon its card. ClickEdit policyon that card. - First check that Medicare really pays second. The form explains it: Medicare pays second only while the patient (or their spouse, or for disability a family member) still works for the employer whose group health plan pays first, or when an accident, no-fault, workers’ compensation, liability, black lung, VA or another federal program pays first. A retiree plan, a Medicare supplement (Medigap), Medicaid, or a plan from a small employer means Medicare pays first: fix the order of the patient’s insurance instead (Insurance & eligibility).
- Pick the reason in
Why Medicare pays second. The choices, in plain words:Working, 65 or older: employer group health plan (theirs or a spouse's) pays firstDisabled, under 65: large group health plan (theirs or a family member's) pays firstKidney failure (ESRD), first 30 months of Medicare: group health plan pays firstCar accident or no-fault insurance pays first,Workers' compensation pays first,Other liability insurance pays firstPublic Health Service or another federal agency pays first,Black lung benefits pay first,Veterans Affairs pays first
- Answer the working question. For the two working reasons, Hero asks whether the patient (or family member) is still working for the employer behind the group plan. Choose
Yes, still working thereto keep the reason.No, retired or not working there (or not sure)means Medicare usually pays first, and Hero won’t save the working reason. - Click
Save policy. The card then showsWhy Medicare pays second: {reason}. Claims held only for the missing reason are released and go out with the next send.
- A suggestion, never automatic. After you answer
Yes, still working there, Hero may show the likely reason from the patient’s age and first insurance withUse this reason. Nothing is saved until you click it and save. - Who can set it. It is a billing term: among staff, only billers, billing managers and office managers can set it; providers and administrators can too. Other staff see it read-only in
Edit policy. Changes are audited. - Clear it by choosing
Not chosenand saving. - Held claims. A claim waiting for the reason sits in the Claims pipeline’s held list with a note starting “Held before sending: Medicare is not this patient’s first insurance on file…” (Claims pipeline).
Not accepted: the patient’s insurance is a plan your practice doesn’t take
A red Not accepted chip means the patient’s plan is on your practice’s Insurance we don’t accept list (out of network or not taken). Not accepted · self-pay means the plan is set to Treat as self-pay: visits start as Cash pay, and claims to it are held (unless the entry covers only some plans of the insurance).
An eligibility check’s Active Coverage only says the plan is active, not that your practice is in its network. When your practice lists only some plans of an insurance (for example TRICARE Prime under TRICARE East, or Medicaid plans under BlueCross of Tennessee), Hero matches them on the plan name and insurance type from the patient’s latest eligibility check, so the flag appears after the first check and is judged again after every new one.
- Patient Information →
Insurance: the chip is on the policy card; hover it for the reason. Below the plan name the card says “Not accepted by this practice: {plan}”, for example “Not accepted by this practice: TRICARE East — plans with “PRIME” in the name”. It updates as soon as a new eligibility check comes back. - Calendar and check-in: the appointment shows
Not accepted; hover for “Not accepted: {plan}.” (with “Treat the visit as self-pay.” for a self-pay plan). The pre-visit readiness view shows the same chip on the policy. - Booking: the review step shows
Not accepted: {plan}, with “Your practice doesn’t accept this plan” or “Your practice treats this plan as self-pay”. Open it for what to tell the patient. It never blocks booking.
What to do. Talk with the patient about payment before the visit, or add the insurance they have now. For a self-pay plan, tell them the visit will be self-pay. Patients who pick the plan in the portal already saw an Insurance not accepted notice.
An administrator manages the list (Insurance we don’t accept). For how billing handles these visits, see Plans you don’t accept.
Every visit for this patient, with paperwork, reminders & outcome
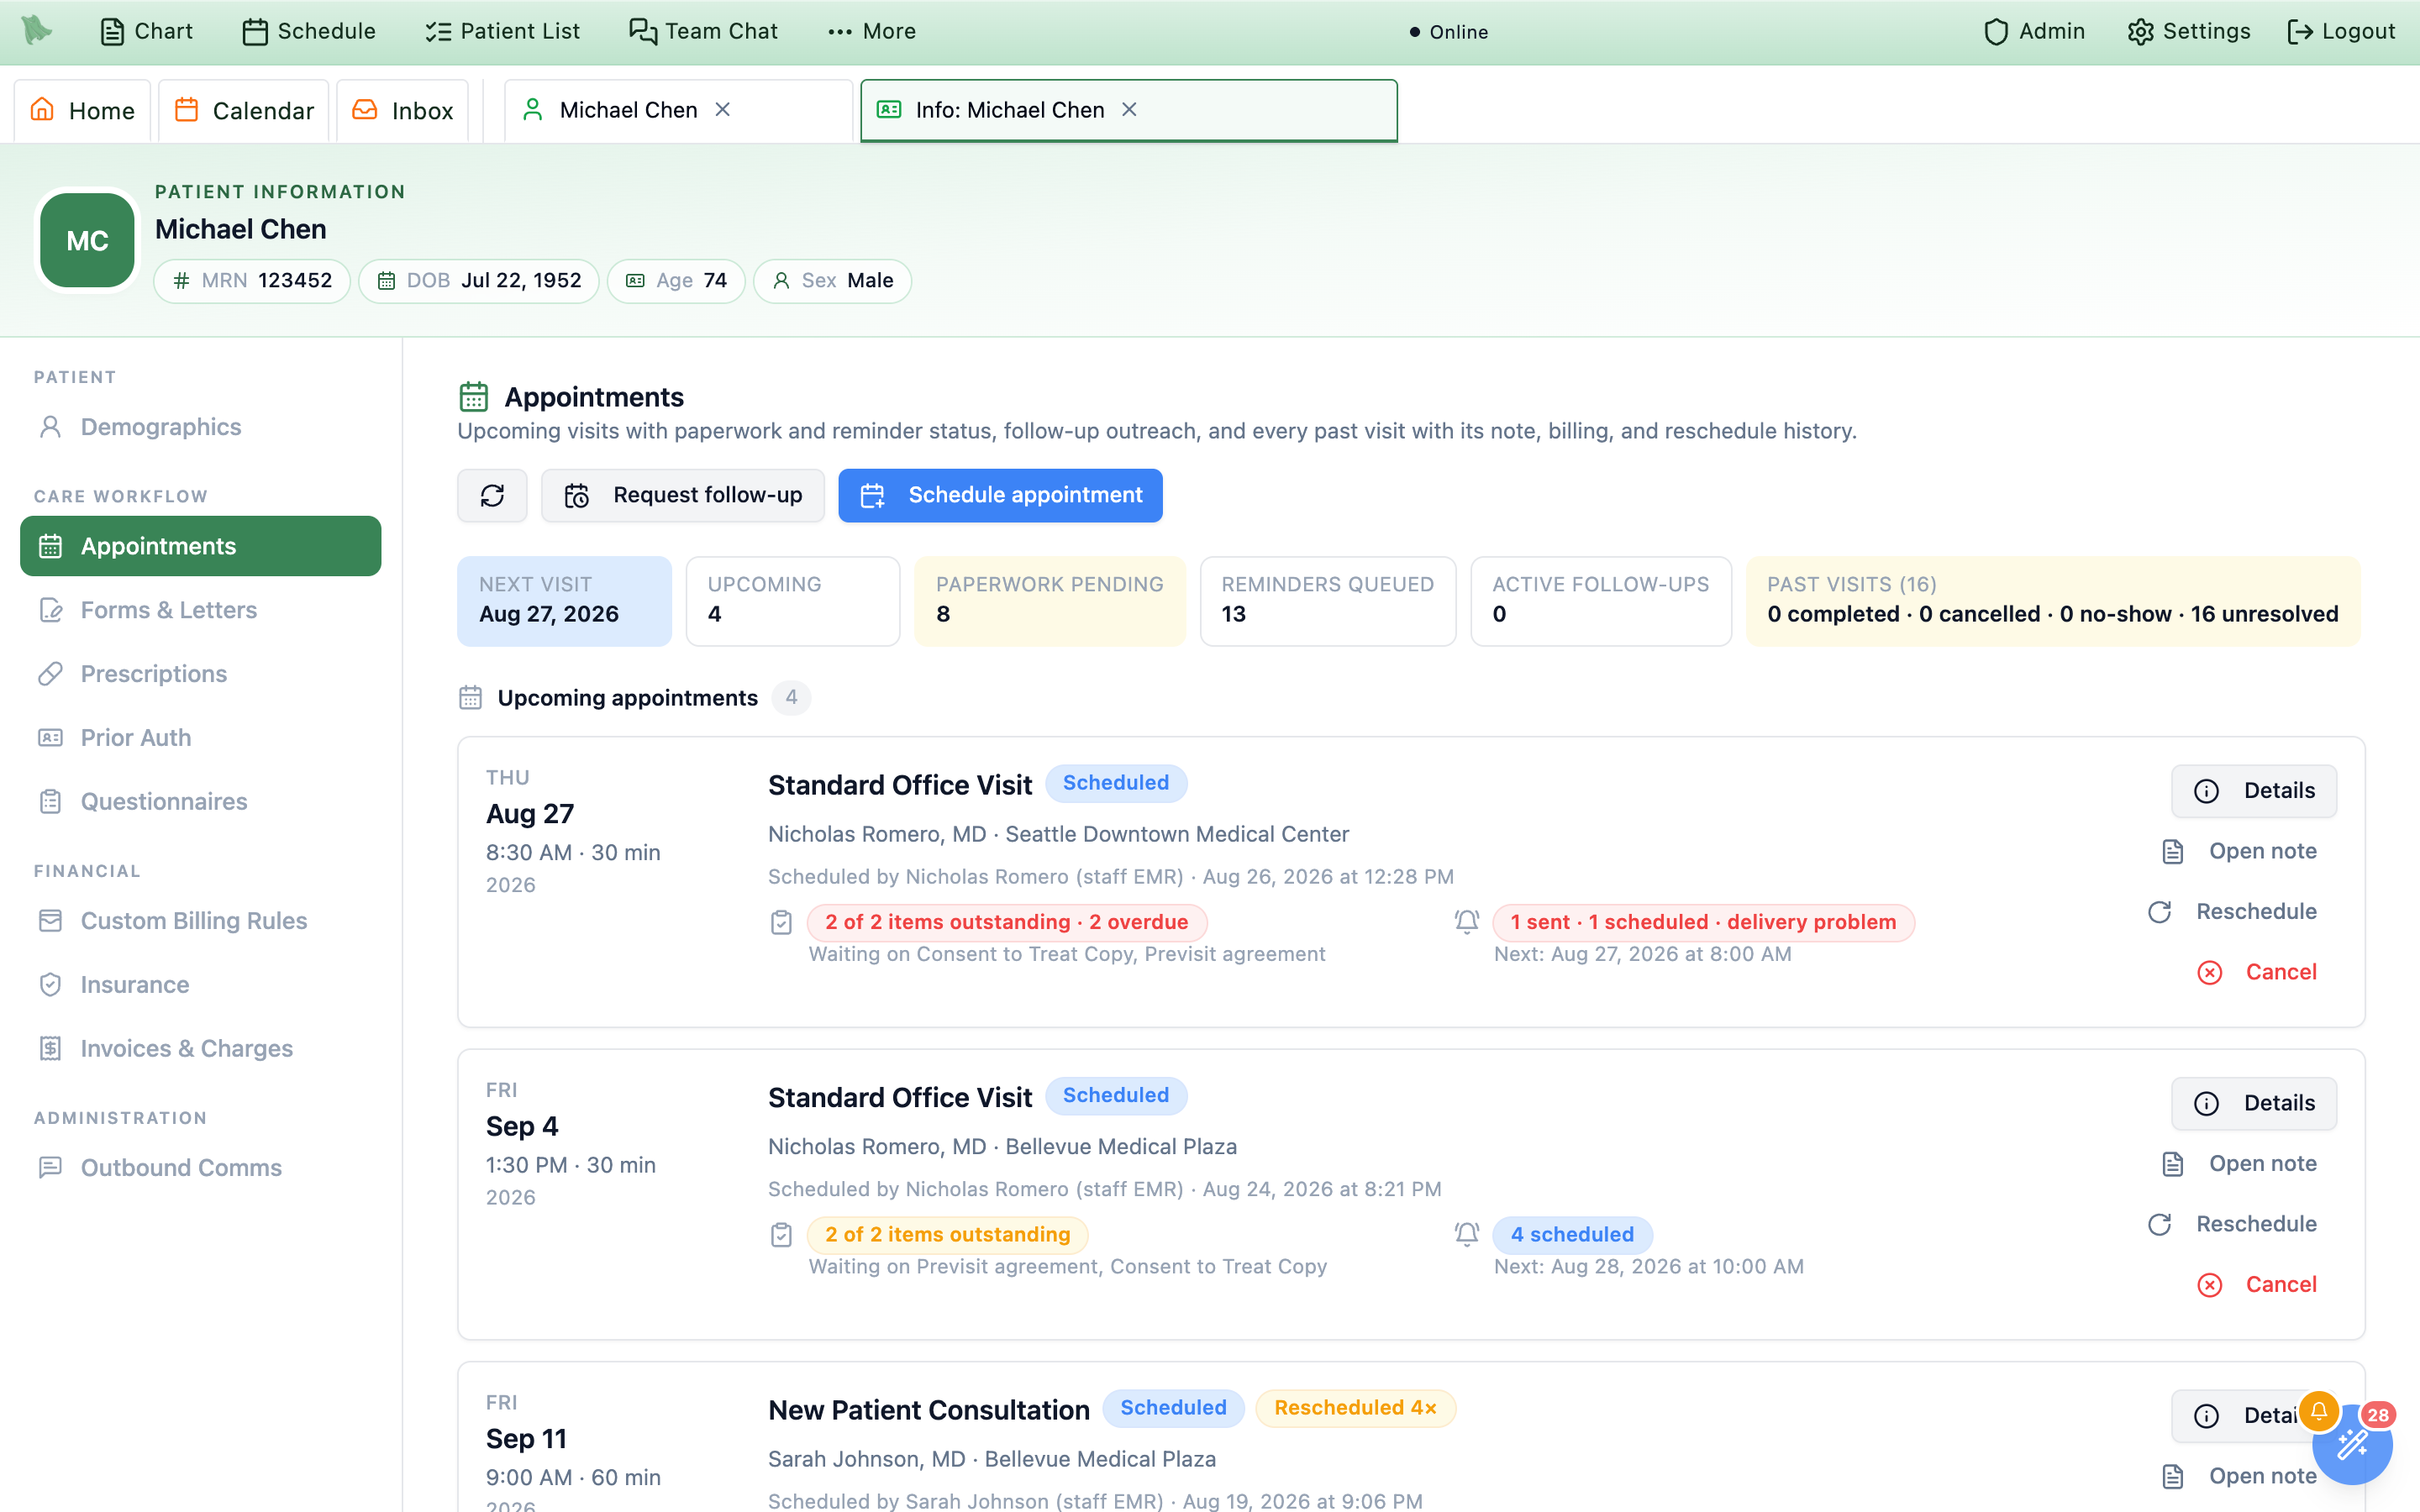
The Appointments tab is the patient-level view of the schedule — as its own sub-line puts it, upcoming visits with paperwork and reminder status, follow-up outreach, and every past visit with its note, billing, and reschedule history. Booking and rescheduling still happen in the scheduler; this tab shows one patient’s whole picture and sends you to the right place. Beside the heading sit Request follow-up, Schedule appointment, and a Refresh appointments icon.
At the top, Prevent this patient from self-scheduling makes the patient contact the practice to book or reschedule while allowing staff to schedule. Physicians, administrators, and staff with scheduling-management permission can change it; the checkbox saves immediately. This is separate from an unpaid-balance scheduling rule and does not cancel existing visits.
-
Scan the six summary chips.
Next visit(a date, orNone scheduled),Upcoming,Paperwork pending,Reminders queued,Active follow-ups, andPast visits (N)— whose value is a breakdown such as0 completed · 12 cancelled · 1 no-show · 29 unresolved, turning amber the moment anything is unresolved. -
Work the upcoming cards.
Each card leads with the weekday, date, start time and duration — in your practice’s time zone, never the browser’s — then the visit type, a status chip, a
Telehealthpill, aRescheduled 4×chip when the visit has moved, aFrom follow-up requestchip when it came out of outreach, the provider and location (orProvider not set), and a booking line such asScheduled by Nicholas Romero (staff EMR) · Aug 26, 2026 at 12:28 PM. Actions on the right:Details,Open note(only with an encounter),Reschedule,Cancel. -
Read the two readiness badges.
Between them they answer “is this visit actually ready?” without opening anything. Paperwork reads
No paperwork required,Paperwork complete (2/2),2 of 2 items outstanding, or — in red —2 of 2 items outstanding · 2 overdue, with a caption naming what is still open (Waiting on Consent to Treat Copy, Previsit agreement). Reminders readsNo reminders,No reminders sent or scheduled, or a count such as1 sent · 4 scheduled, gaining· patient confirmedin green when the patient replied yes and· delivery problemin red when a message failed or bounced; when another is queued,Next: Aug 27, 2026 at 8:00 AMsits underneath. Reminders already sent stay counted and listed after the patient checks in, joins the video visit, or the visit is cancelled; only the ones not yet sent are cancelled.Detailslists each appointment reminder asSent(with when),Failed, or stillScheduled/Queued, and theReminders queuedchip counts only the ones still to go out. InsideDetails, theQuestionnaires & paperworksection lists what the visit type assigned — orNothing was assigned for this visit.— and, for anyone who can send paperwork (front desk with patient-management permission, physicians, administrators), aSend a formbutton that opens the same dialog as the Questionnaires tab. The form goes to the patient’s Forms to sign, linked to the visit’s encounter when it has one. Switch the dialog to A packet to send one of your practice’s packets instead; every item in it is linked to this visit the same way. -
Clear the unresolved ones.
A visit whose date has passed but which nobody ever marked completed, cancelled, or a no-show is Unresolved: an amber
Unresolvedchip in place of its status, with the hover note Still “Scheduled” after the visit date — mark it completed, no-show, or cancelled. The history filter has anUnresolvedoption, and each such row gains aResolvebutton. It opens the same dialog asCancel: pickInitiated by—Provider / clinicorPatient, deliberately unselected until you choose, because provider-initiated waives the fee — then aReason, optionally aNote for the chart, and confirm withCancel AppointmentorMark No-Show. -
Follow the outreach trail.
Follow-up requestsshows a{n} activepill and aShow {n} closedtoggle — a request the patient has already booked counts as closed and hides by default.Request follow-upasks which visit it belongs to, aVisit type(Office visit,Telehealth,Phone call),When(2 weeksthrough6 months, or your own number and unit), an optionalPreferred time of day, an internalReason, andInstructions for the patient. The patient is contacted after the practice’s review delay, not instantly. When the patient already has an upcoming visit from about a week before the follow-up window onward (with any provider; a treatment session such as a Spravato, ketamine or TMS session counts only for a request of that same visit type), the request showsScheduledwith that visit and no booking reminder goes out;Resendthen says so instead of sending. Each row then keeps the whole trail — status (Pending outreach→Patient notified→Awaiting response→Reminder sent, ending atScheduled,Expired, orDeclined), the booking window, attempt counts, whether the patient replied or booked, and every message sent — plusResendandCancel, which fires immediately with no confirmation. -
Mine the history.
Appointment historylists past visits underWhen,Visit,Outcome & billing, andActions, filtered byShow(All visits,Completed,Cancelled / rescheduled,No-shows,Unresolved).Outcome & billingcarries a clickable note chip —Signed note,Note completed, orUnsigned note— plus a billing chip in the same words as the invoices (Paid,Balance due,Partially paidonly when the patient paid part,Past due,With insurance,Insurance review,Awaiting secondarywhile the visit’s secondary claim is pending,Not billed,No charge,Billing cancelled), the payer name, a balance such as$25.00 due, and any no-show or late-cancel fee; rows with neither readNo encounter. Cancellations spell themselves out:Late cancellation · by patient — Sick. The filter only searches pages you have loaded, which is why the button readsLoad more (17 more visits to search).
The reschedule chain is durable. Reschedule opens no dialog here — it hands you to the scheduler in reschedule mode with the visit preloaded, reusing one Scheduling tab however many times you click it. What this tab keeps is the record: a Rescheduled 4× chip on the card, Rebooked as a new appointment. on a visit that was replaced, and inside Details a Lifecycle section reading Rescheduled 4 times. above a timeline of every move — Booked, Rescheduled, Cancelled, Marked no-show, Checked in — each with its actor, its timestamp, and for a reschedule the old slot and the new one. Open the rebooked appointment and Open the appointment this replaced walk the chain.
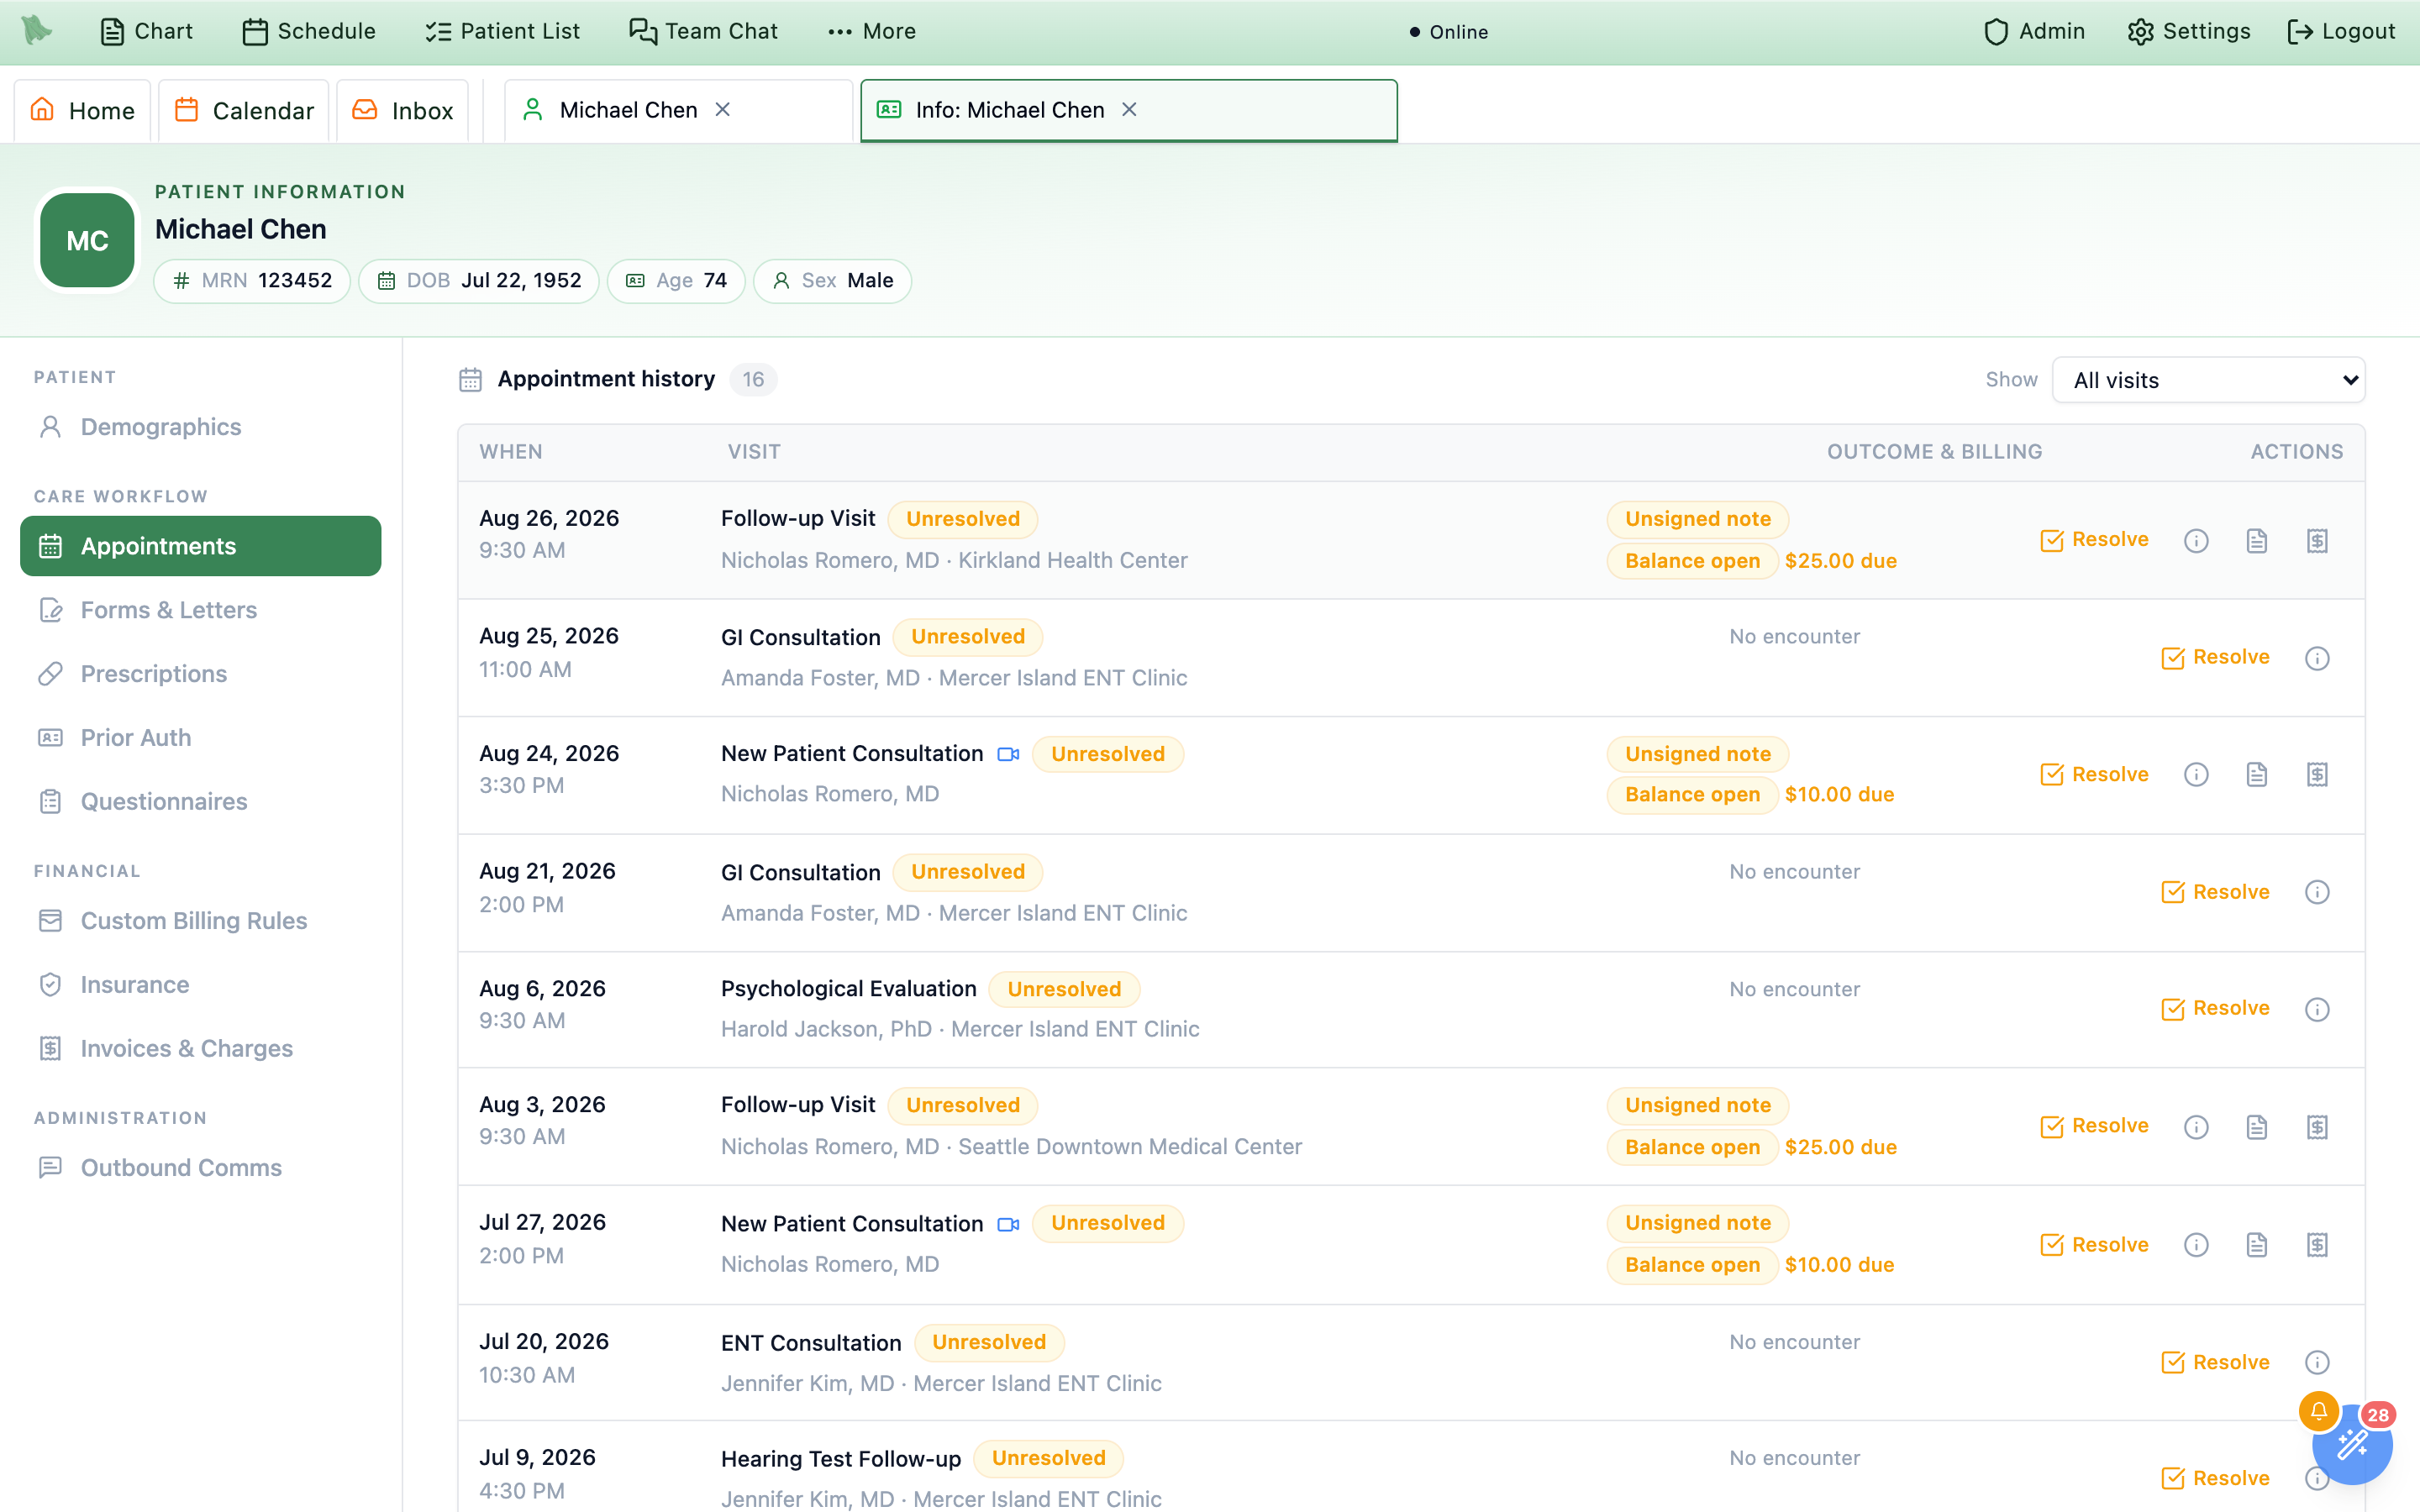
Resolve appears on every stale visit.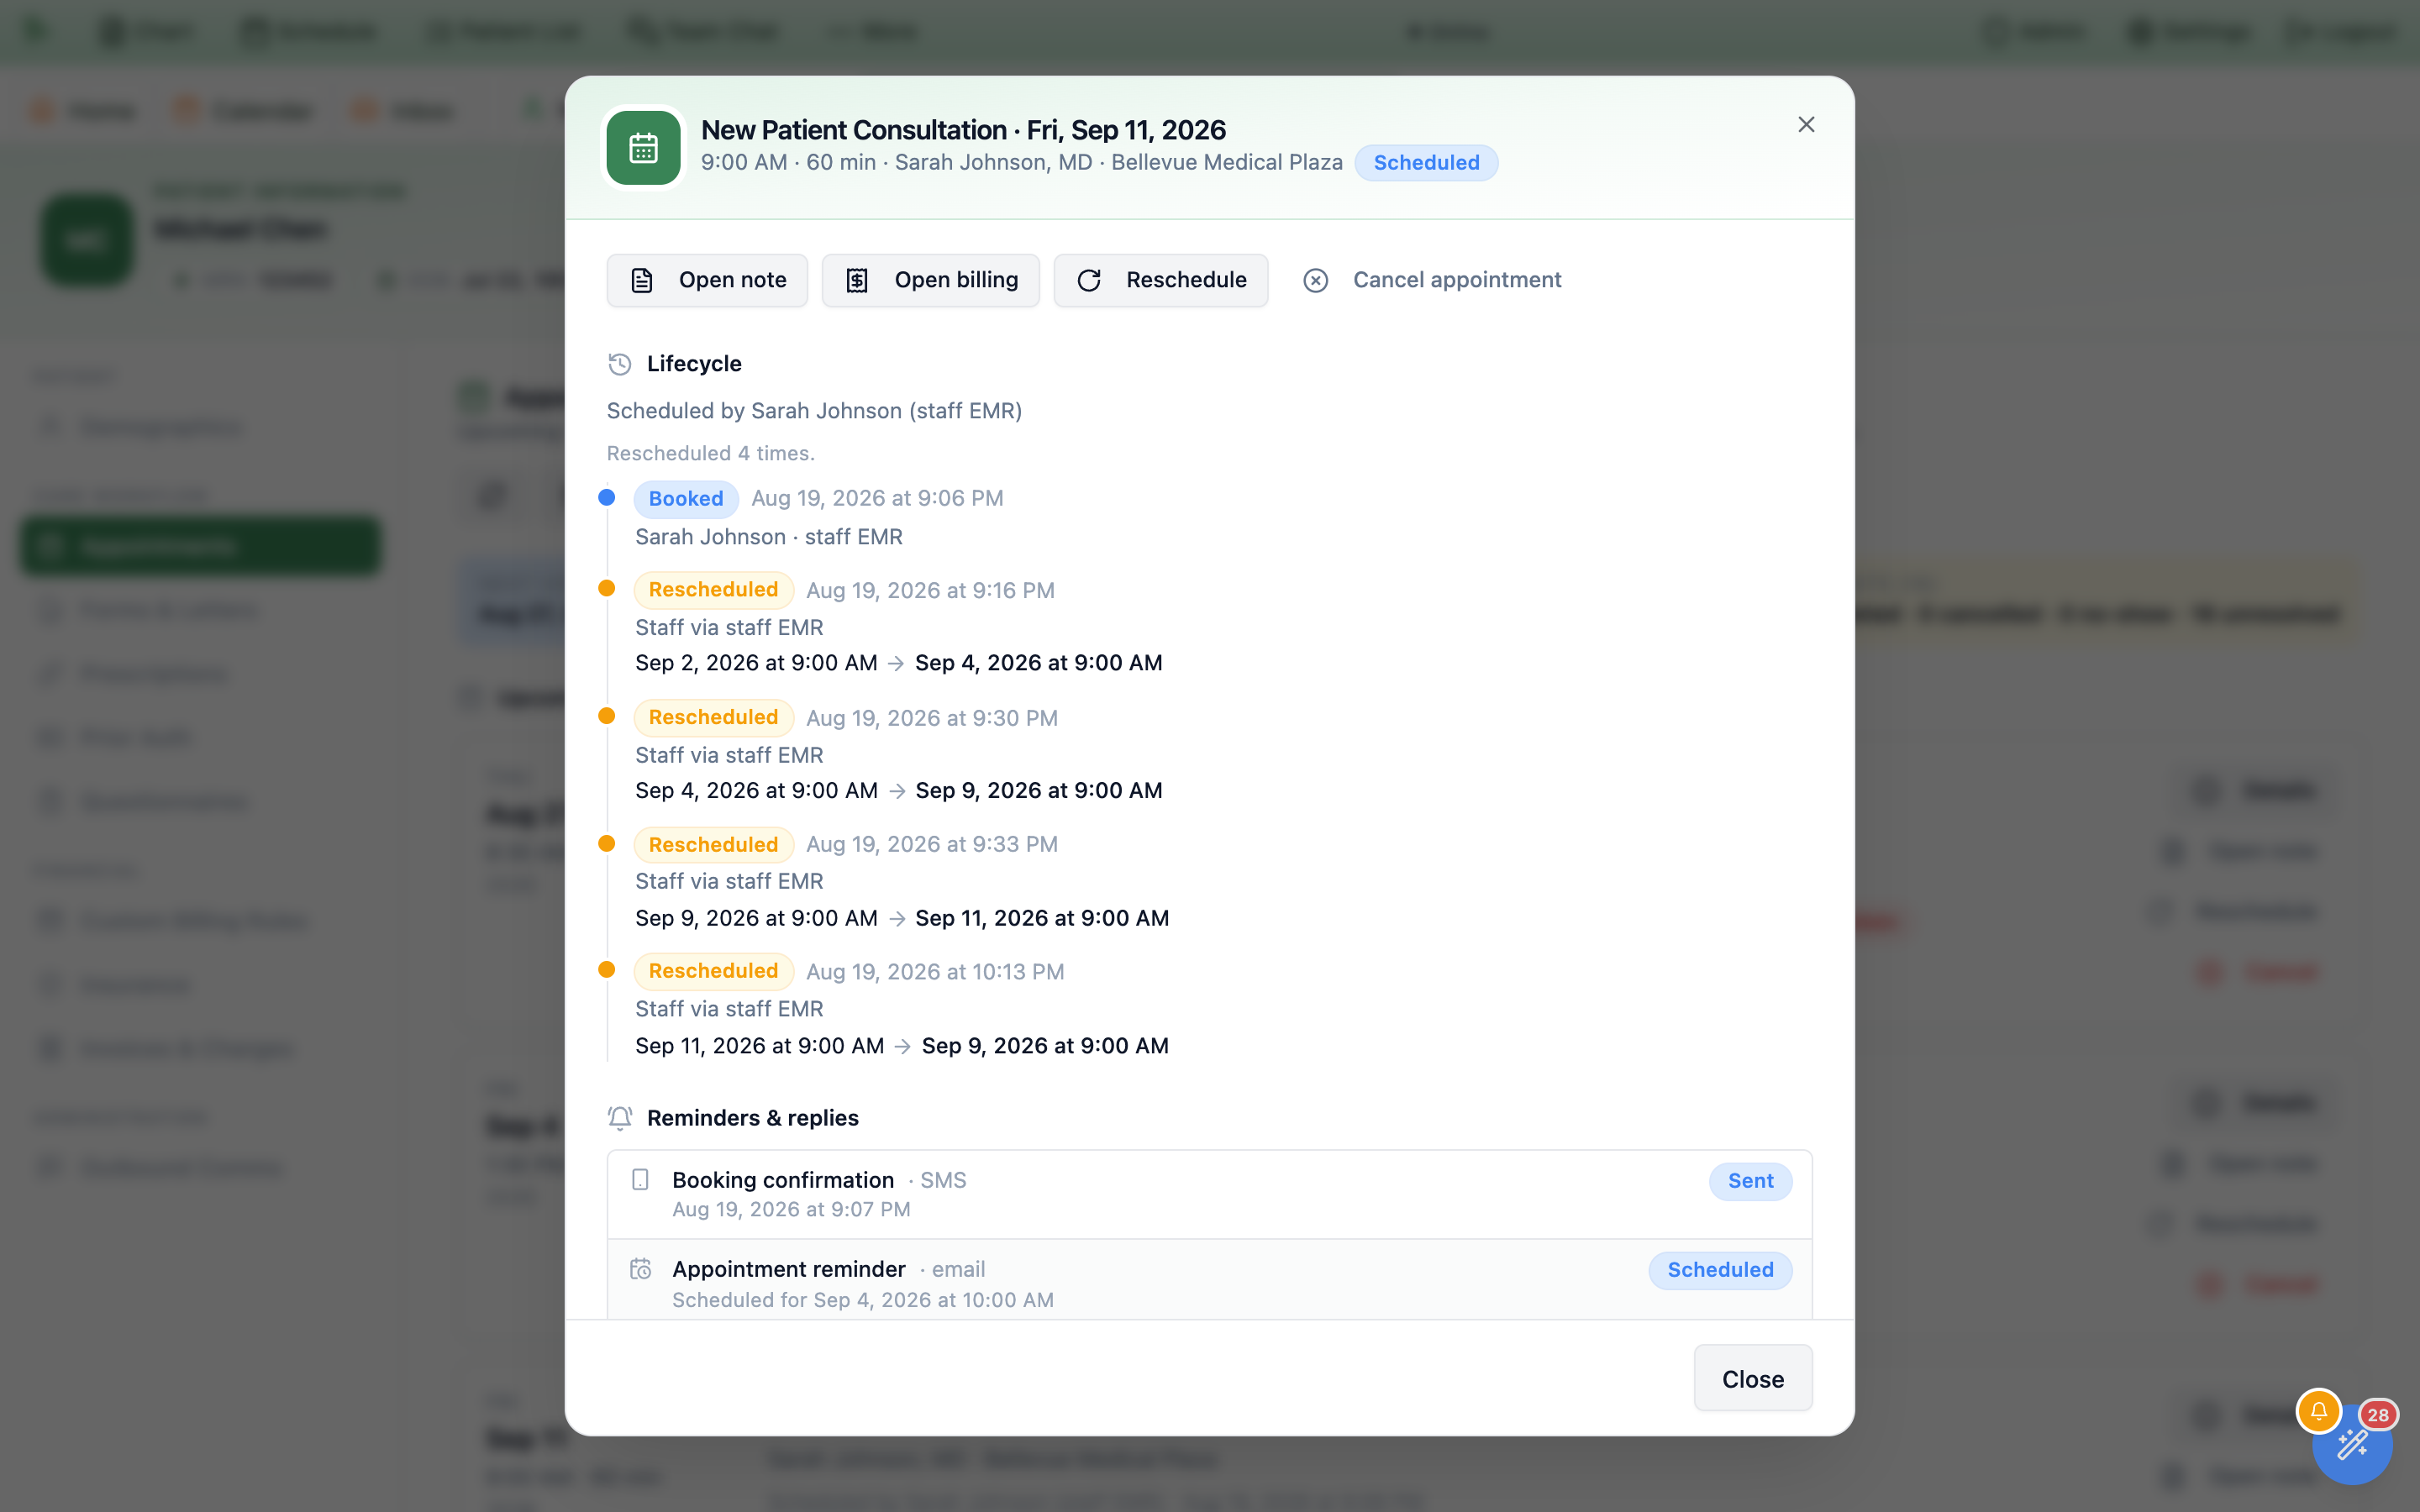
scheduling.view puts it in the sidebar and lets it load — without it the panel reads Appointment history is restricted / Your role does not include scheduling access for this practice. scheduling.manage makes it writable: Schedule appointment, Request follow-up, Reschedule, Cancel, and Resolve all disappear without it, while Details stays. Admins and physicians pass both by role. Without a billing permission the amounts are not merely greyed out — balances, claim figures, and Open encounter billing are absent from what the screen is given, so nothing here leaks a number your role cannot see. Balances themselves are worked in patient balances.Send questionnaires, automate them, read the answers
The Questionnaires tab is the per-patient counterpart to the practice-wide questionnaire rules: send one now, put this patient on their own recurring schedule (or stop a practice rule reaching them), read every result, and find out why a rule did or did not fire. A banner at the top states the precedence plainly — rules on this tab apply only to this patient and always override practice-wide questionnaire rules for the questionnaires they cover. For a patient under 18 a second banner names who actually receives the questionnaire, and warns when no guardian contact is on file to deliver it to.
-
Start with the trends.
Score trendsis the first section, shown once any instrument has at least two completed, scored results (PHQ-9, GAD-7, AUDIT-C, a youth screener or one of your own all qualify the same way). Each instrument showsLatest {score}/{max} · {interpretation}and the change since the previous result, for example▼ 4 since Sep 2, with dates on your practice’s calendar. Open one for its chart: the instrument’s severity bands (for example Minimal to Severe on a PHQ-9) are shaded behind the line in neutral tones and named in the right margin, with the scale marks at the cutoffs, then aDate/Score/Interpretationtable. Click a point or a row to read exactly how that submission was answered. Results from versions with different score ranges are not compared. With nothing to plot the section is absent rather than empty. -
Send one now.
Send a questionnairehas one button,Send Questionnaire, which expands an inline picker rather than a dialog. Type inSearch questionnairesto narrow it; your practice’s own questionnaires sort to the top, then the standard library alphabetically. Clicking a row sends it immediately — no confirmation step, no due-date field, no channel picker. Delivery follows the patient’s notification preferences, and for a minor it routes to the guardian. A greenPHQ-9 sent.confirms it; a red banner carries the reason it failed, most oftenActive assignment already existswhen one is still open. Above the search,Send a packetopens the packet picker described below. When your practice has turned on Someone else inAdmin > Questionnaires, the picker starts with Send to:The patientorSomeone else, for a teacher, spouse or other person who fills in a questionnaire about the patient (Send questionnaires to someone else). Those sends are listed in their own card, Sent to someone else, withResendandCancel; in the timeline they read Sent to Ms. Jones, teacher and, once answered, Completed by Ms. Jones, teacher, and the patient never sees them. -
Send a consent, intake or other form.
The
Send a formcard sits underSend a questionnaire. ItsSend a formbutton opens a short dialog with this patient already filled in: choose the form inForm— any form your practice has published in Previsit Paperwork, including on-request-only ones such as a controlled substance agreement — and clickSend form. The patient signs it in the portal under Forms to sign; no appointment is needed. A green line confirmsSent “Consent to Treat” to {name}, andSend another formkeeps the patient selected. This is the front desk’s way to send paperwork: it needs the same patient-management permission as sending a questionnaire, not access toAdmin > Previsit Paperwork. If the list is empty, nobody has published a form yet — an administrator does that in the paperwork manager. -
Send a whole packet.
In the
Send a formdialog, switch One form to A packet (or openSend a packetin the questionnaire picker). Choose the packet inPacket: its forms and questionnaires are listed in order, all ticked; untick anything this patient doesn’t need, and an item whose form was deleted or retired is greyed out with Not available. ClickSend packet (N items). A green line sums it up, for exampleSent “Packet 2: clinical” to {name}: 4 items sent, 1 already waiting. They get one message about it and find everything together in the portal., and lists anything not sent with the reason. Anything the patient already has waiting is not sent twice. For a minor, the visit check underFor visitapplies to the packet too. Administrators build packets in Admin > Questionnaires > Packets. -
Put the patient on their own schedule.
Automatic questionnaires for {first name}lists this patient’s rules;+ Add ruleopensNew patient rule. Pick a mode —Send automaticallyorStop automatic sending(practice-wide rules will never auto-send these to this patient) — choose the questionnaires, and for a sending rule chooseWhen:On a schedule,When a visit is booked, orWhen a visit starts. A scheduled rule takes a cadence:Monthly,Every 3 months,Every 6 months,Yearly, or your ownEvery N daysup to 1,095. Each saved rule becomes a card with anActiveorPausedpill, a plain-English subtitle (Blocked from org-wide sending, Every 3 months), andPause/Resume, edit, and delete controls. -
Check what the practice is already doing.
Practice-wide rules for this patientis a collapsed panel counting the org rules that reach this patient, plus how many are partly or fully overridden by patient rules. Expand it and each rule shows its triggers and its questionnaires, with any questionnaire a patient-level rule has taken over struck through and labelledOverridden by patient rule. -
Read the timeline.
Previous & upcominglists everything sent plus what is scheduled next. Filter withAll,Upcoming,Completed,Missed; search by name; sort byNewest first,Oldest first,Questionnaire, orScore. Each row carries a badge —Scheduledfor a projected future send (drawn with a dashed border, because it does not exist yet),Sent — awaiting completionfor a real assignment, thenCompleted,Skipped, orExpired— a score chip where one exists, the date (Next around…,Due…, or the completion date), and where it came from:Sent manually,Patient rule · PHQ-9 every 3 months,Practice rule · Follow-up Visit questionnaires, orPhone agent. Click a completed row and its answers open inline underneath, question by question, with any safety flag and the item it fired on marked. When the questionnaire scores domains separately, aSubscalesbreakdown shows each domain’s score and cutoff result — see Score, timing, and every answer. A questionnaire that ended without answers says why:Skipped,Declined,Expired,Withdrawn (visit changed),Withdrawn (visit cancelled), orReplaced (updated version). -
Cancel one that was sent by mistake.
A sent questionnaire the patient has not started has a
Cancellink on its row.Cancel questionnaireexplains “The patient will no longer see this questionnaire. It stays in the chart marked Skipped.”; confirm withCancel questionnaireor back out withKeep it. If the patient has just started it, Hero refuses: “Could not cancel this questionnaire. The patient may have just started it. Refresh and try again.” Nothing is ever deleted; see Cancel a sent questionnaire. -
Record a refusal, or fill it in with the patient (optional feature).
With
Social needs screeningturned on inAdmin → Additional Features(off by default), an open questionnaire’s row also offersPatient declined(sent or started) andFill in with patient(not started yet).Patient declinedopens Patient declined to answer (“The patient will no longer see this questionnaire. The chart shows it as Declined, and shared records report that the patient declined to answer.”), with an optionalNote (optional, stays in the chart); clickRecord as declined. A declined questionnaire is never scored.Fill in with patientopens the questionnaire so you can enter the answers in the office, thenSave answers; every required question must be answered (“… or close and use ‘Patient declined’ if they would rather not answer.”). The same feature adds the social needs and behavior screeners (Hunger Vital Sign, the CMS social needs screening tool, financial strain, education, stress, physical activity, social connection and intimate partner violence) to your questionnaire library. -
Act on a positive social needs screen.
Under a completed social needs screener with a positive answer,
Suggested next stepslists each need (for example Food insecurity) with Concern: … · Goal: … and a referral idea (“Refer to a food assistance program (SNAP, WIC, food bank)”).Add to chartadds that concern and goal to Goals, health concerns & health status and then readsAdded. It needsGoals, health concerns and health statusturned on and permission to edit the problem list; otherwise the button is greyed out and says which is missing. -
Debug a rule that did not fire.
Rule checksanswers “why did this patient not get it?” Each rule shows anApplies,Does not apply,Suppresses, orOverriddenpill, aPatient rule/Practice rulescope pill, its triggers, and how many upcoming visits matched.Patient criterialays each condition out in three columns — the criterion, thePatient / visitvalue, and what theRule expects— andUpcoming visit checksrepeats that per visit for the next few appointments. A row reading visit typeStandard Office Visitagainst an expectedFollow-up Visitis the whole answer. -
See what the rules actually did.
Rule checksanswers “what would happen now”; the collapsedWhy questionnaires were or weren't sentat the bottom answers “what happened, and why”. Its summary reads, for example, 12 times the rules ran · 3 not sent. Each entry is one run —Visit booked,Visit changed (type, provider or time),Visit note opened,Portal registration,Date of birth corrected, orQuestionnaires withdrawn— with its time, the visit, and one line per rule markedSent,Already there,Skipped,Not sentorWithdrawn, the deciding reason first, in your practice’s words: “Not sent: patient is 16, rule is for 18+”, “Not sent: pre-visit forms are off for ‘Follow-up’ visits”, “Not sent: visit type ‘Follow-up’ is not one of the rule’s visit types”, “Not sent: the visit was booked more than 7 days ahead”.Show all Nlists older runs; with none it readsNo questionnaire rule has run for this patient yet.
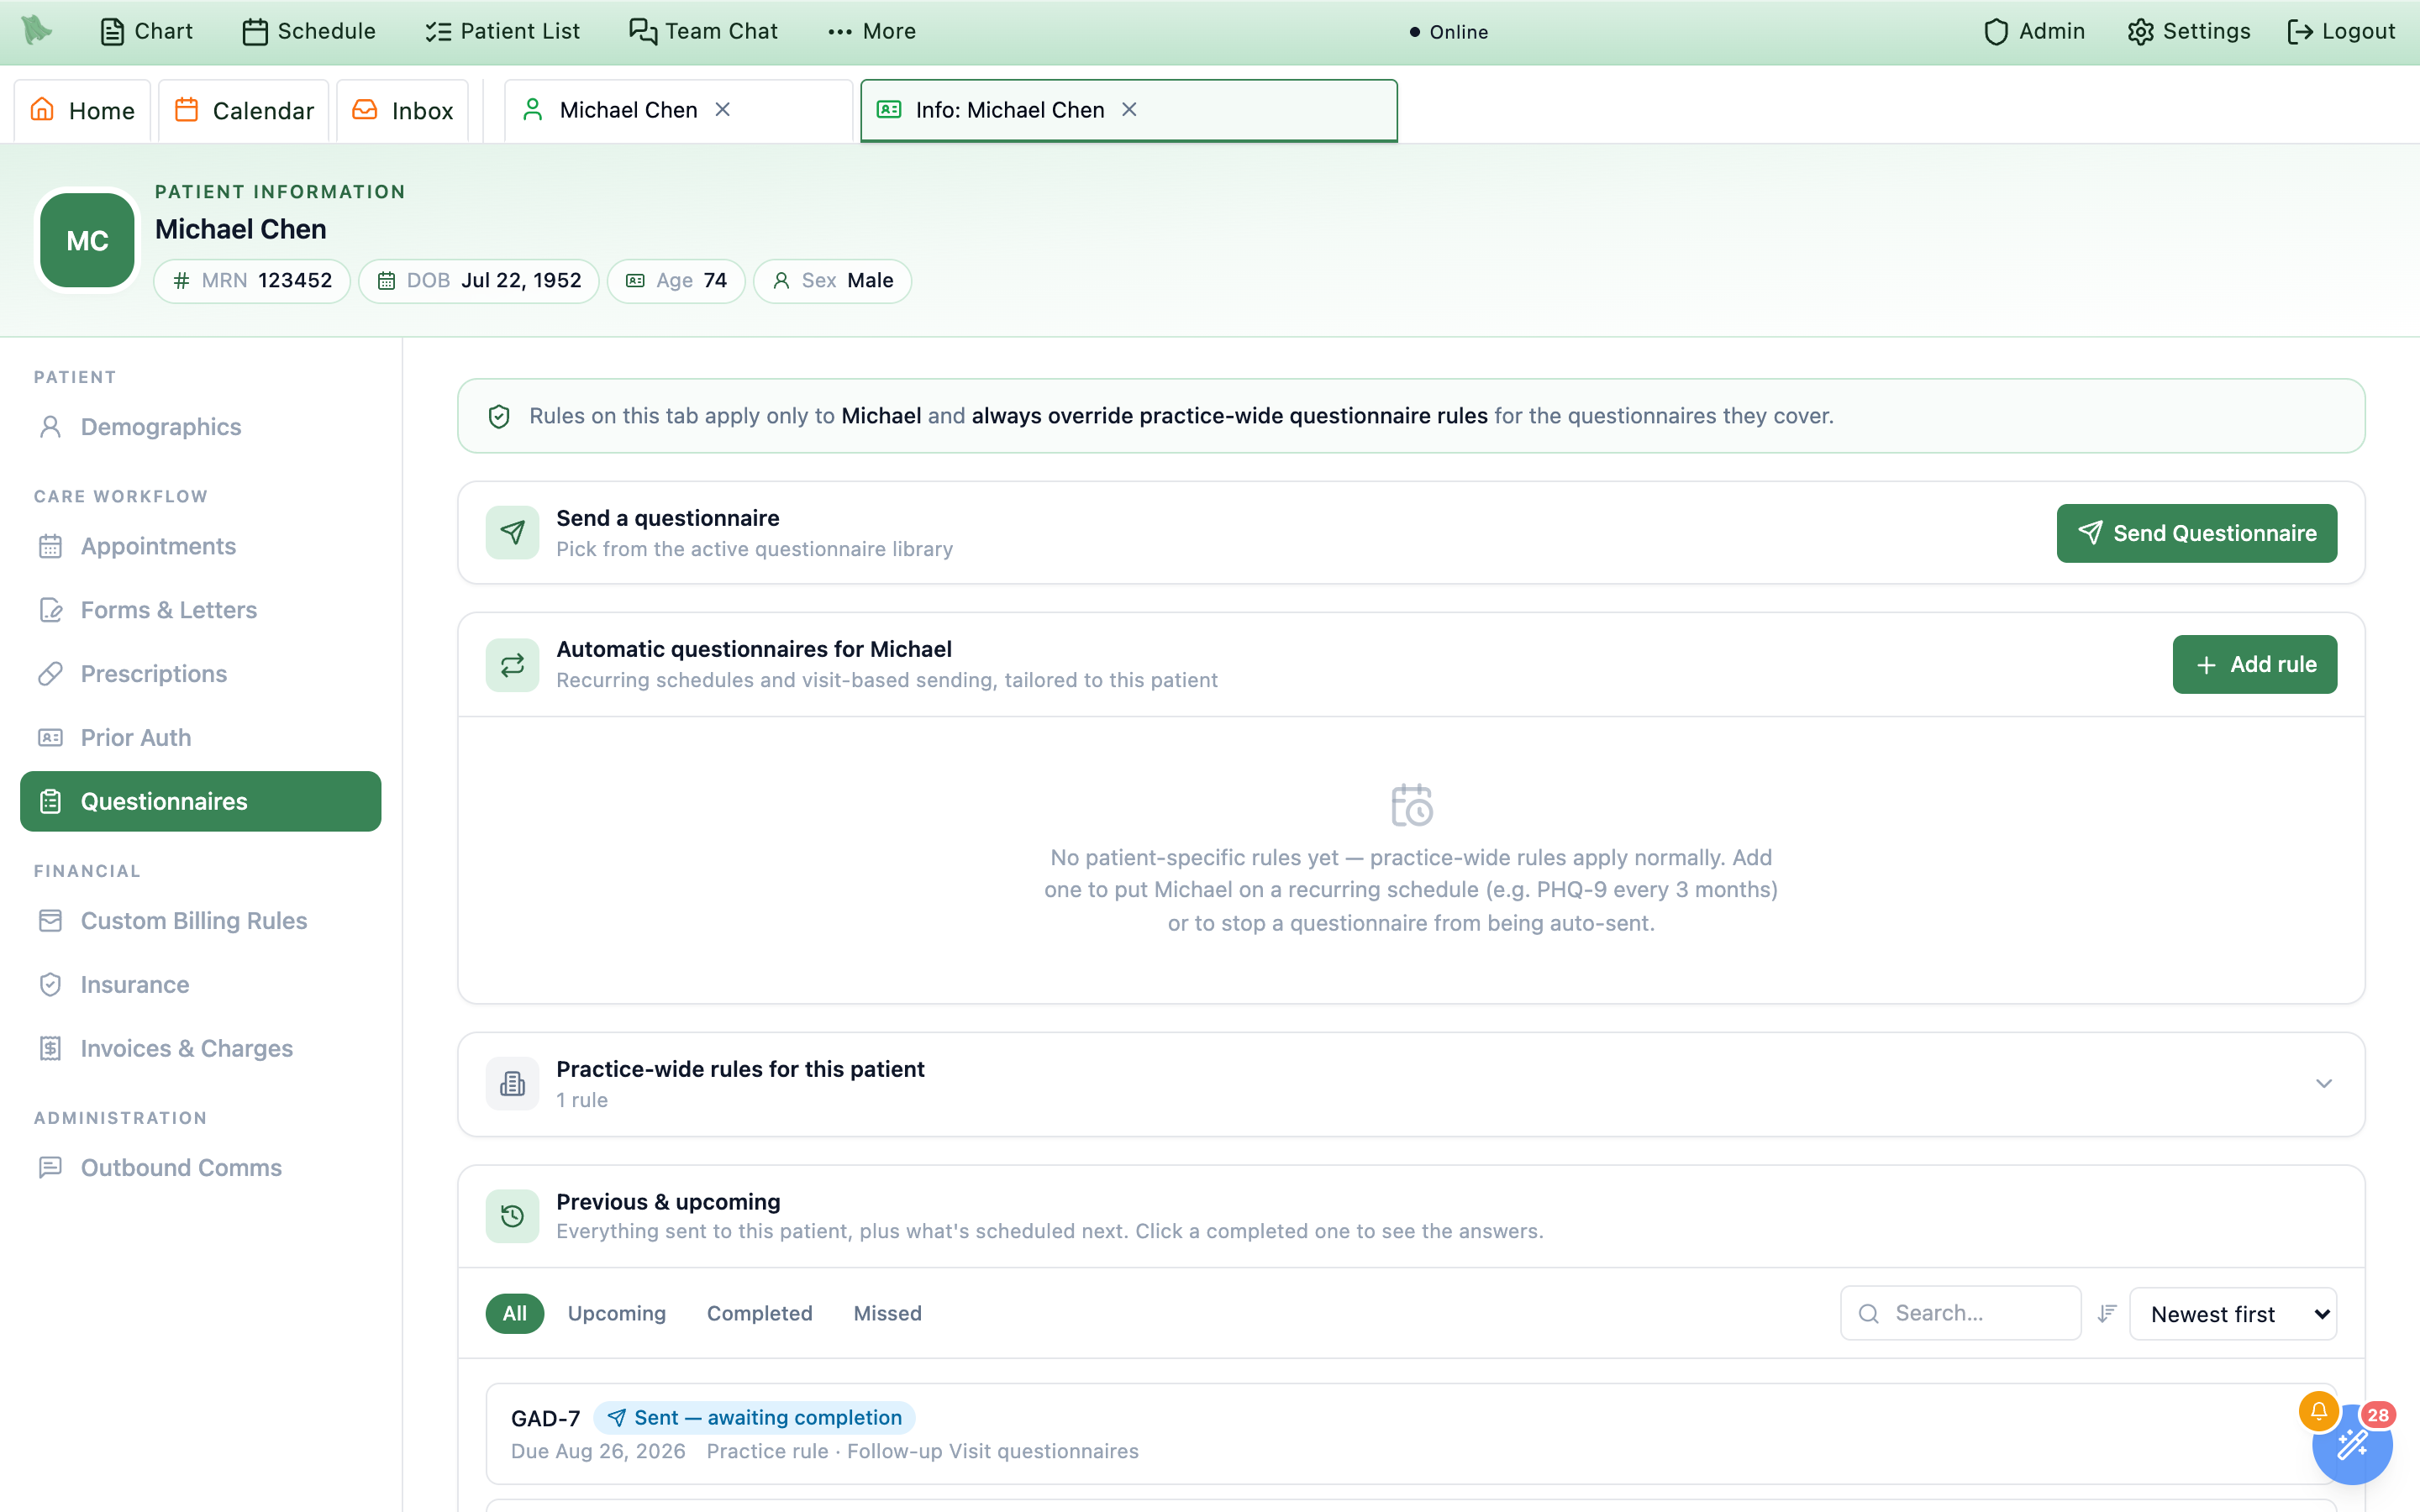
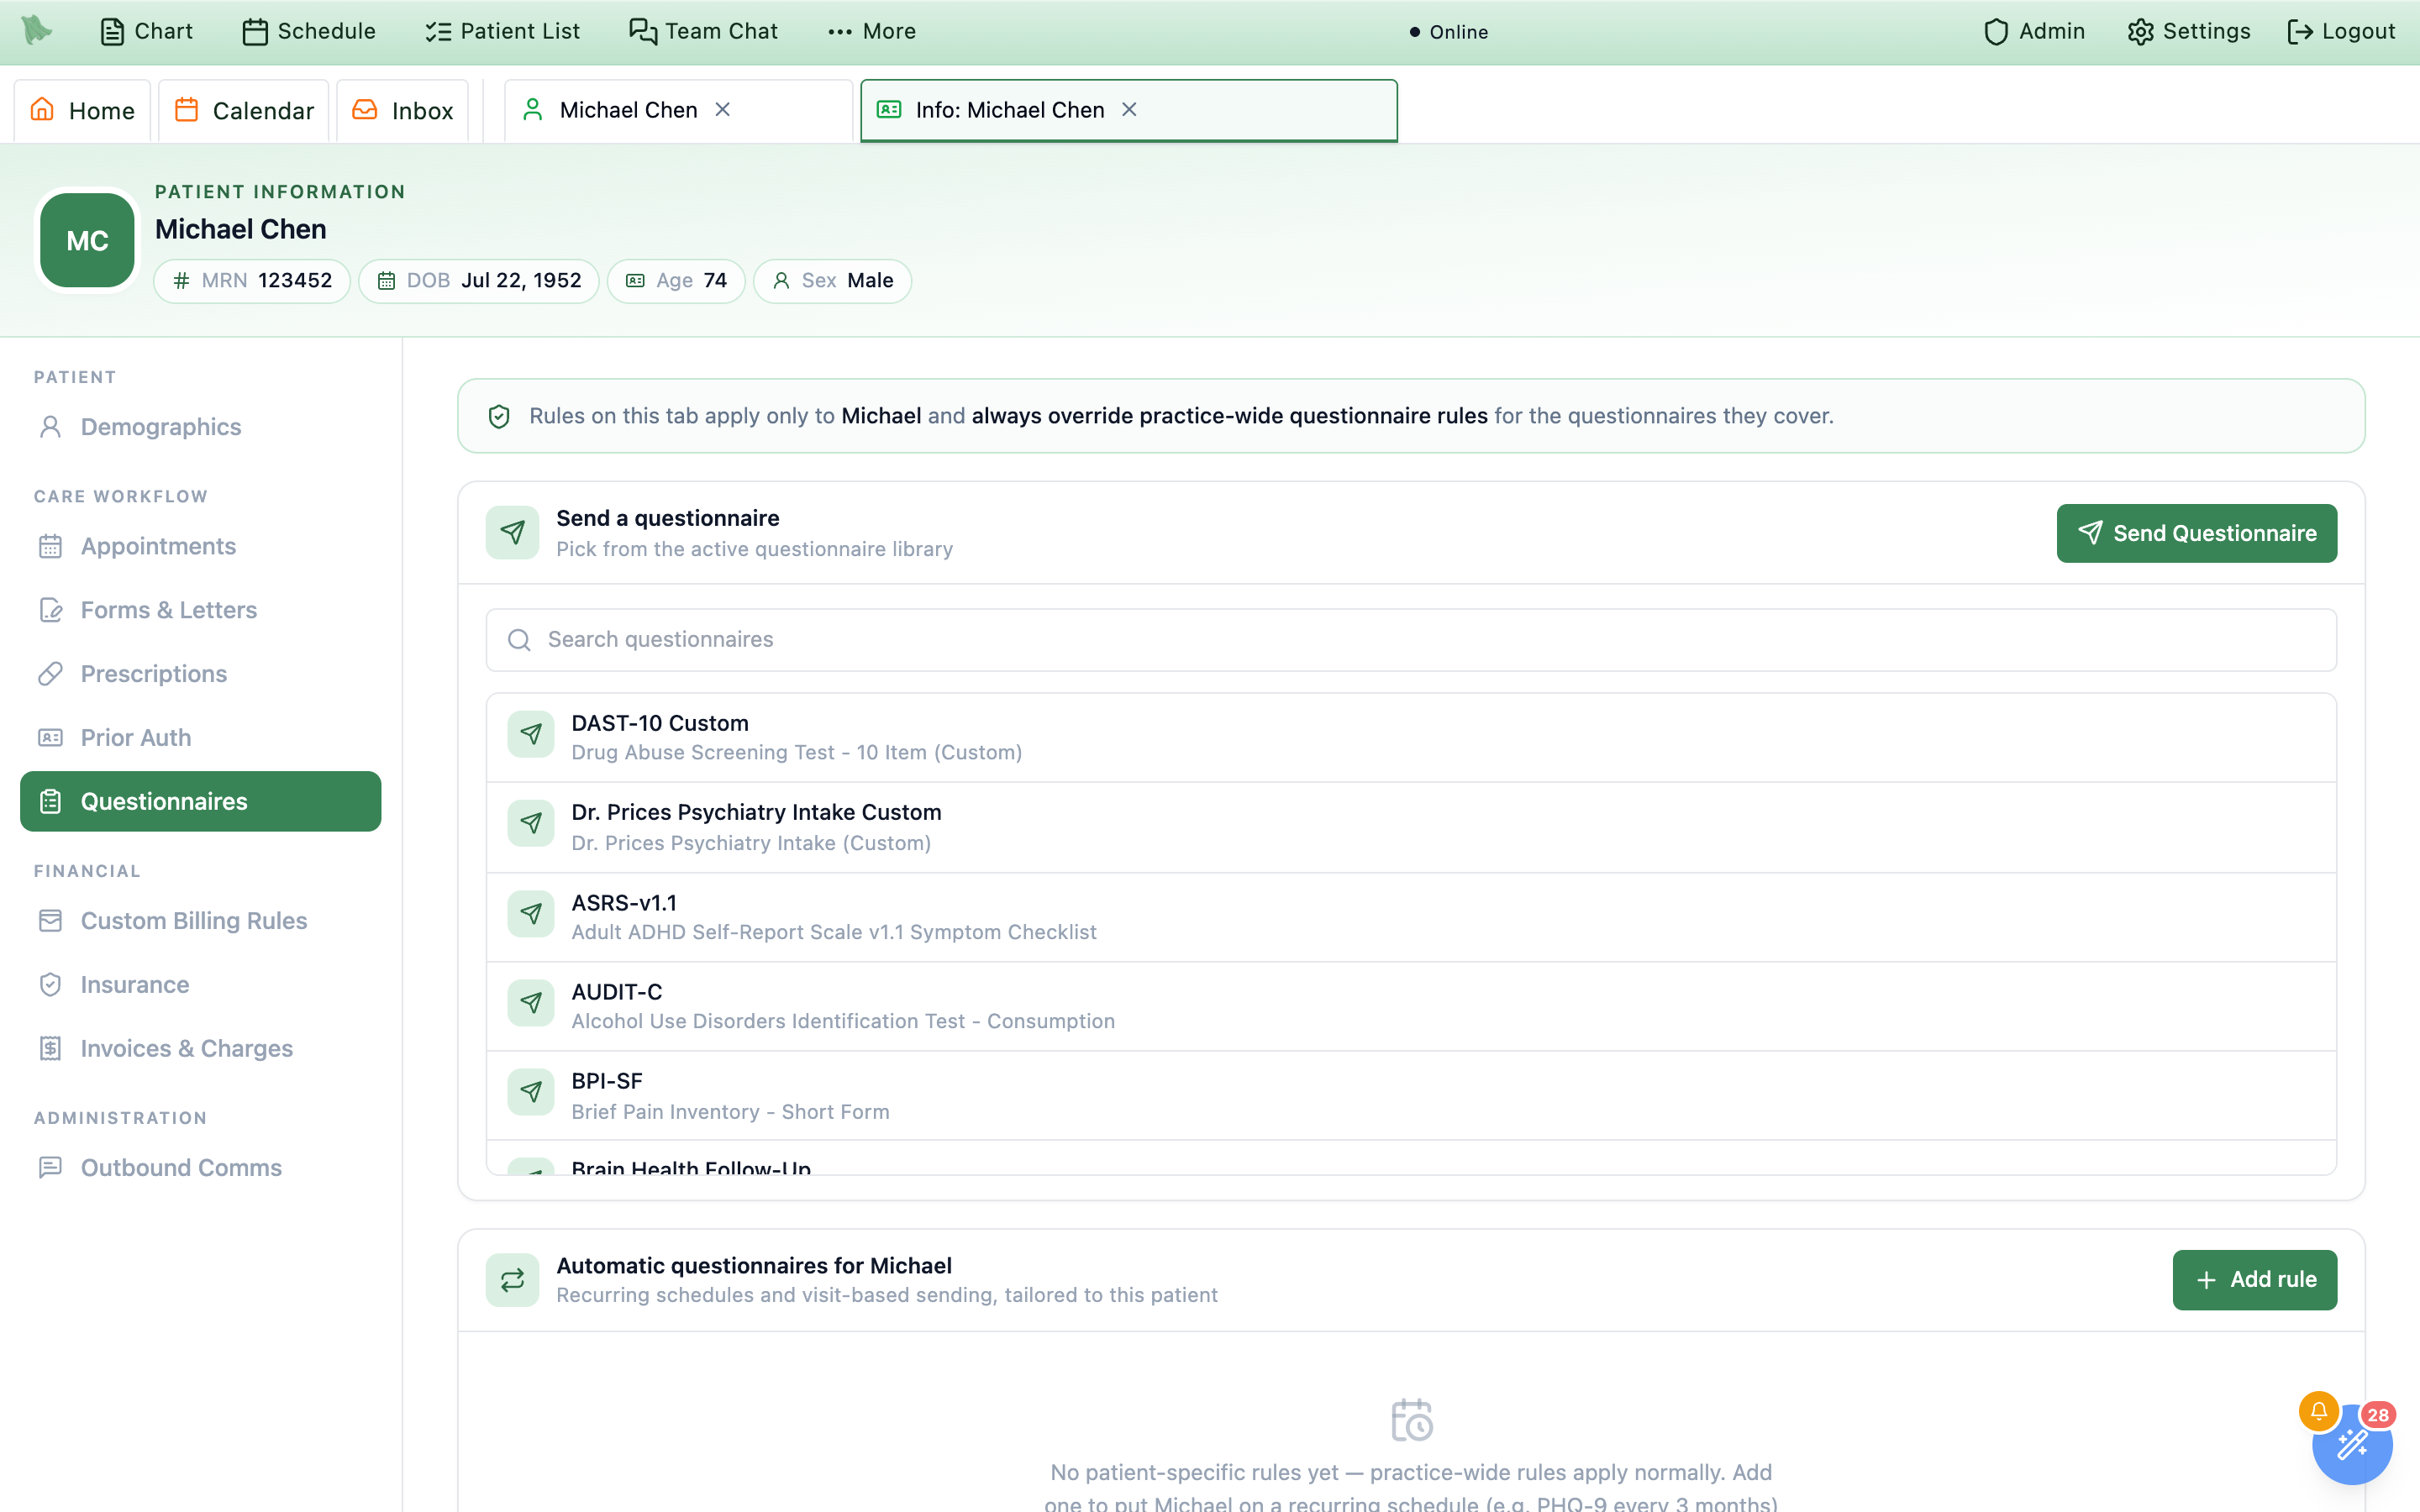
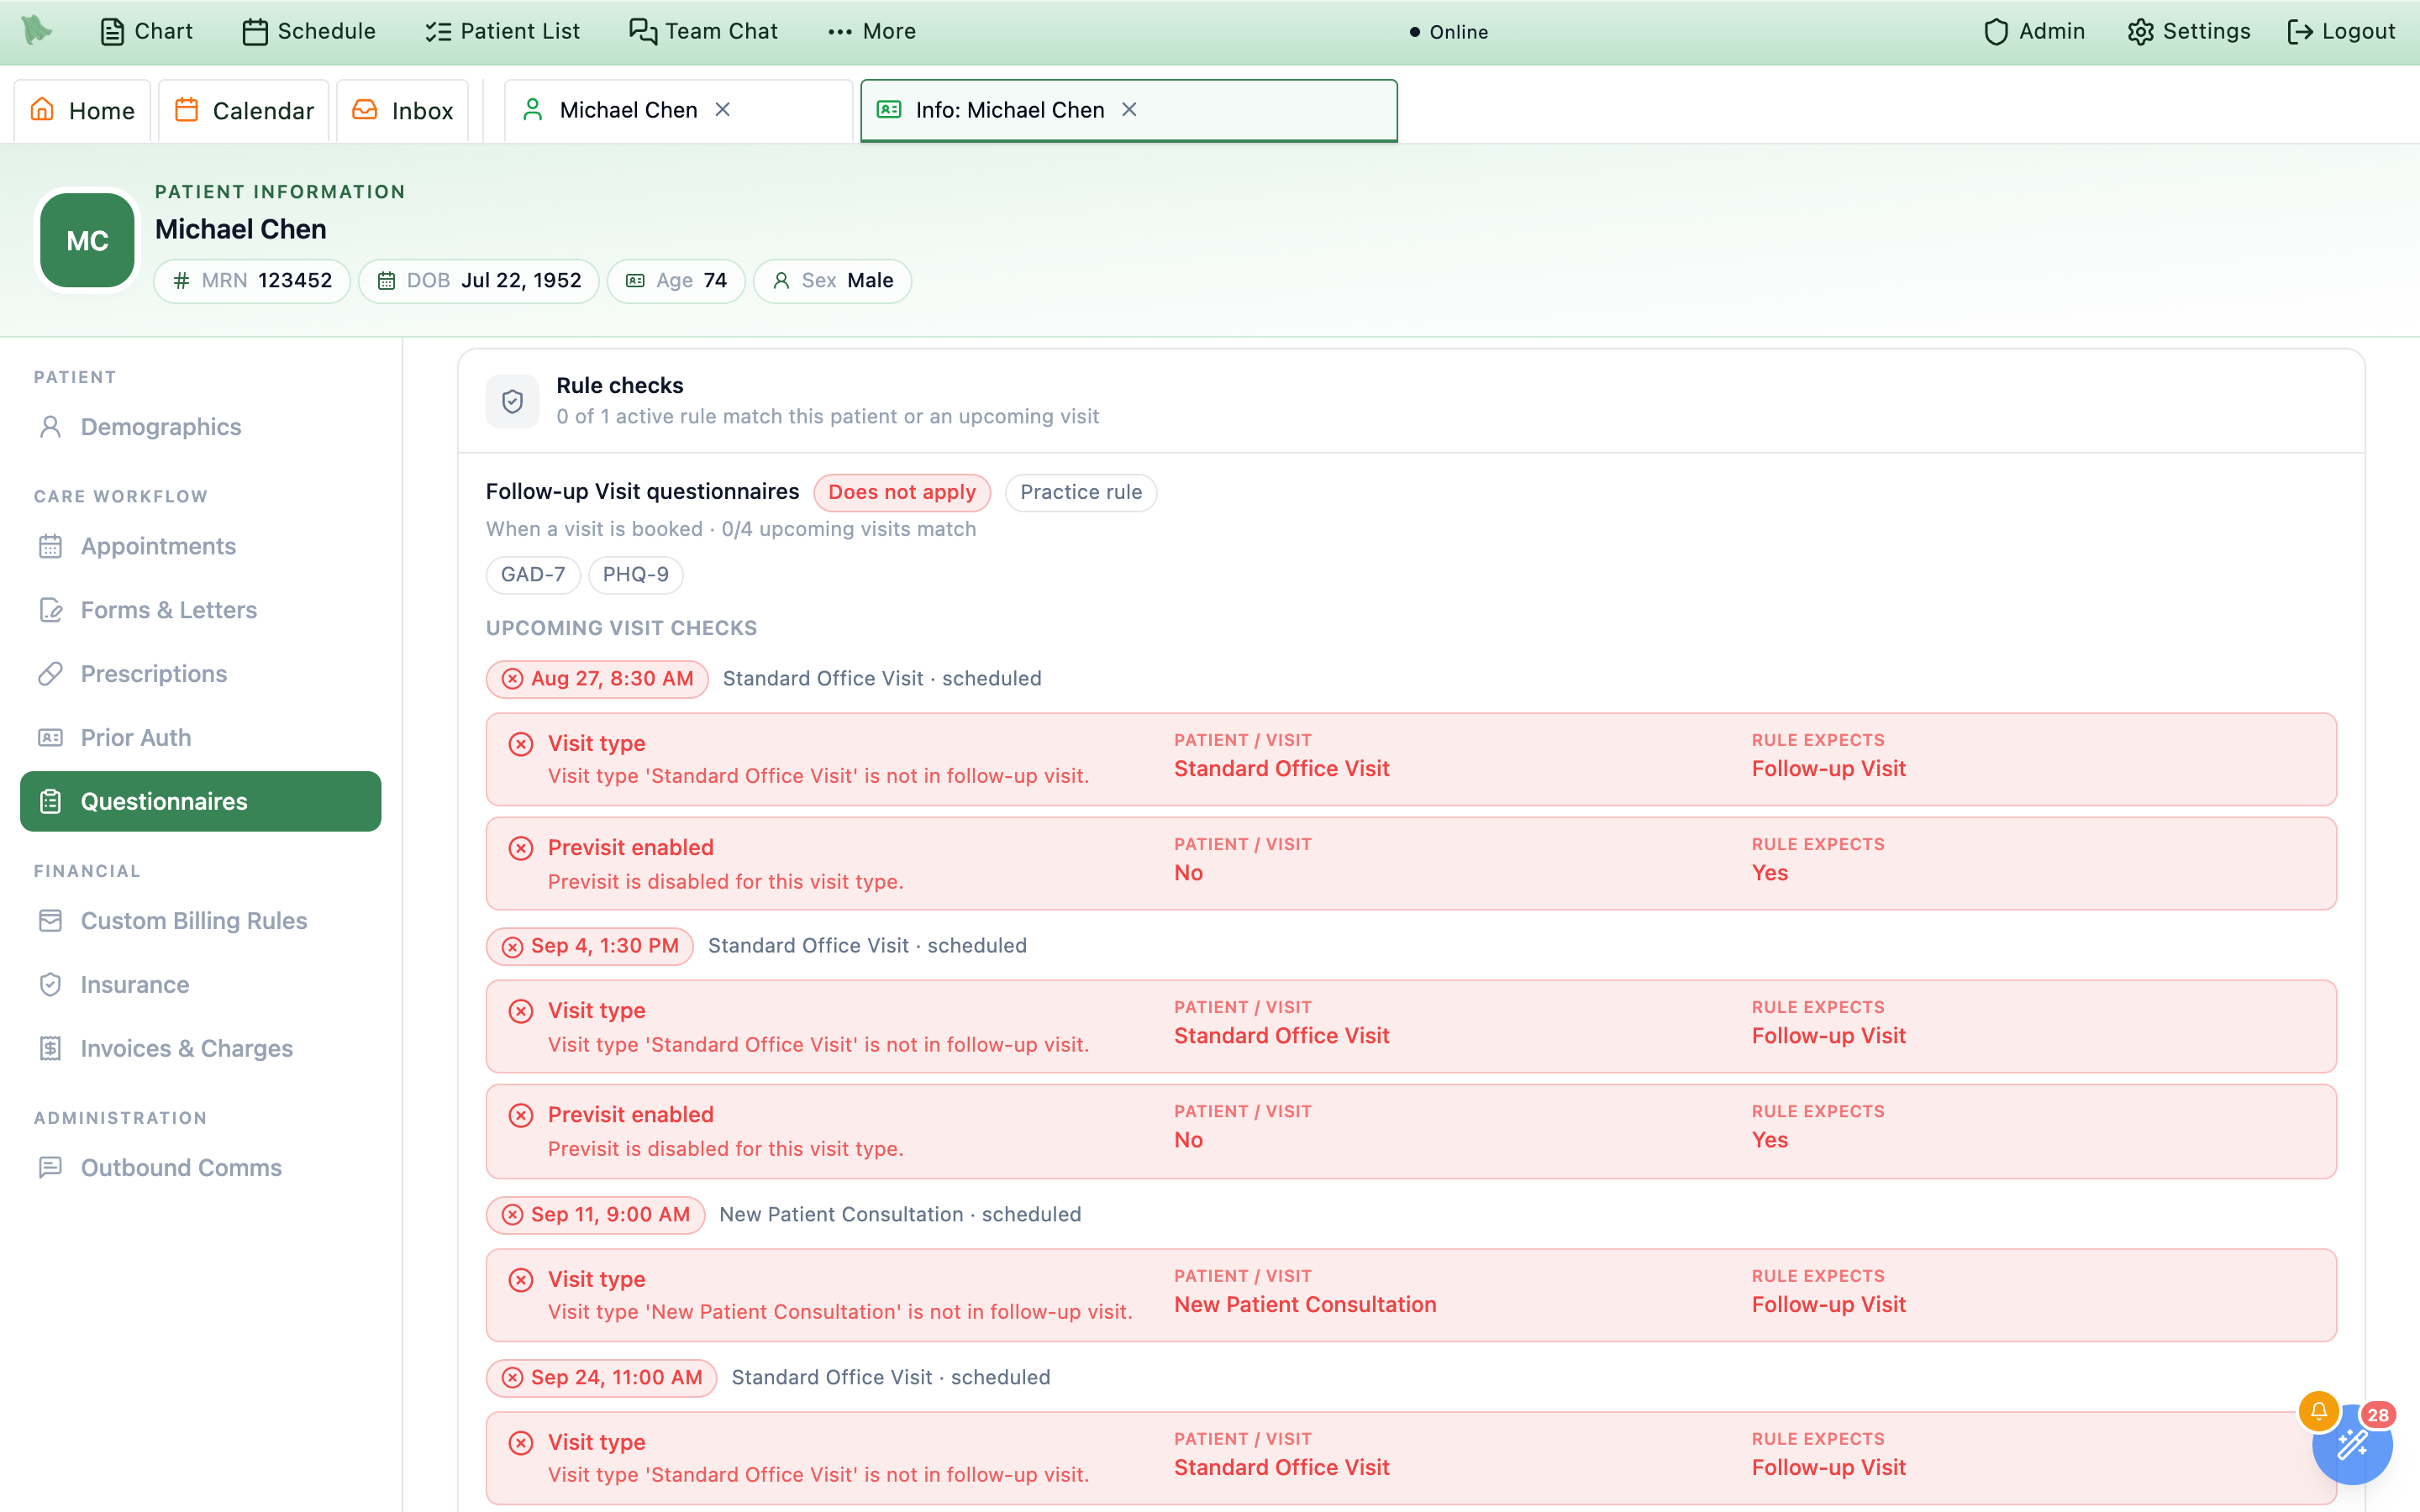
Rule checks shows the comparison that failed, per rule and per upcoming visit.Send a questionnaire, Send a form, Cancel and the whole rule editor need patient-management permission — physicians and admins have it by role, staff need it granted; without it the patient’s rules are read-only. Answers, scores, interpretations and safety flags need intake review or visit-note access (physicians, administrators, and staff who review intake or read visit notes); other staff, such as the front desk, still see which questionnaires were sent or completed and when, but opening the answers says “Your role can't see questionnaire answers or scores. Staff who review intake or read visit notes can.” Building the questionnaires themselves is covered in the questionnaire library.Stop automatic sending rule silently re-exposes the patient to every practice-wide rule it was blocking, so pause it instead if you only want a break.The whole prescribing trail for one patient
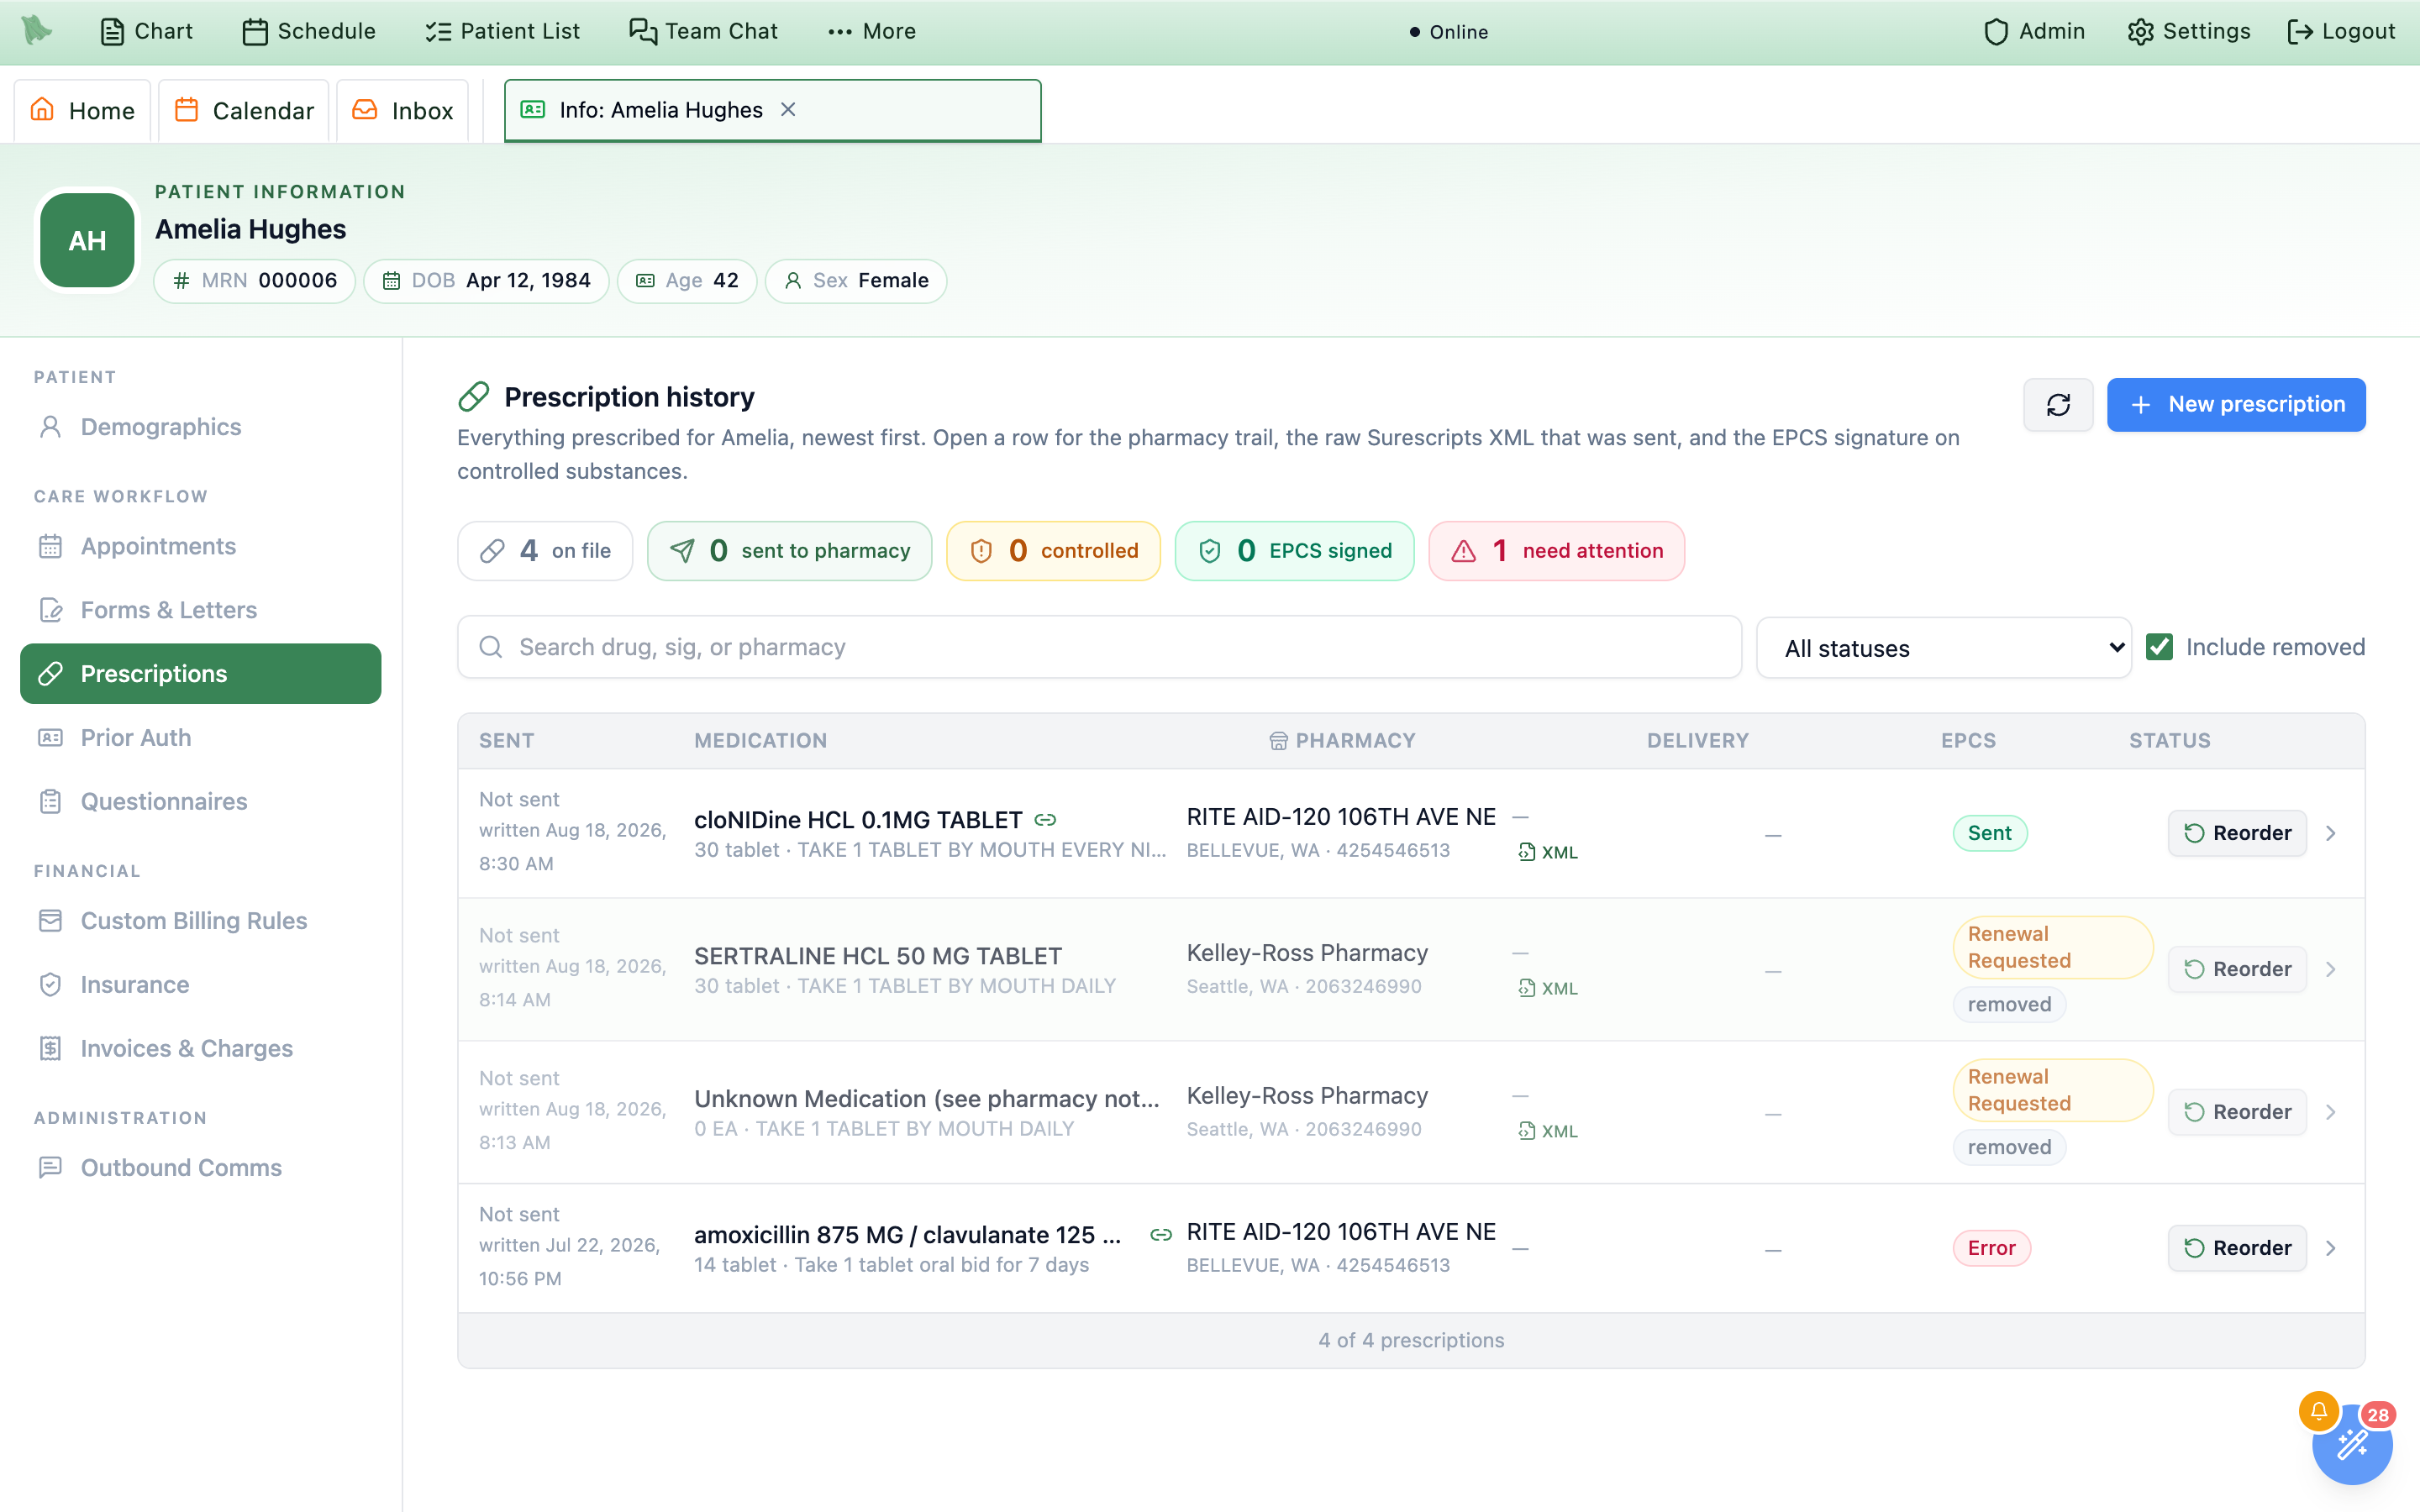
Prescriptions sits under Care workflow in the sidebar and answers the question the chart’s medication list can’t: did the pharmacy actually get it? The header reads Prescription history over “Everything prescribed for {first name}, newest first. Open a row for the pharmacy trail, the raw Surescripts XML that was sent, and the EPCS signature on controlled substances.” Admins, physicians, and staff holding prescription.view can read it; placing an order from here — New prescription or Reorder — is physician and admin only, and those buttons are simply absent for view-only staff rather than greyed out. Every row you open is recorded as a chart access. For the read-only medication list itself, see the Medications tab.
-
Read the counters first.
Five chips:
on file,sent to pharmacy,controlled,EPCS signed, andneed attention, the last shown only when it is above zero.need attentioncounts prescriptions inError,Denied, orPending signature, plus anything whose Surescripts reply came back as an error, failure, or denial. Thecontrolledchip is also a button: click it to filter the list to controlled substances, click again to release it. -
Narrow the list.
Search drug, sig, or pharmacymatches the drug description, the sig, and the pharmacy name;Filter by statusholds one status at a time, starting atAll statuses.Include removedis on by default, which is why cancelled and replaced prescriptions appear, faded, with a greyremovedchip. There is no sort control — the list is always newest-sent first, and long histories load 50 rows at a time as you scroll. -
Read a row.
Sentis the transmission time.Medicationis the drug — with an amberCII-style pill on controlled substances — over a line of quantity · refills · sig.Pharmacy,Delivery(the Surescripts status, a reply count, and anXMLlink),EPCS, andStatusfollow. -
When the
Sentcell saysNot sent. The prescription has no send time and no transmission date on record — it was printed, faxed, never transmitted, or is still waiting on a signature. A smallerwritten {date, time}line underneath tells you when it was created, the Overview fieldSent to pharmacyreadsNot transmitted, and the Surescripts tab says “No Surescripts messages recorded for this prescription (it may have been printed, faxed, or never transmitted).”
| Status | What it means |
|---|---|
Draft / Pending Signature | Written but not signed. Nothing has left the practice. |
Signed | Signed but not sent — the filter spells this out as Signed, not sent. |
Sent | Transmitted to the pharmacy. |
Active | The pharmacy confirmed it. |
Renewal Requested / Change Requested | The pharmacy asked for a renewal or a change; the prescriber has yet to answer. |
Cancellation Pending | You asked the pharmacy to cancel it and no answer has come back yet. Filter by status lists it as Cancellation pending. |
Error / Denied | Transmission failed or the request was refused — these drive need attention. |
Completed / Discontinued / Canceled | Finished, stopped, or withdrawn. |
removed | A grey companion chip, not a status: the row was cancelled or replaced, and shows only because Include removed is ticked. |
Clicking a row opens the detail dialog; clicking its XML link opens the same dialog straight onto the Surescripts trail. The dialog is titled with the drug and subtitled Prescribed by {name} · written {date}, over a strip of pills — the status, Surescripts: {status}, Controlled, the EPCS state, and In medication list or Not in medication list. Four sections sit below it, the last three carrying a count badge:
Overview & Timeline
Overview is three field grids: the product (Drug, Quantity, Days supply, Sig, Refills, RxCUI, NDC), the parties (Pharmacy with its NCPDP and address, Prescriber with NPI, and the Encounter it belongs to — or Standalone — not tied to an encounter), and the transmission facts (Sent to pharmacy, Written, Signed, Message ID, and Lineage when this prescription replaces or was replaced by another). Timeline is the lifecycle audit — each event, its before → after status, the time, and who did it.
Surescripts & XML and EPCS signing
Surescripts & XML is the ground truth for delivery: one card per message with a Sent or Received direction pill, the message type, an ok or error pill, the message IDs, and View raw XML to read exactly what went over the wire. EPCS signing shows the signature on a controlled prescription — signed at, device, signer, signature hash, and each two-factor session. On anything else it reads “Not a controlled substance — no EPCS two-factor signature is required.” See EPCS for the signing ceremony itself.
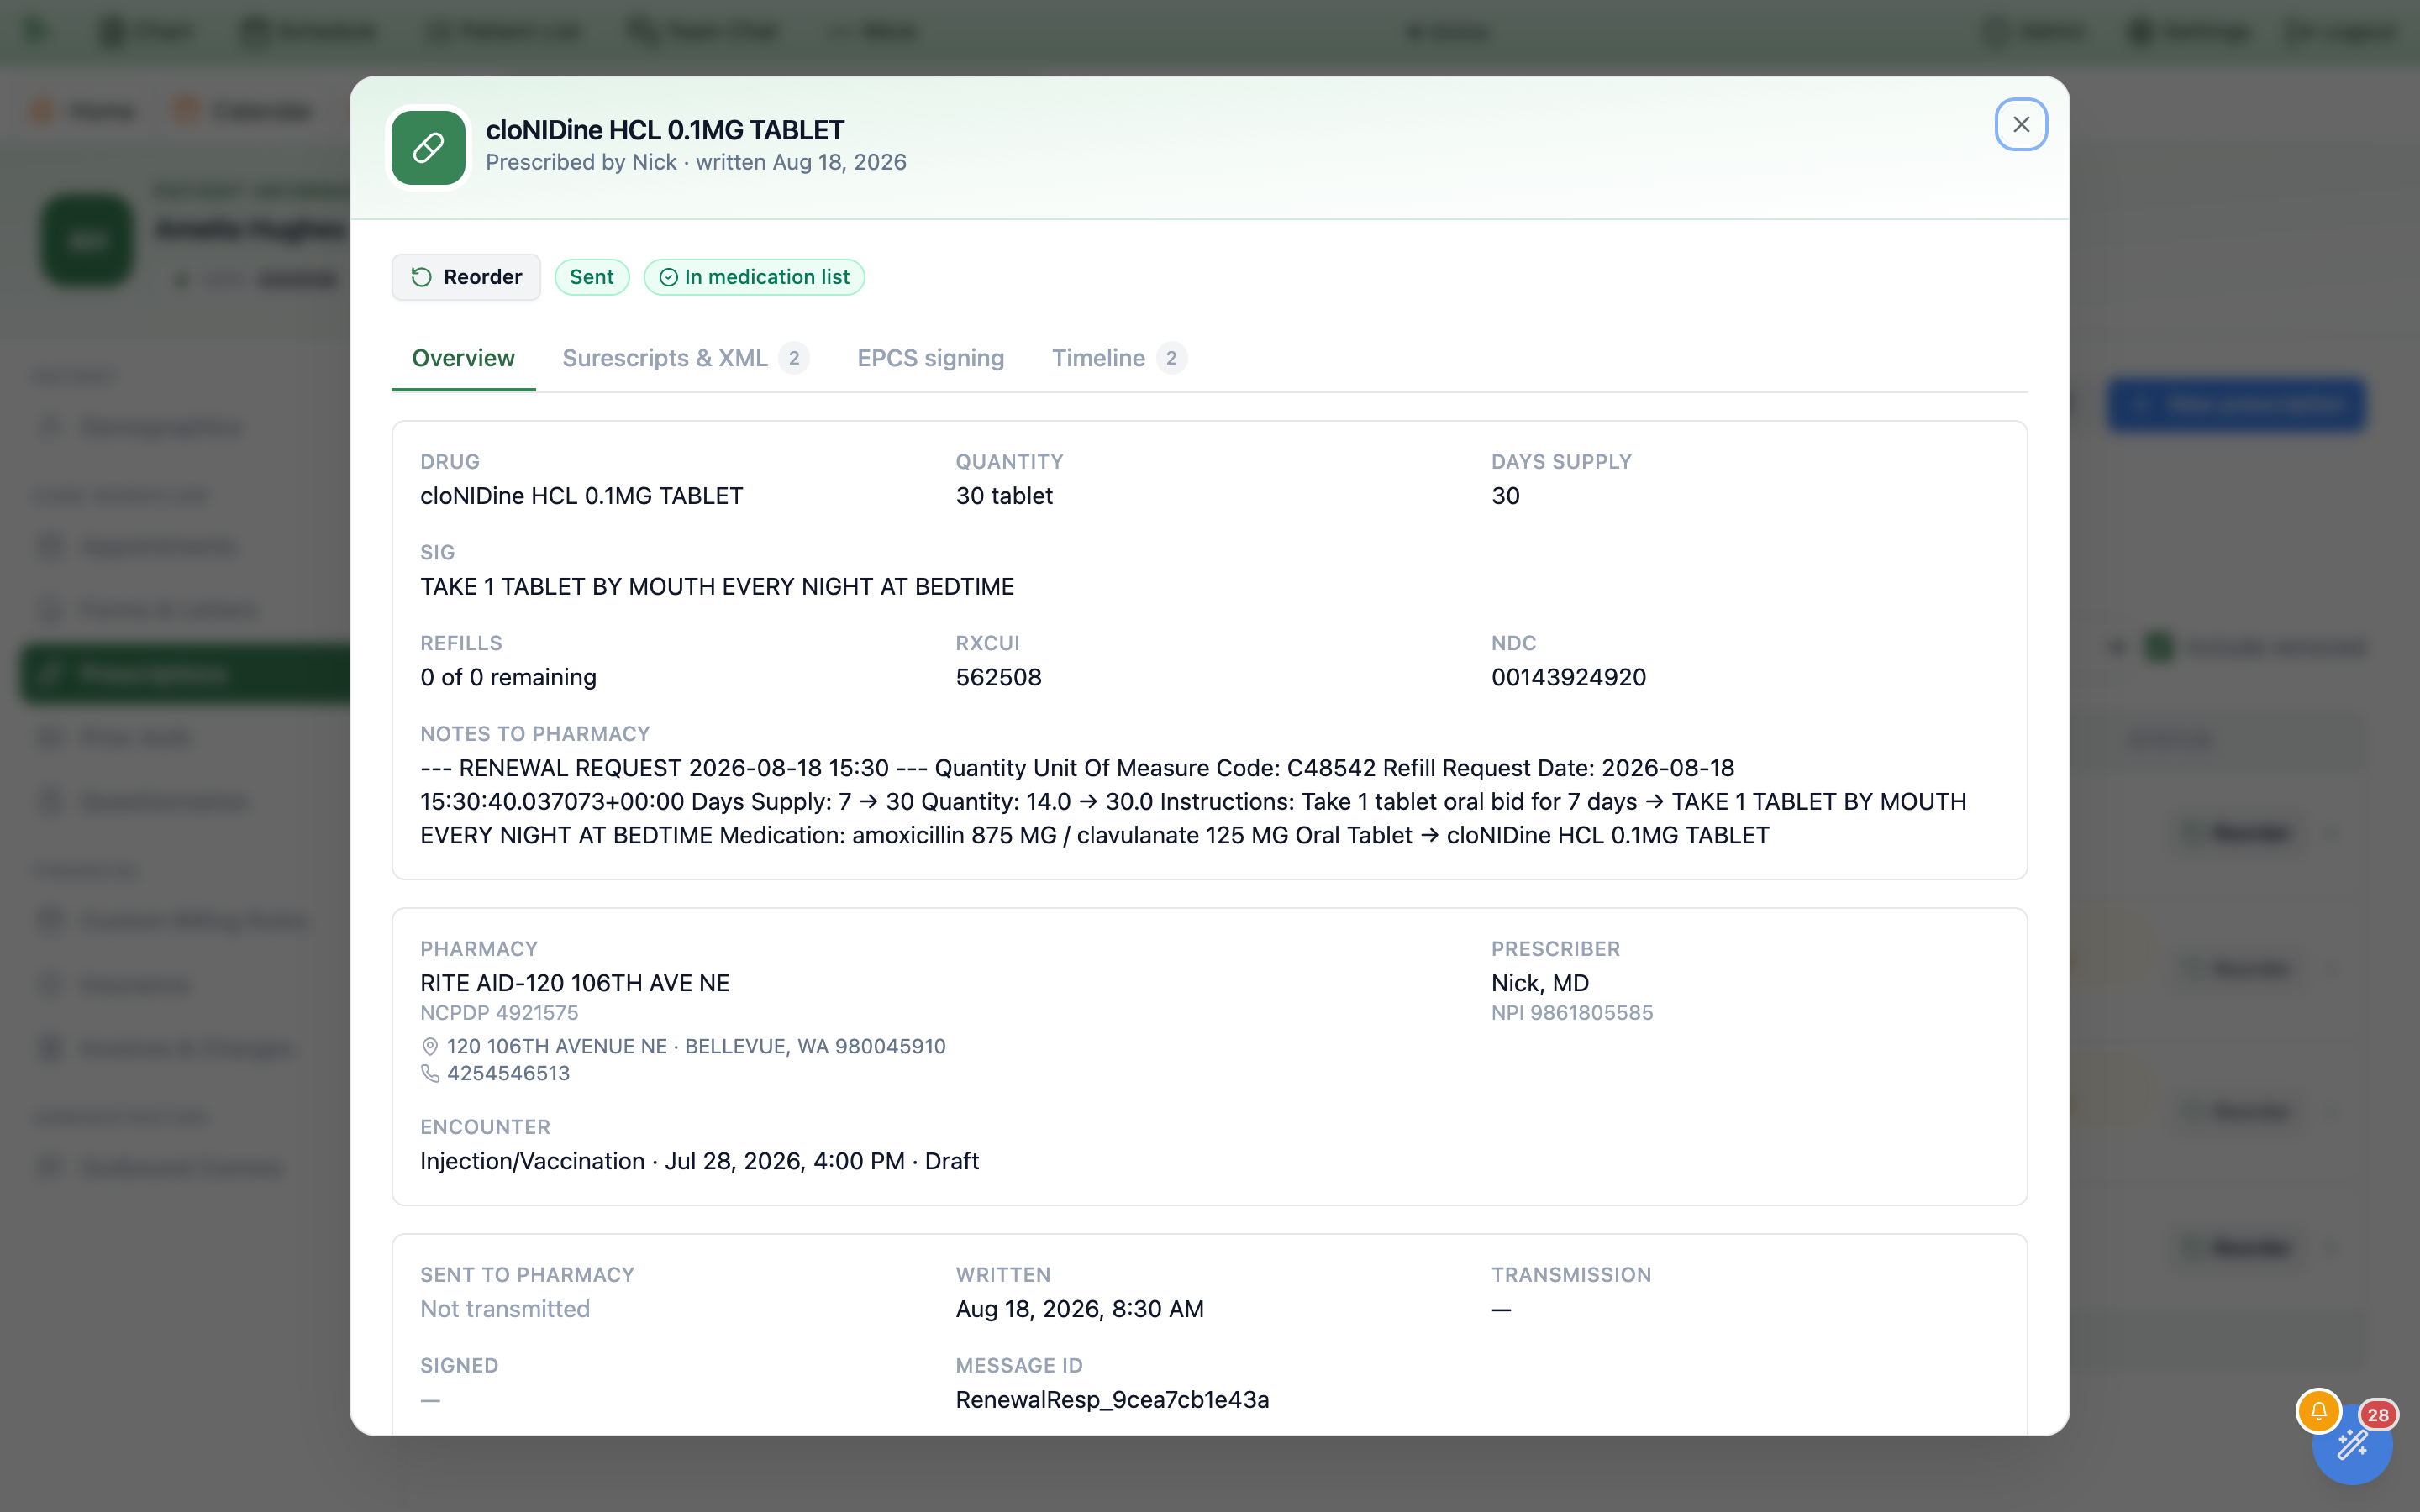
Overview. Reorder is the first control in the status strip.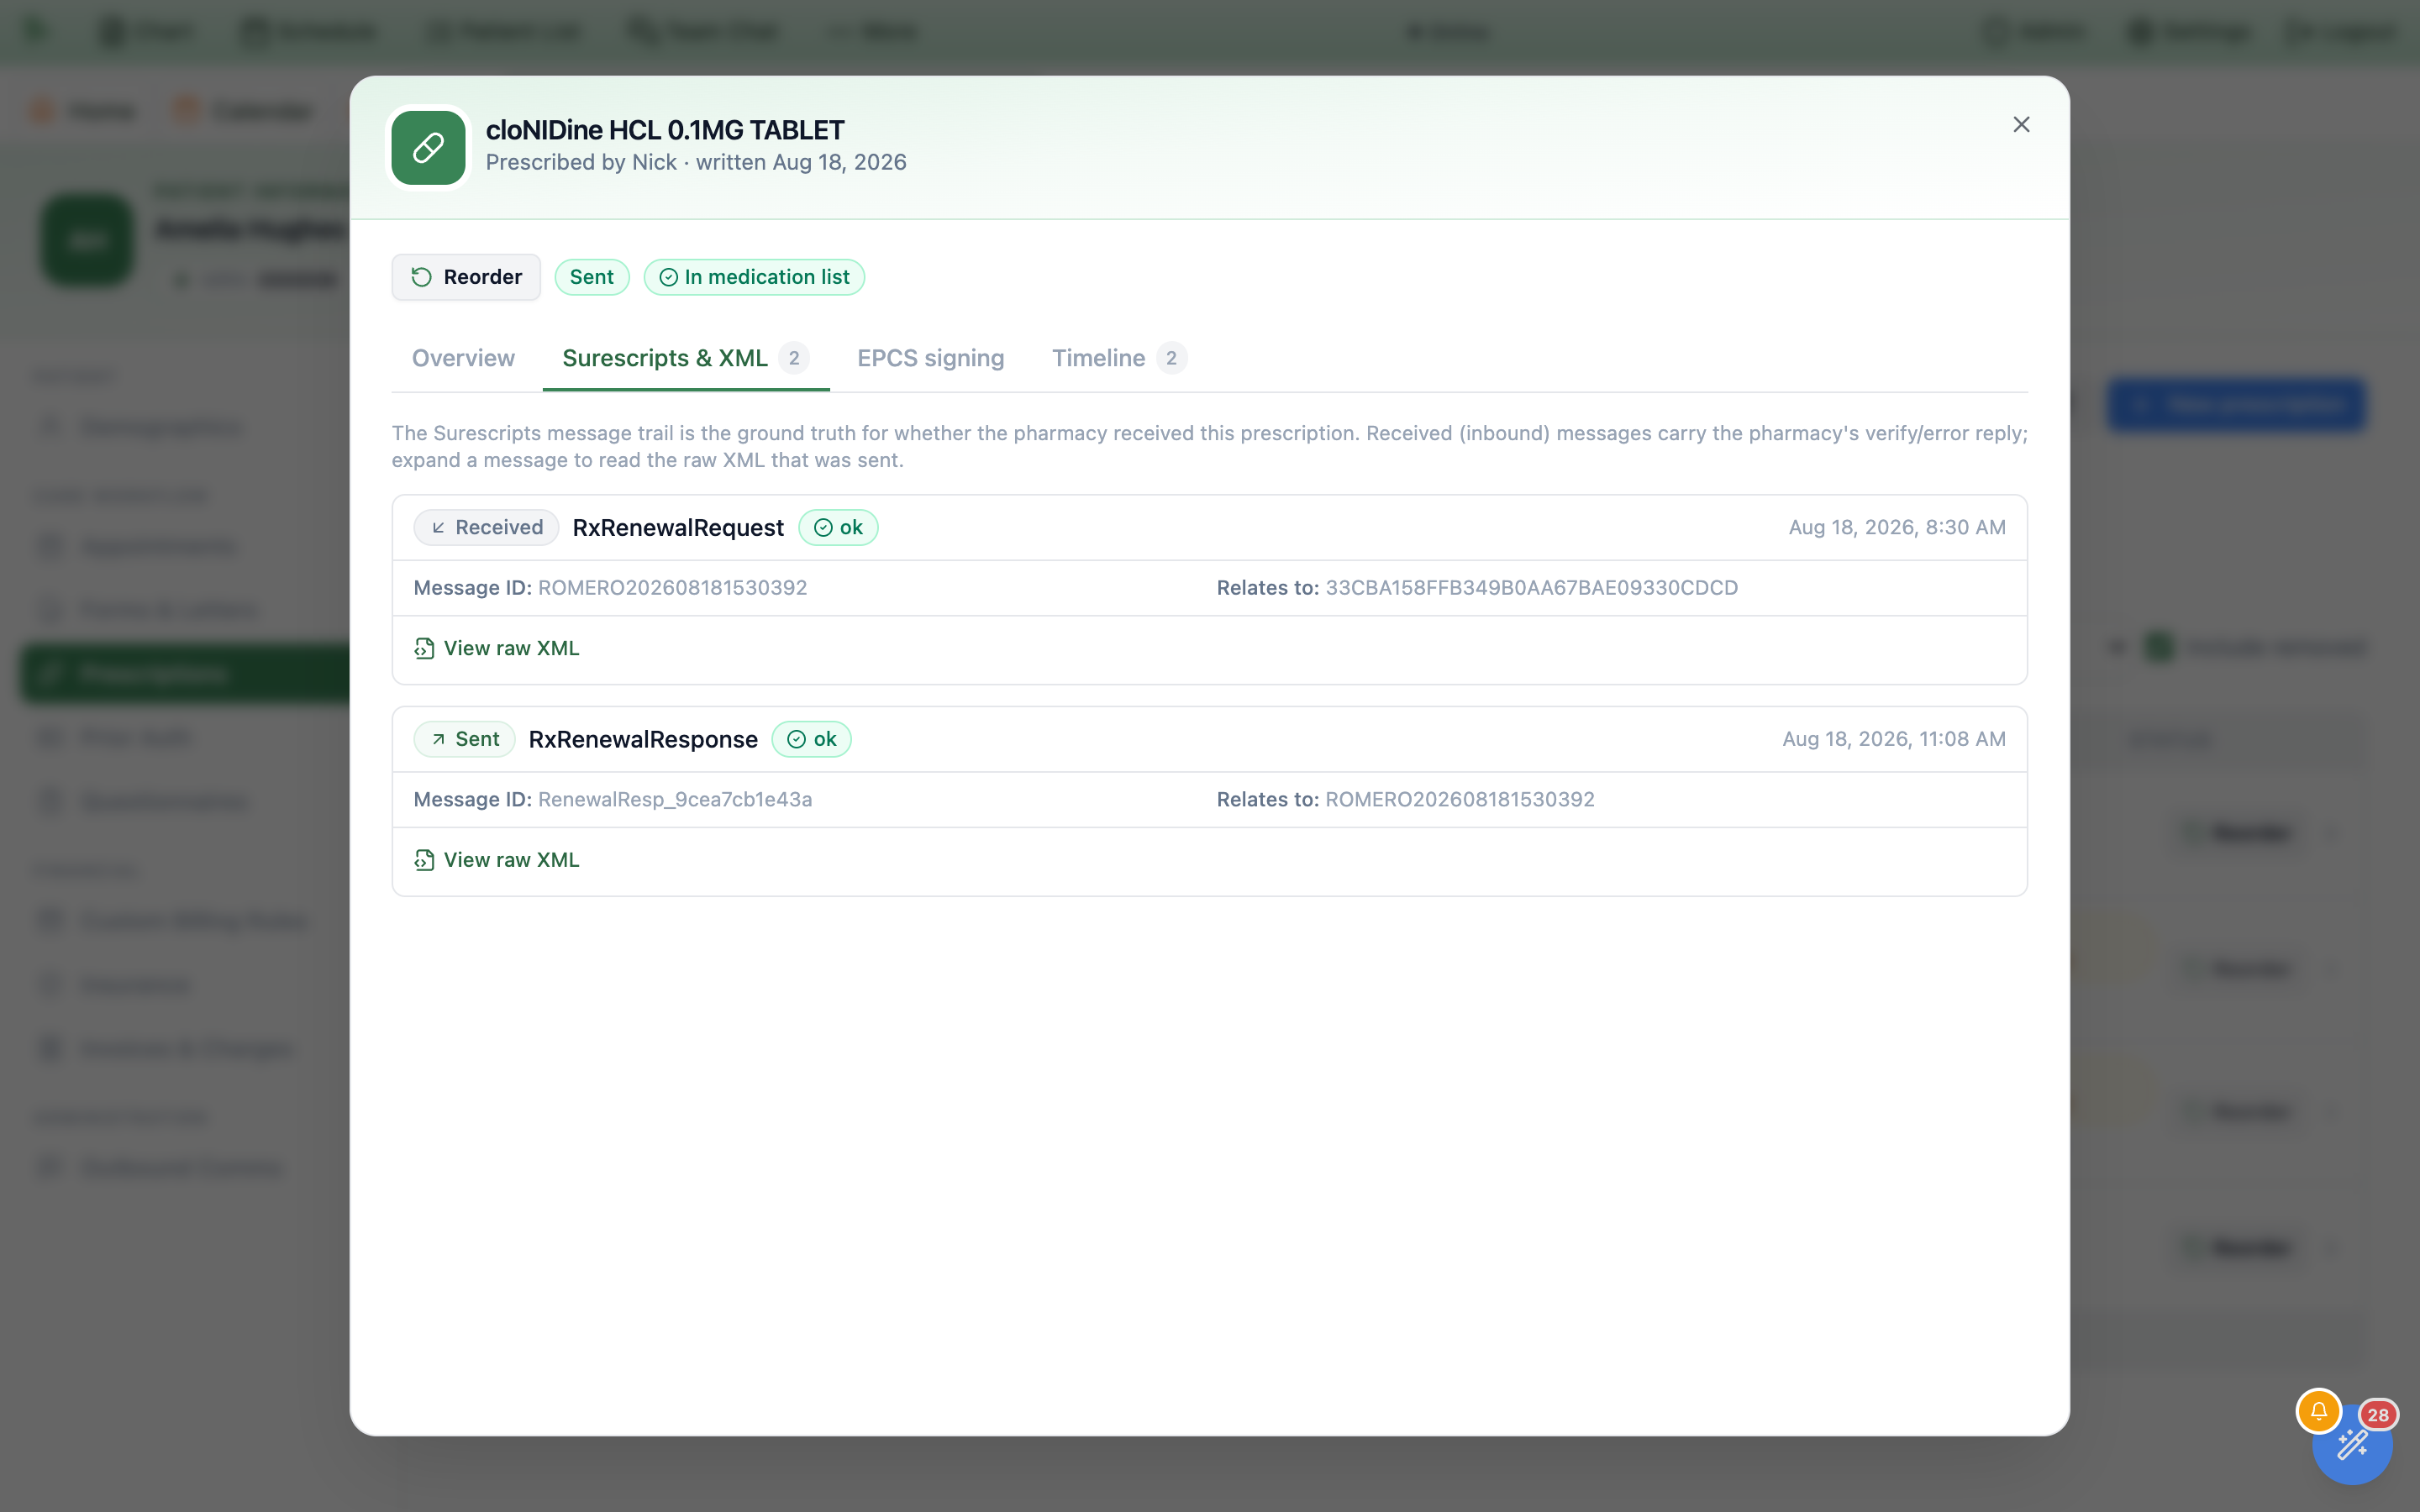
Received rows carry the pharmacy’s reply; View raw XML shows what was actually sent.Reorder appears on every row and again at the top of the detail dialog. It opens the ordinary prescription editor with the medication dialog already showing a new draft titled Reorder · {drug}. Carried over: the drug identity (NDC, RxCUI, DEA schedule), quantity, units, refills, days supply, notes to pharmacy, the sig — rebuilt as structured fields, Extra instructions included, where dose, route, and frequency can be represented, otherwise kept verbatim as free text — and the diagnoses from the original, so the send gate is already satisfied unless you change them. For a controlled substance, directions a prescriber wrote out in Hero reopen word for word; directions from anywhere else, such as the medication list or a refill request, open in the fields for you to fill in. Review the sig, quantity, and refills, confirm the diagnosis, then finish through the normal prescribing flow. If the seed can’t be fetched you get a Could not start the reorder toast and the button is usable again straight away.
Reorder does not resend the old prescription. It always issues a brand-new one with a fresh identity, so the previous Sent status can never carry over — and nothing reaches the pharmacy until you sign and send in the order editor, controlled substances through EPCS. To chase a prescription that failed rather than repeat one that worked, start from Prescription status & errors.Include removed to see the live picture. Because it starts ticked, superseded renewals and cancelled prescriptions are listed by default — useful for an audit, misleading if you are counting what the patient is actually taking.Cancel a prescription
A prescription that has already gone to the pharmacy can be recalled from here: Cancel sits beside Reorder on the row, and again in the status strip at the top of the detail dialog. It is offered to exactly the accounts that may place an order — physicians, and admins who hold a prescriber profile — and only where a cancellation can actually reach somewhere. A prescription that was printed, faxed, or never transmitted has nothing at a pharmacy to recall, so its row carries no Cancel at all; nor does one that is already cancelled, one whose cancellation is already on its way, or one that has been replaced by a newer prescription — there it is the replacement that must be cancelled.
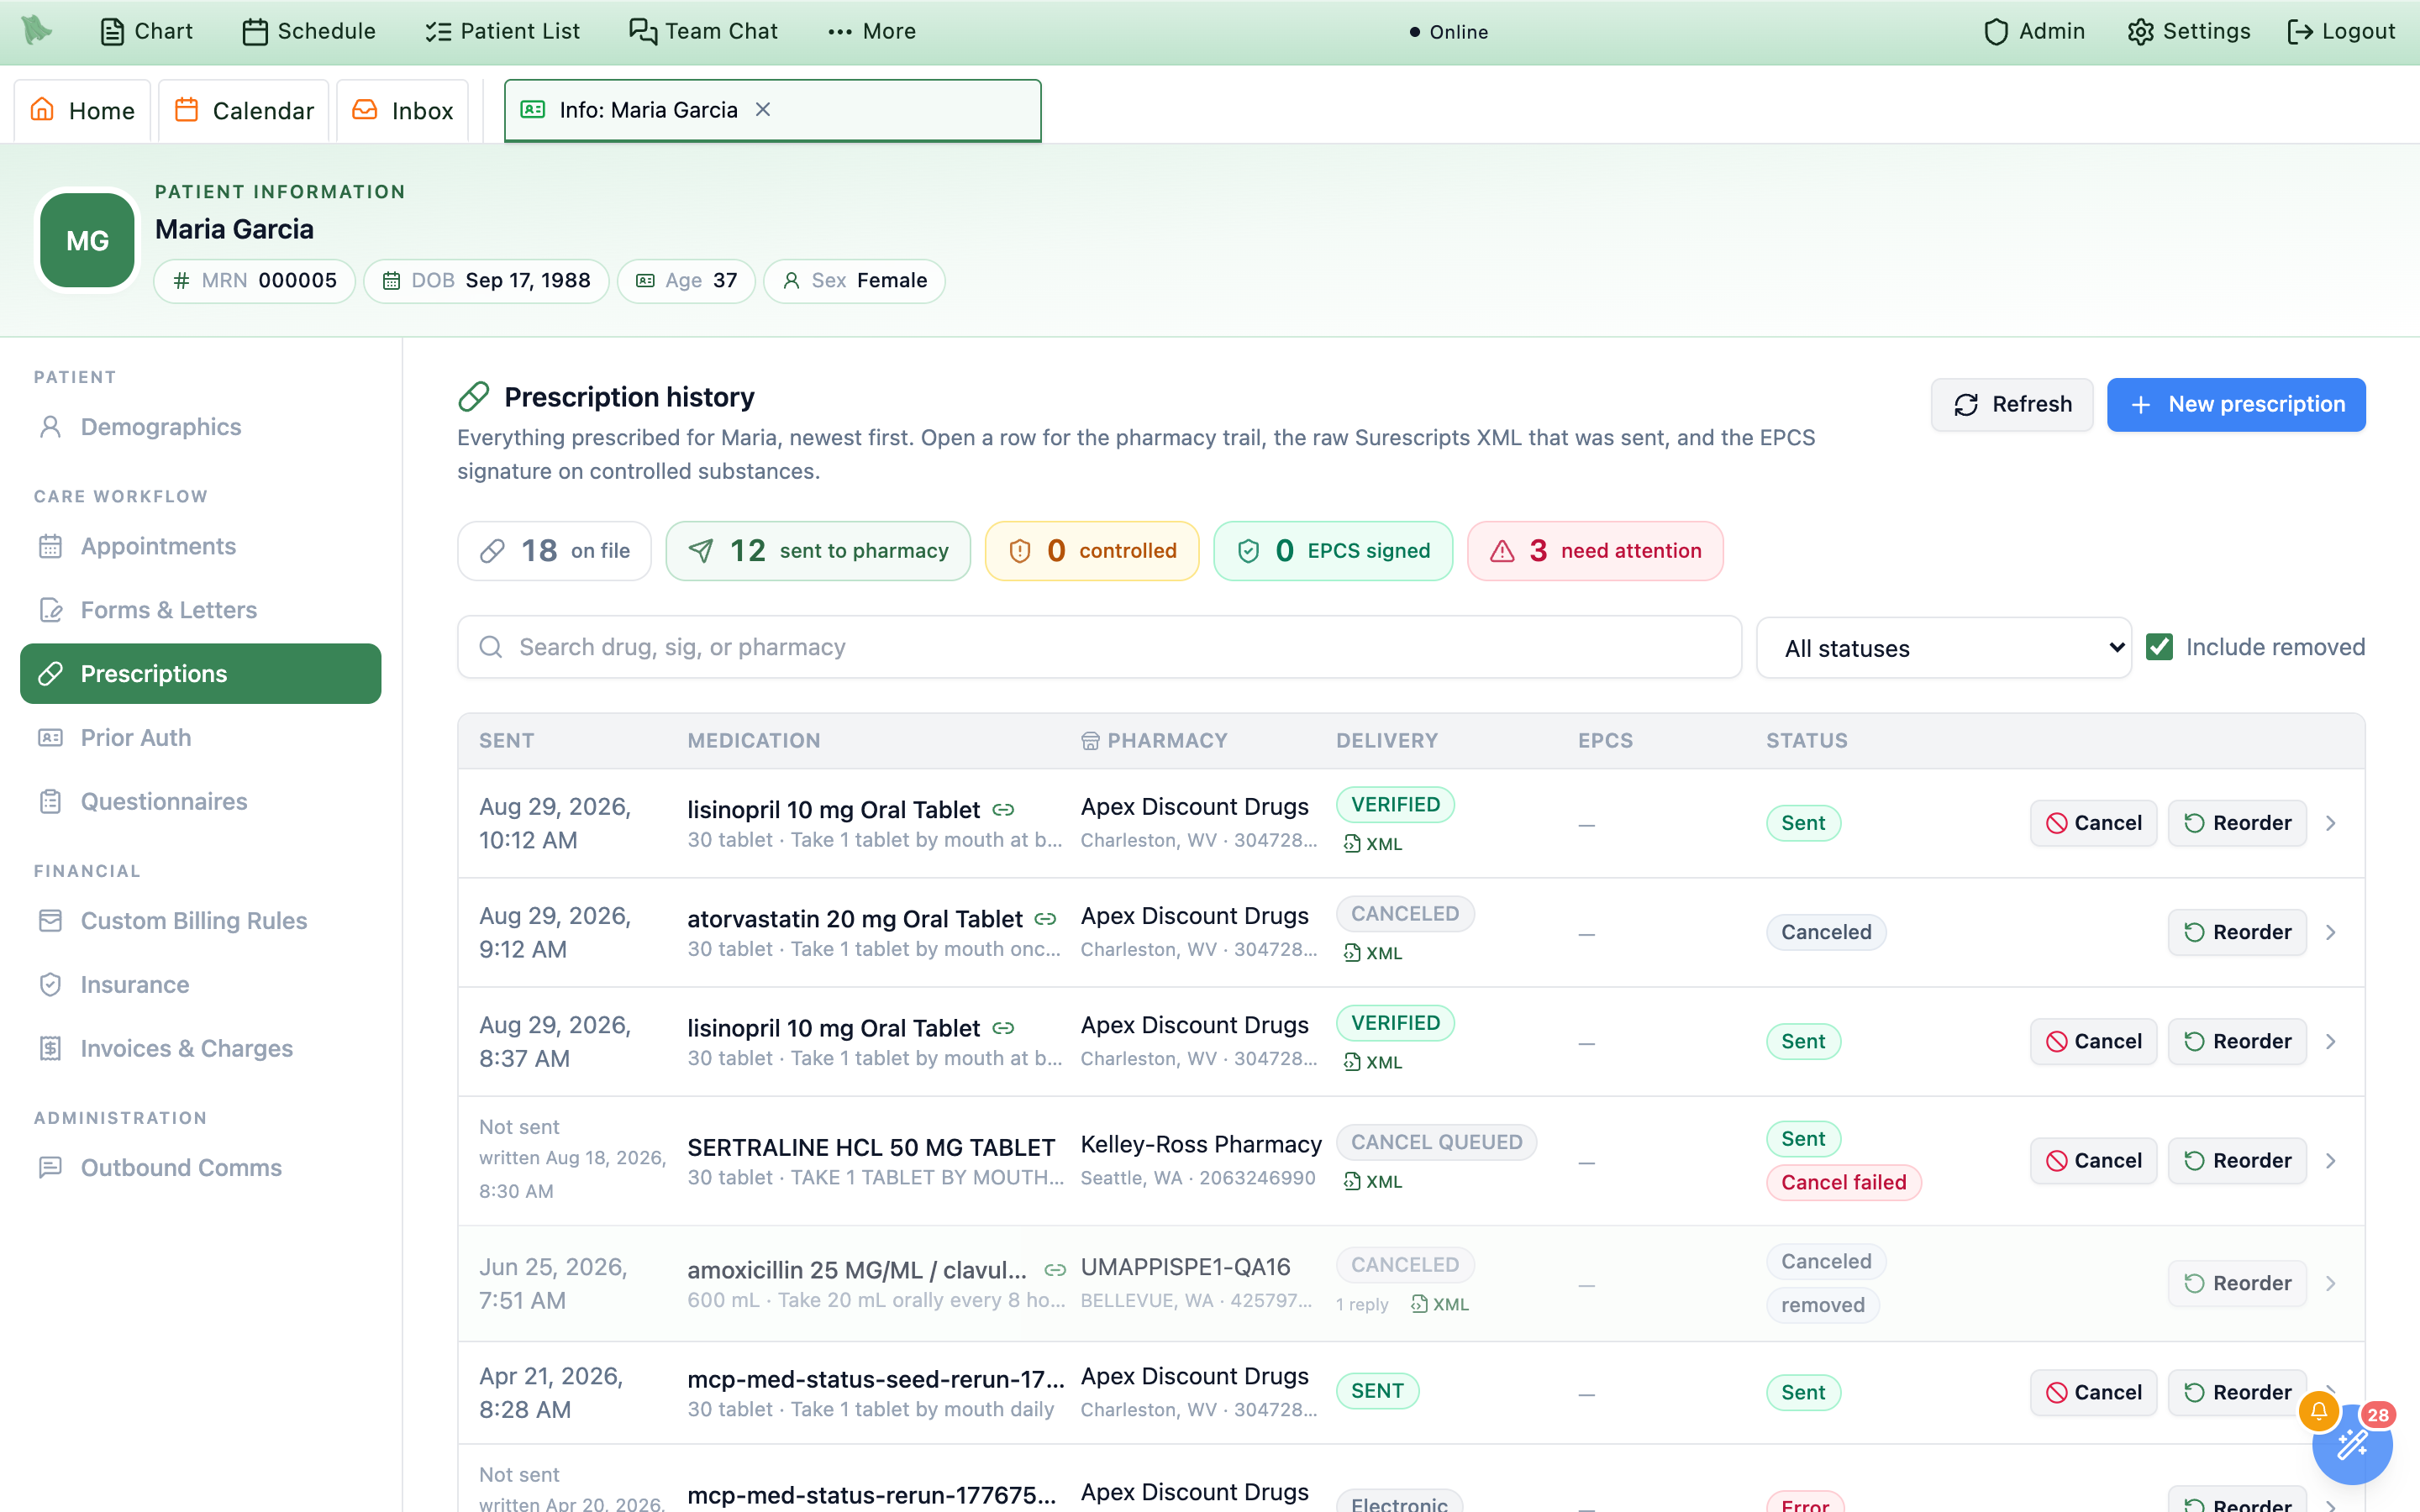
Cancel appears only on rows the pharmacy can still act on. Everything else keeps just Reorder.-
Say why.
CancelopensCancel this prescription— “The pharmacy is asked to cancel it. You will see their answer here.” — over a card naming the drug, the pharmacy, and when it was sent.Reasonis one ofEntered in error,Therapy changed,Patient no longer needs it,Duplicate prescription, orOther;Detail for the pharmacy (optional)takes up to 280 characters of free text, and both travel with the cancellation. -
Check what is actually being cancelled.
If the prescription you clicked was superseded by a renewal or a change response, an amber line says
This cancels the replacement prescription sent {date}— the recall follows the chain to the version the pharmacy is holding. On a controlled substance a second amber line reminds you that the pharmacy must acknowledge the cancellation. -
Send it, or back out.
Keep prescriptioncloses without doing anything.Send cancellationqueues it and confirms withCancellation sent to the pharmacy— “The prescription shows ‘Cancel pending’ until the pharmacy answers.” Nothing needs reloading; the row updates itself when the answer arrives. -
Read the outcome on the row.
While it is in flight the status reads
Cancellation Pendingwith an amberCancel pendingpill in place of the button, andDeliveryshowsCANCEL QUEUED. When the pharmacy answers, the pill becomesCanceled,Cancel denied, orCancel failed; the detail dialog spells the pending one out asCancel pending · requested {date, time}.
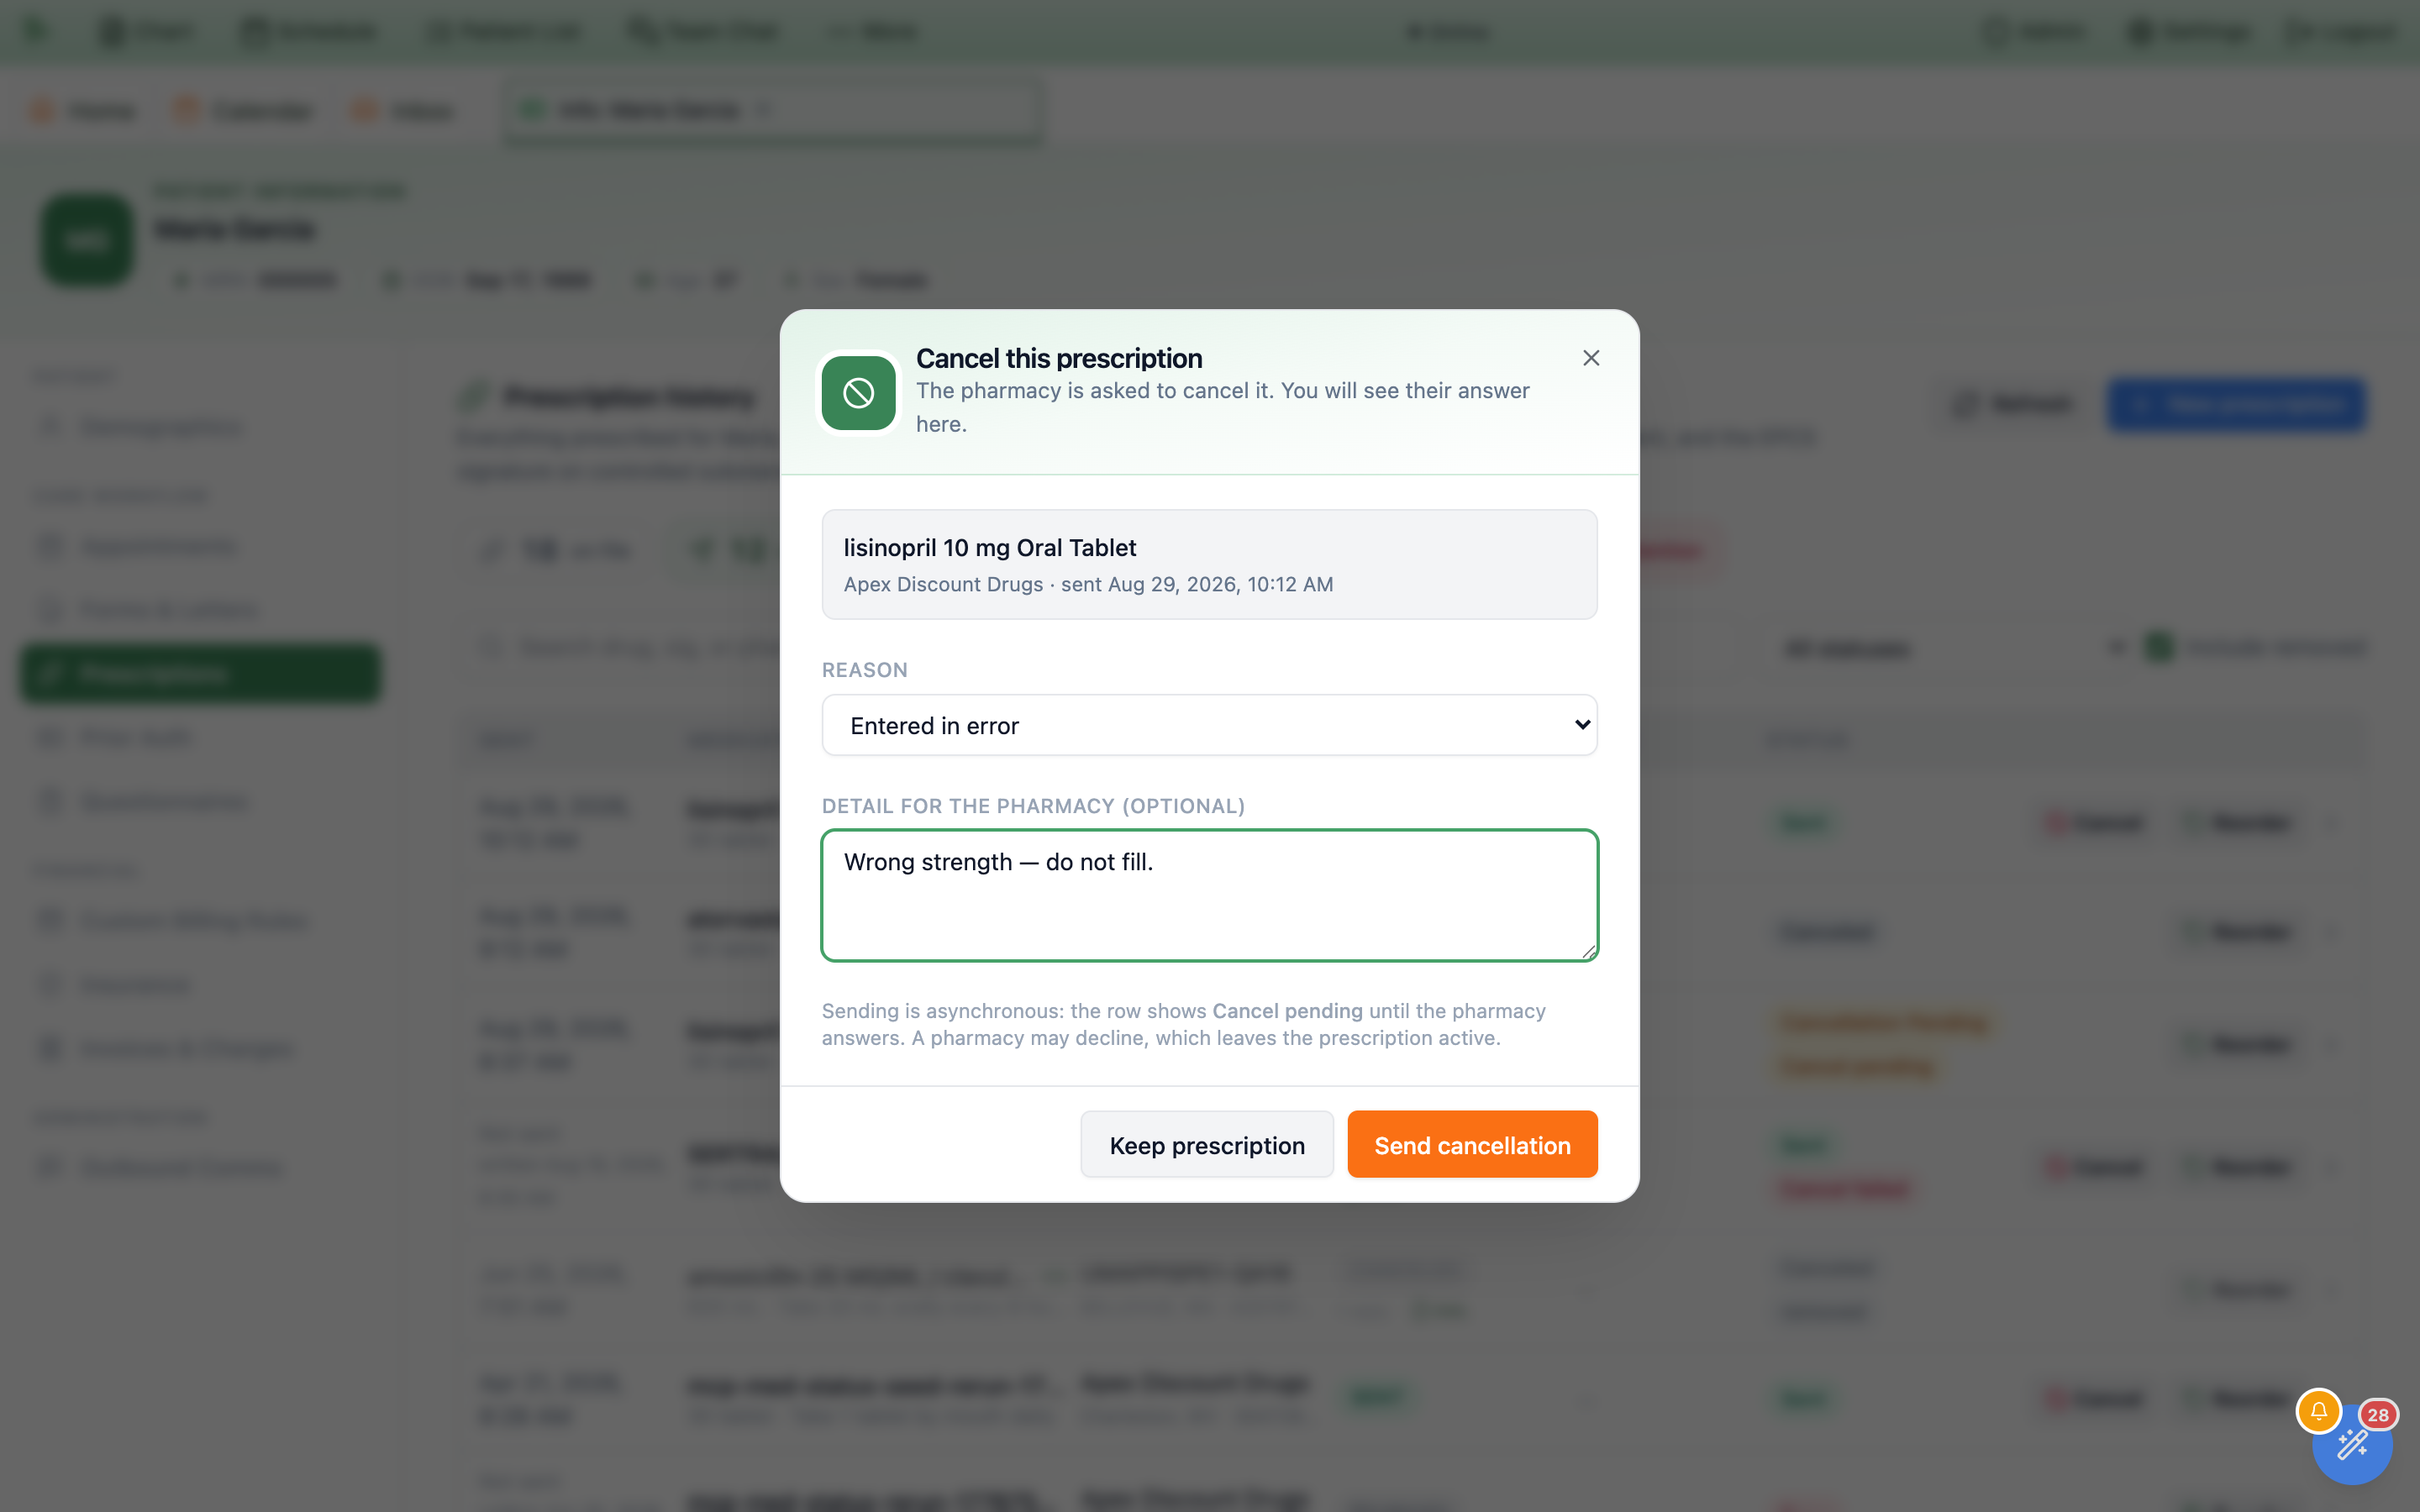
Keep prescription is the safe way out.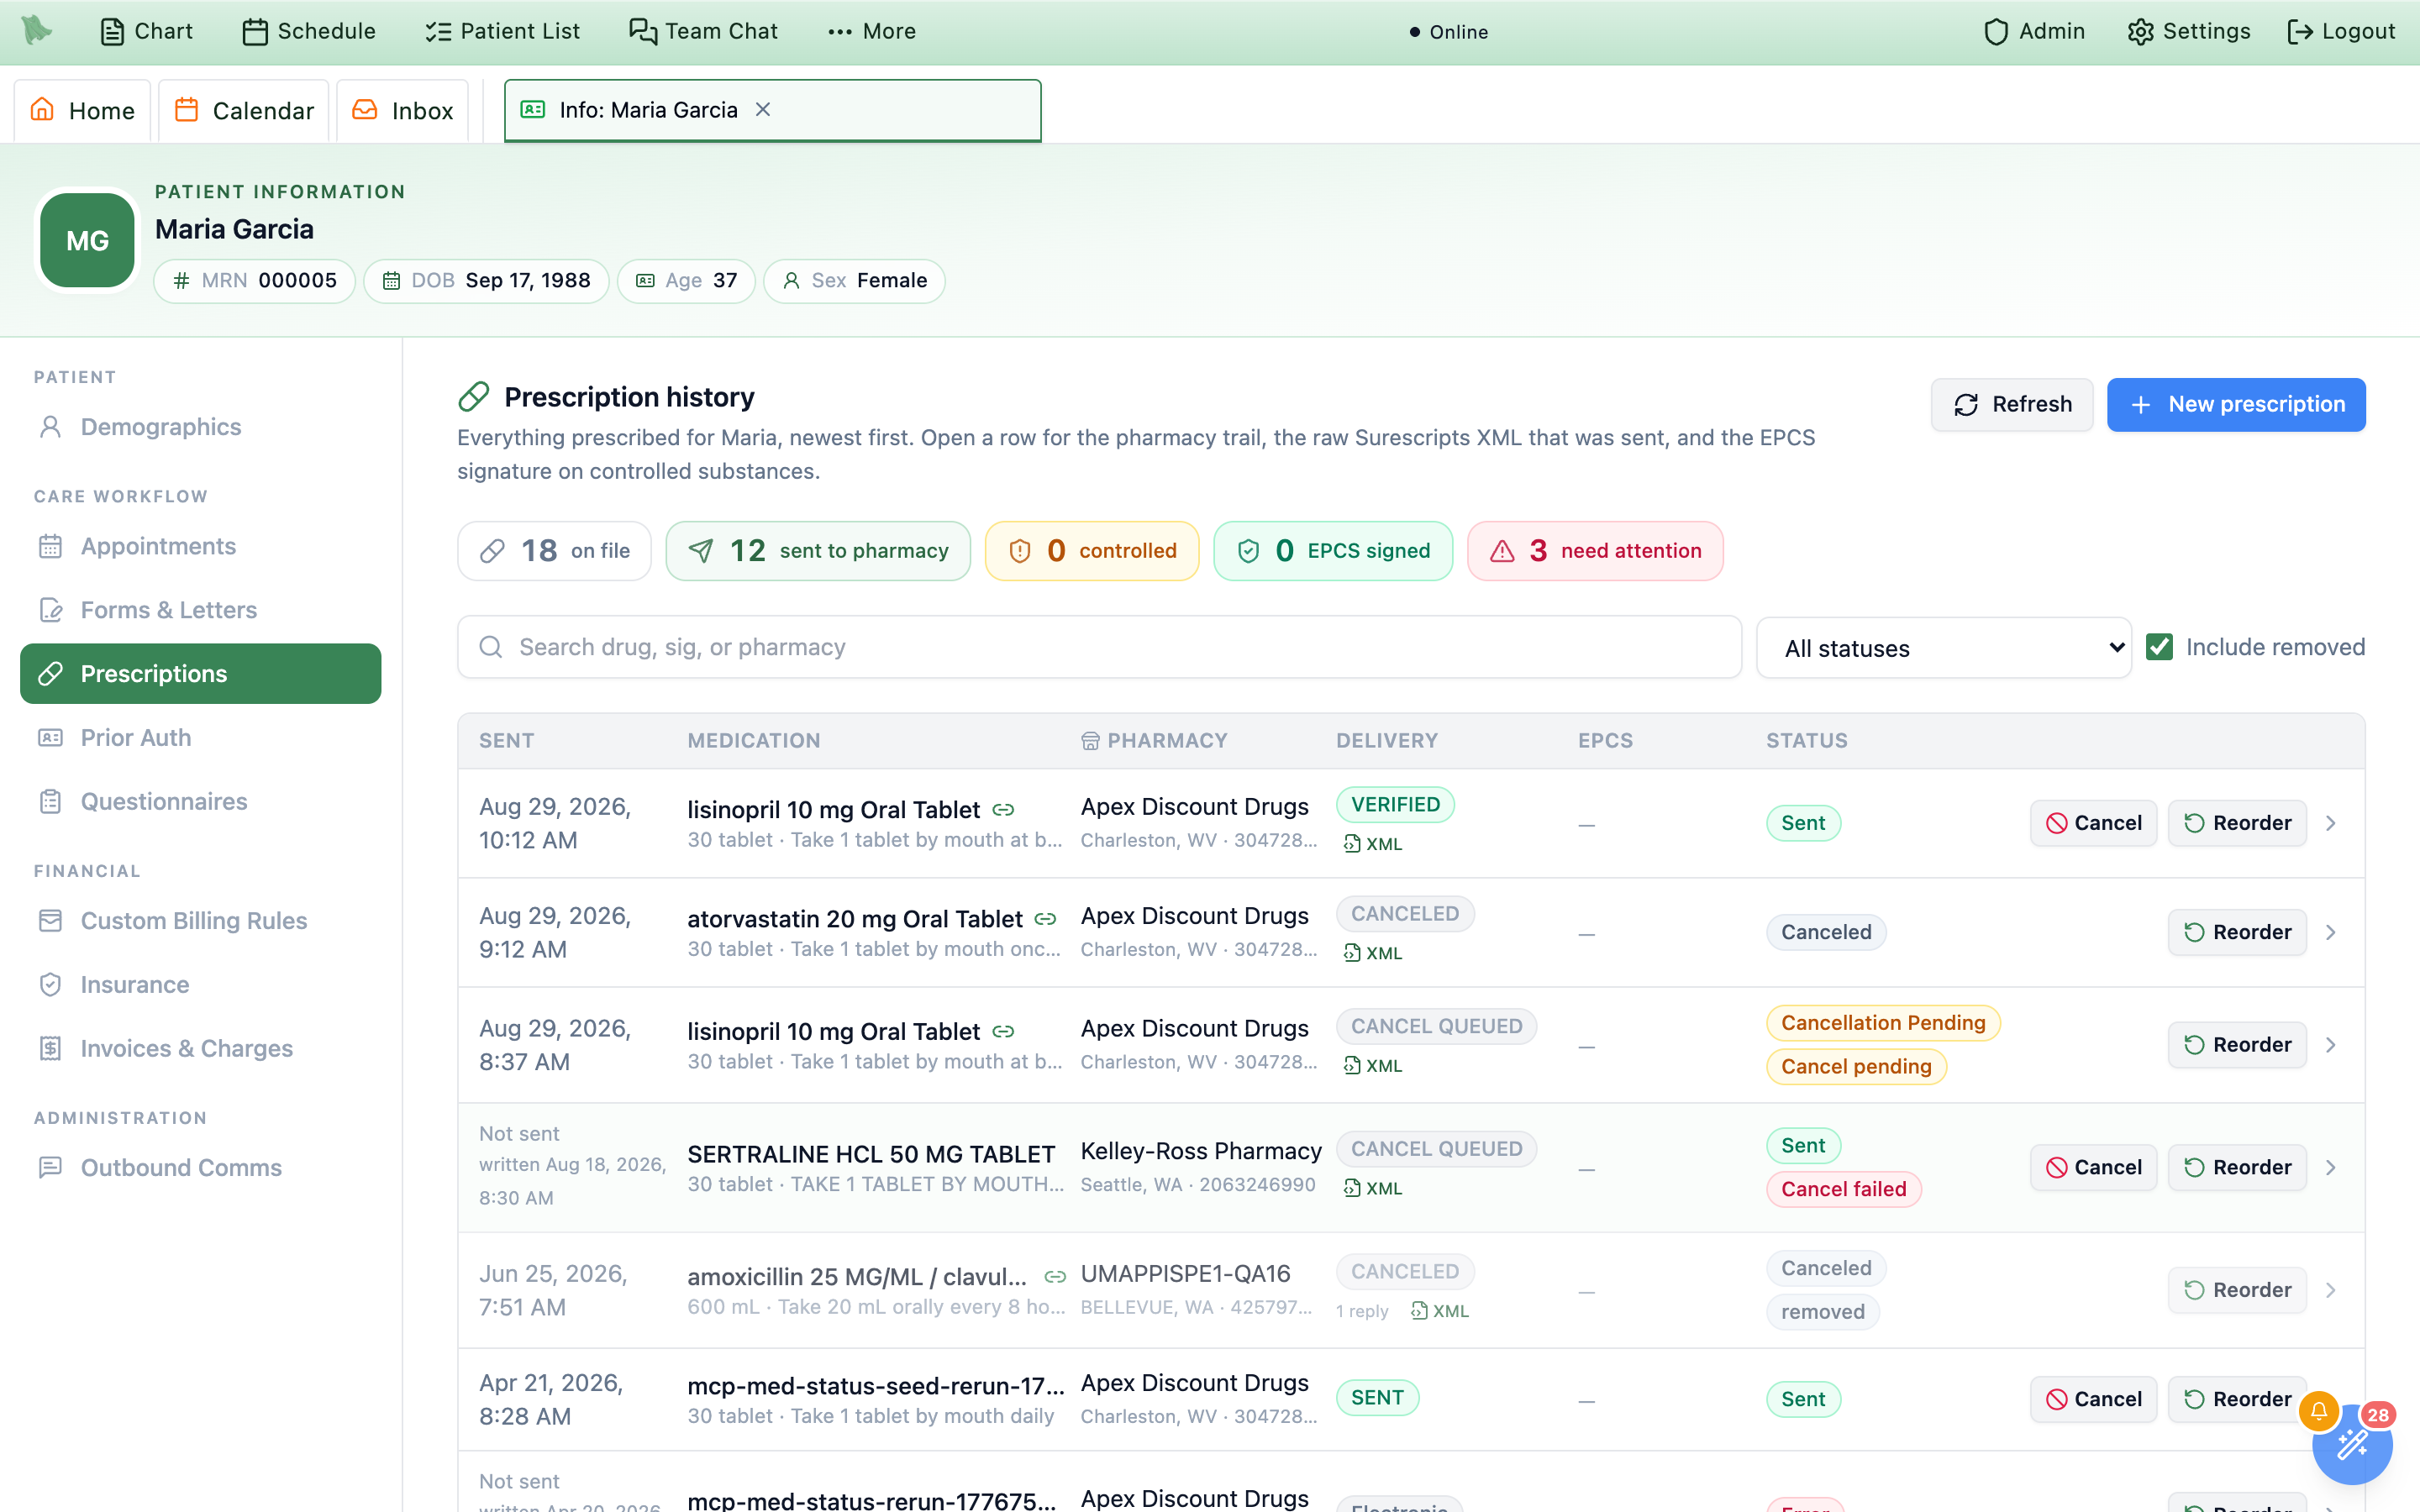
Status column: still waiting, cancelled, or refused.Cancel denied means the request was refused and the prescription is still active — it stays in the list, unfaded, and the patient can still have it filled. Cancel failed means the recall never reached the pharmacy at all. In both cases the prescription is live until you deal with it another way, so treat neither pill as “done”.Prescribe with a clinical note
Prescribing from this tab no longer means leaving the reasoning out of the chart. New prescription and Reorder both open the order workspace with a Clinical note box: once in the prescription dialog, directly under Diagnosis, and once as a Clinical note panel in the body of the modal with an Add a note button. They are two views of the same note — type in either one, and while the prescription dialog is open the panel shows a preview and reads “Editing in the prescription dialog — your changes appear here when you close it.” Dot phrases work exactly as they do in the note editor: type . followed by a few letters (the placeholder suggests .adhdfu) and pick from the list.
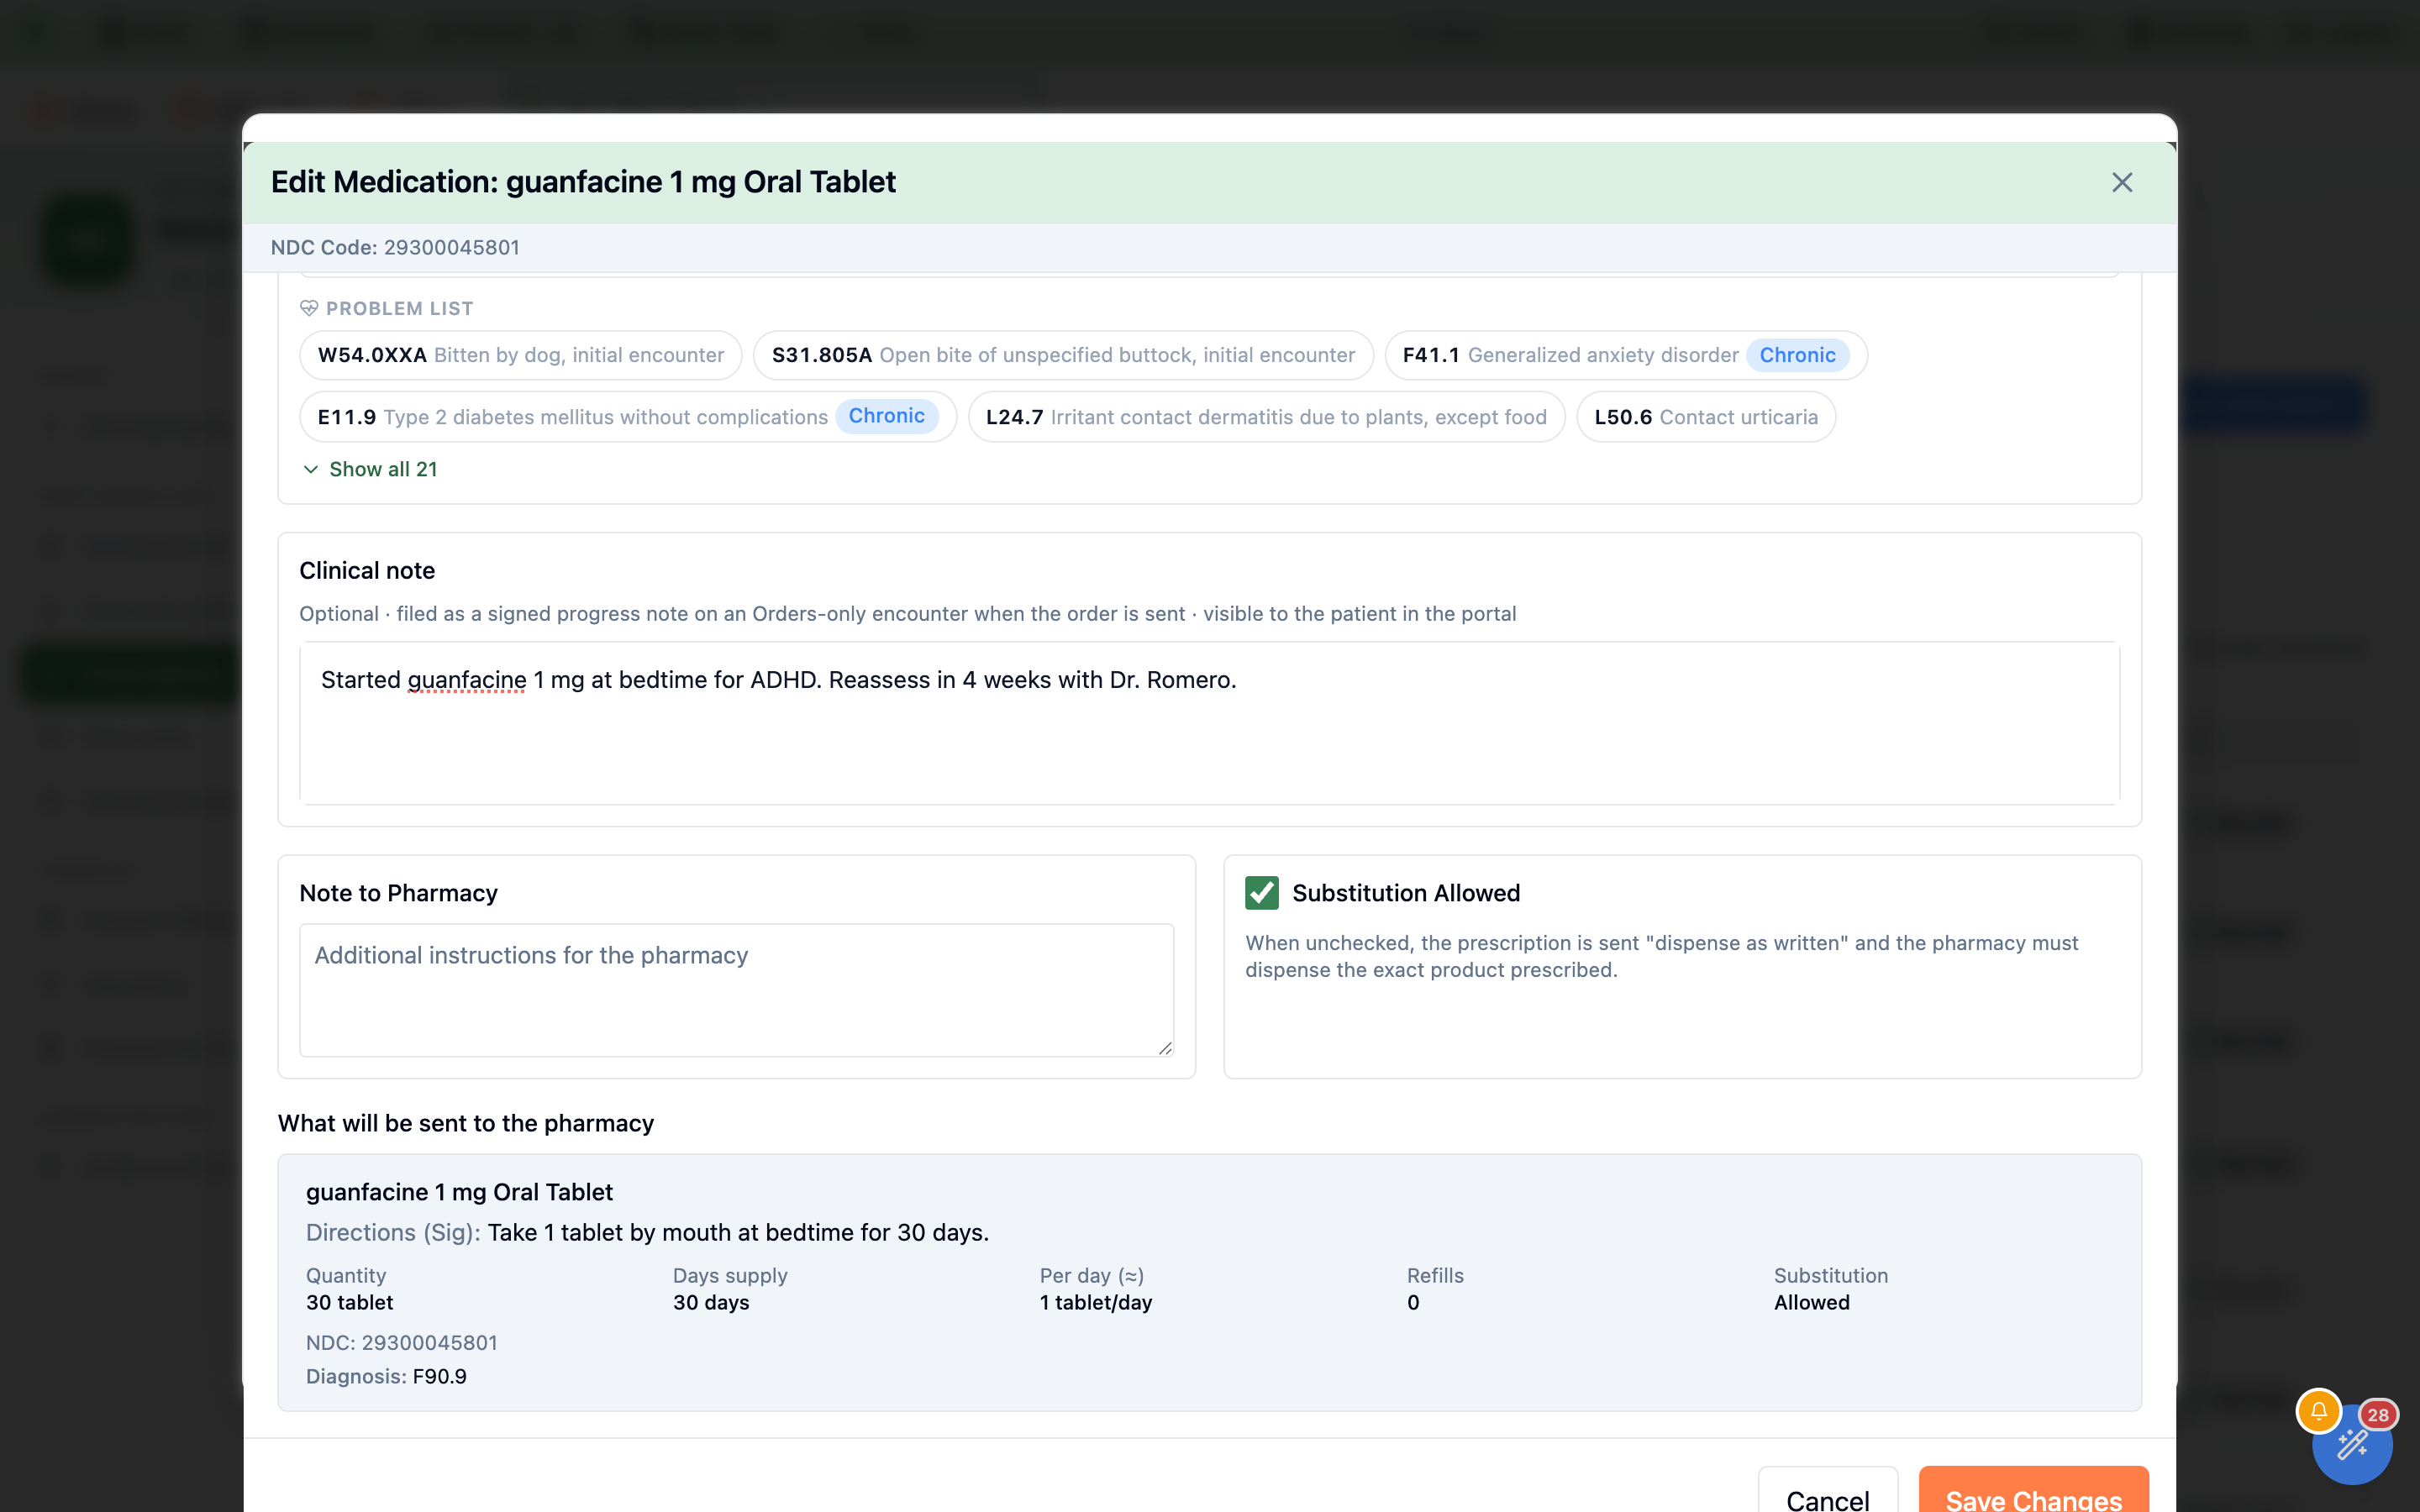
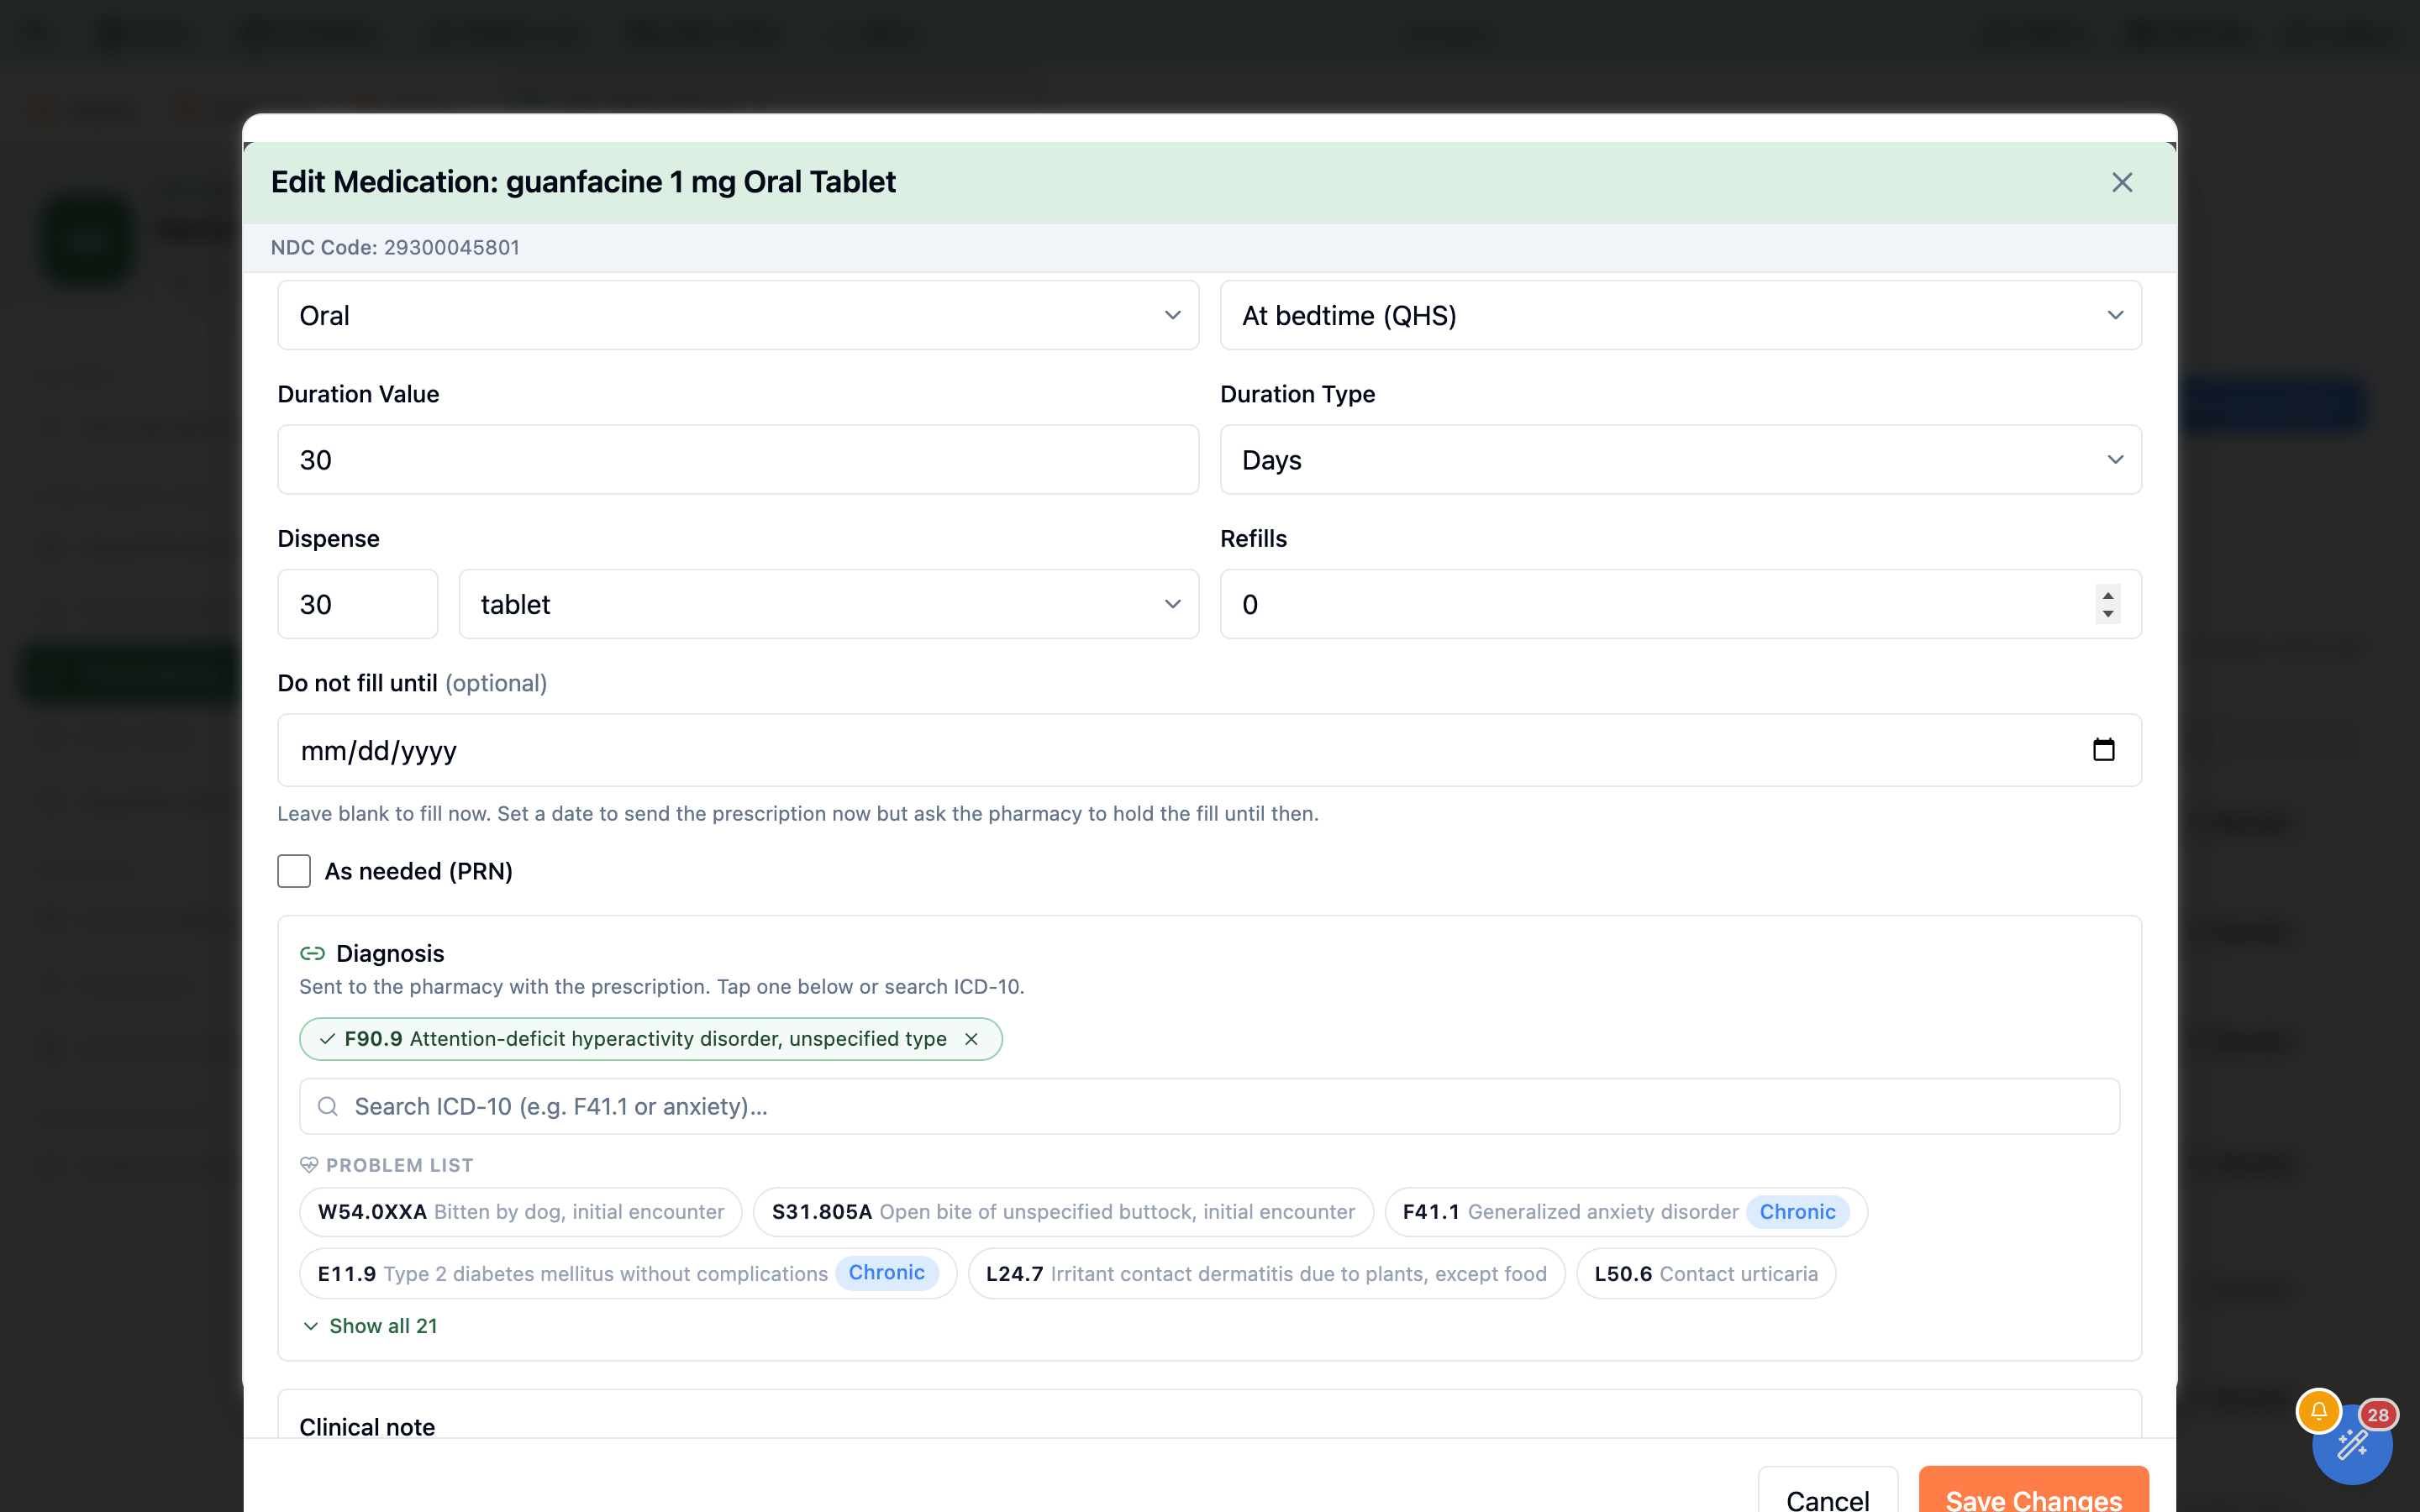
At bedtime (QHS) and the other timing options now survive the send and come back on a Reorder.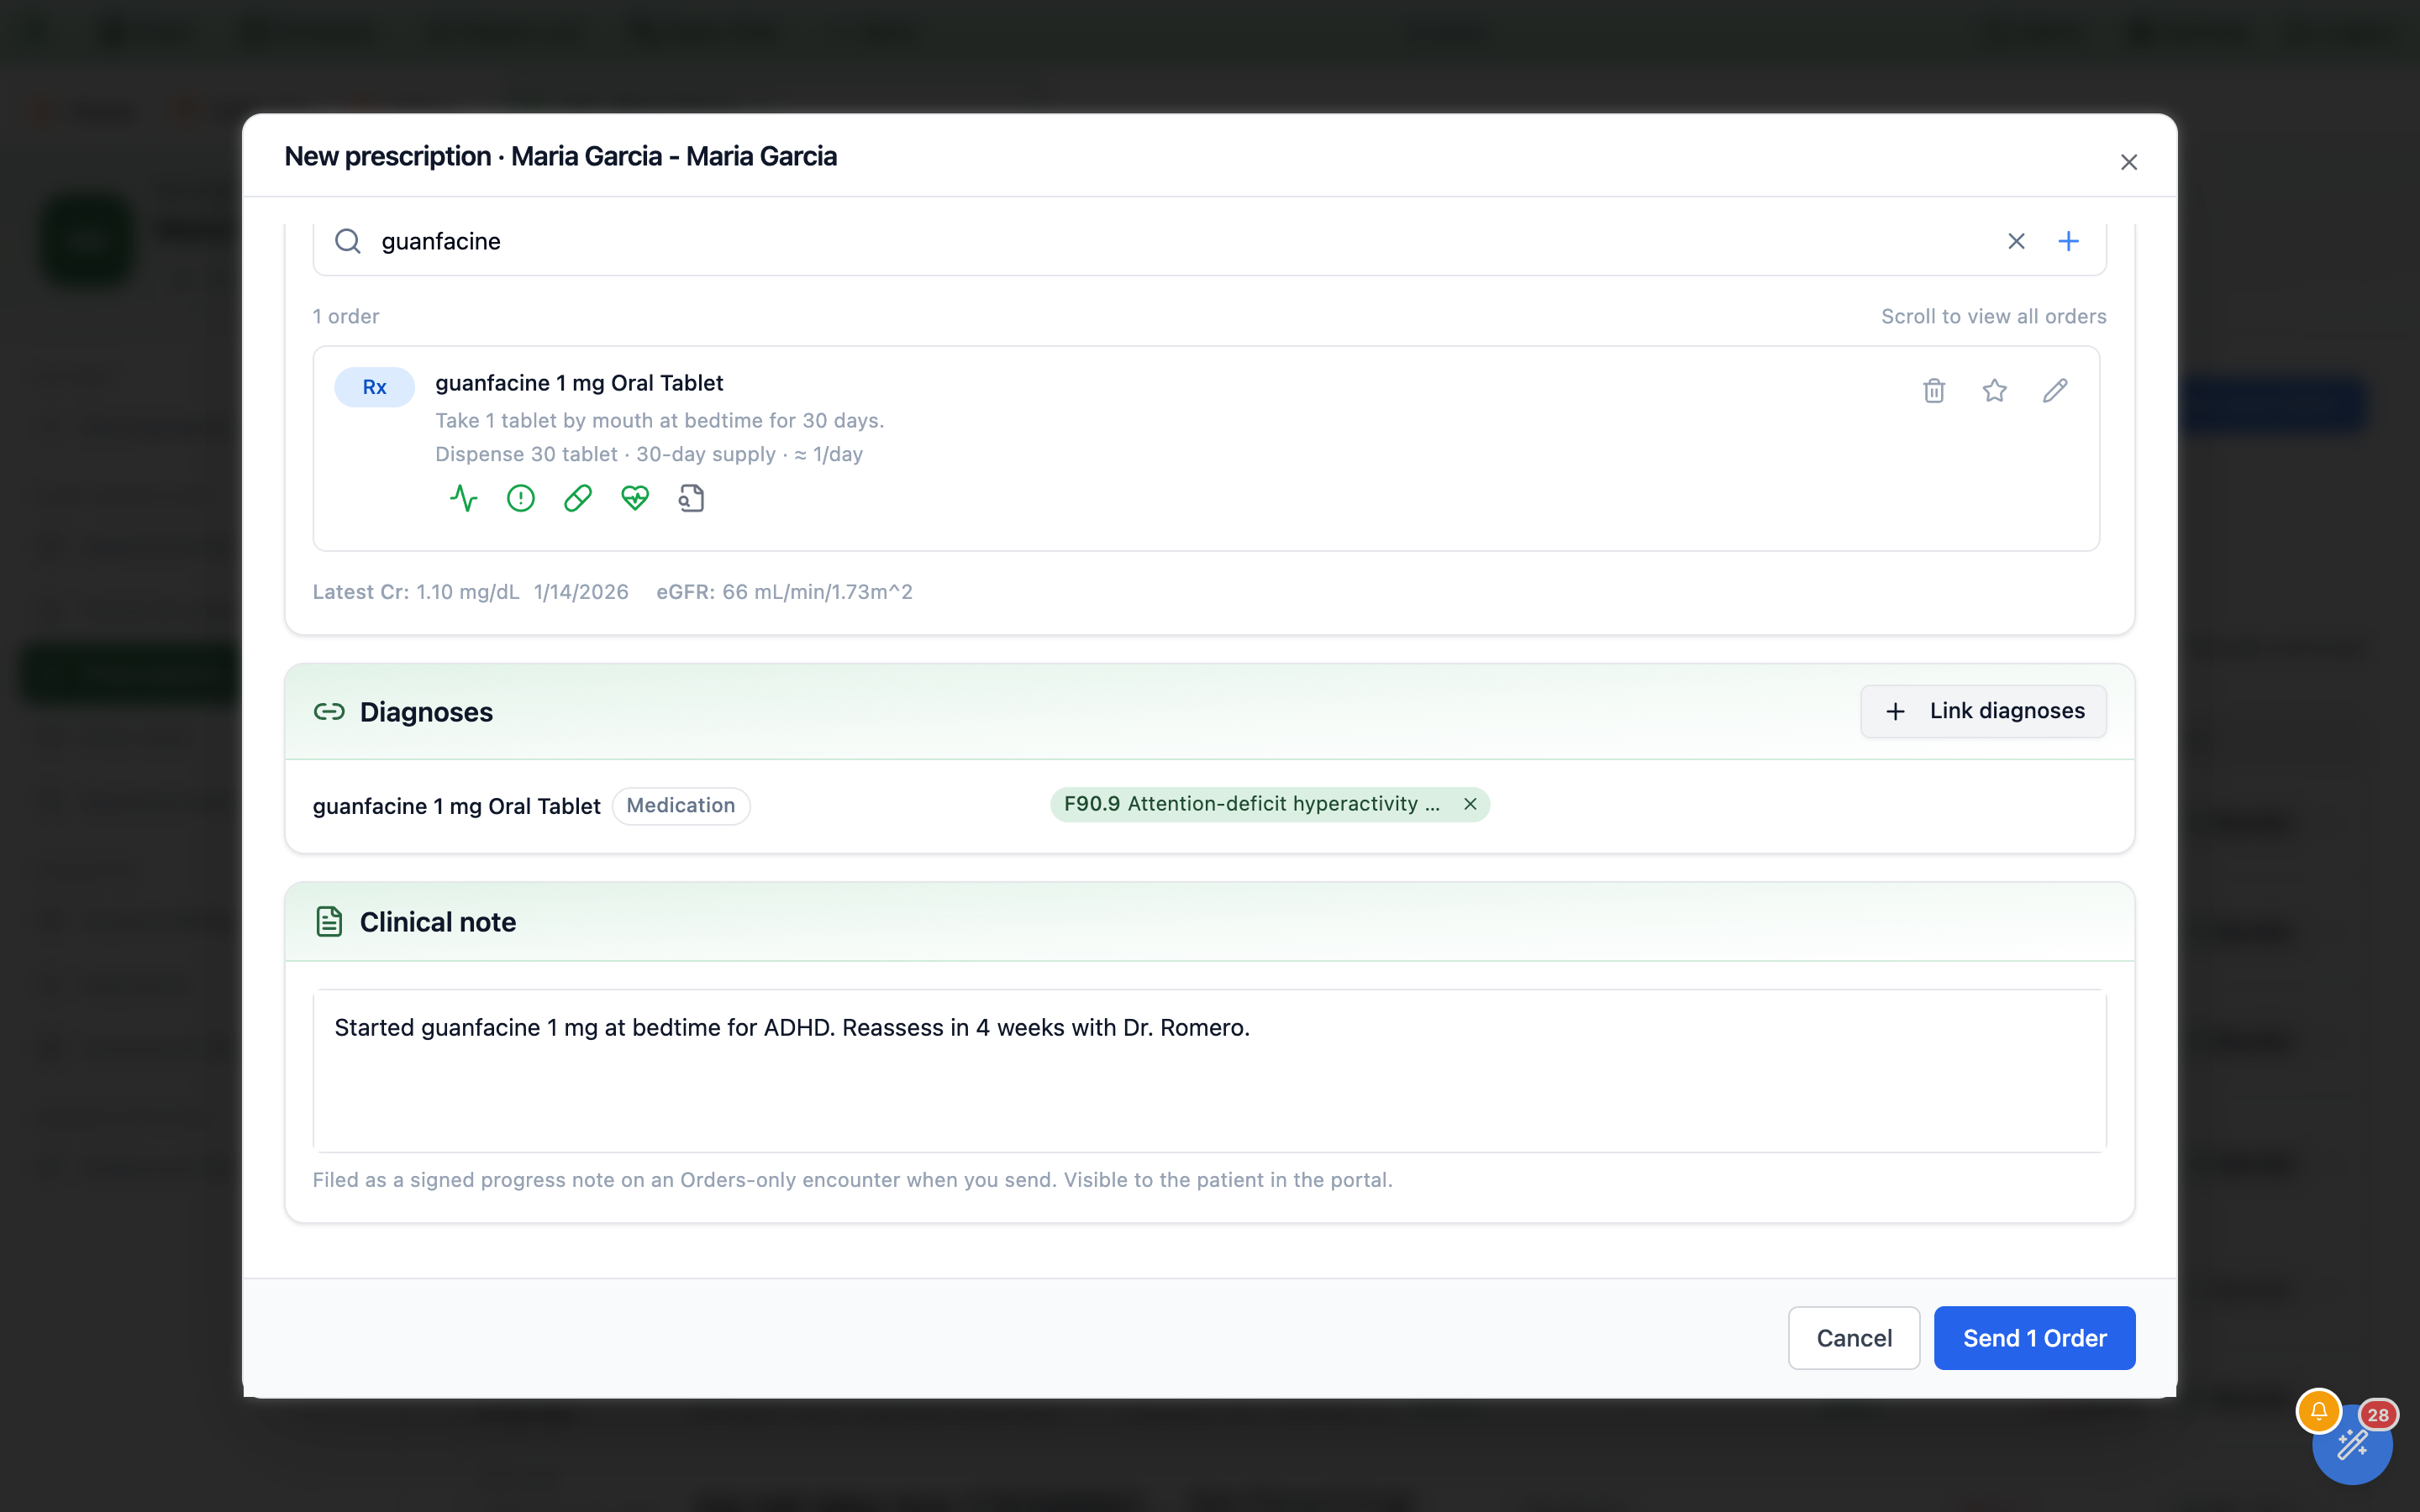
Send.Sending a prescription from here with no visit open creates one Orders only encounter for that send, and the note is filed on it as a signed progress note — but only after at least one order has actually gone out. Cancel the modal, or have every order fail, and nothing is filed and no visit is created. When it works the panel gains a green Filed badge; if the orders go but the note does not, the panel says Not filed — your orders were sent, the note was not. with a Retry button beside it. Afterwards the note is an ordinary chart note: it shows on the Notes tab of the visit, it reaches the patient in the portal like any other signed note, and the prescription’s detail dialog records where it went — the Encounter field reads Orders only · {date, time} with a Clinical note filed chip beside it.
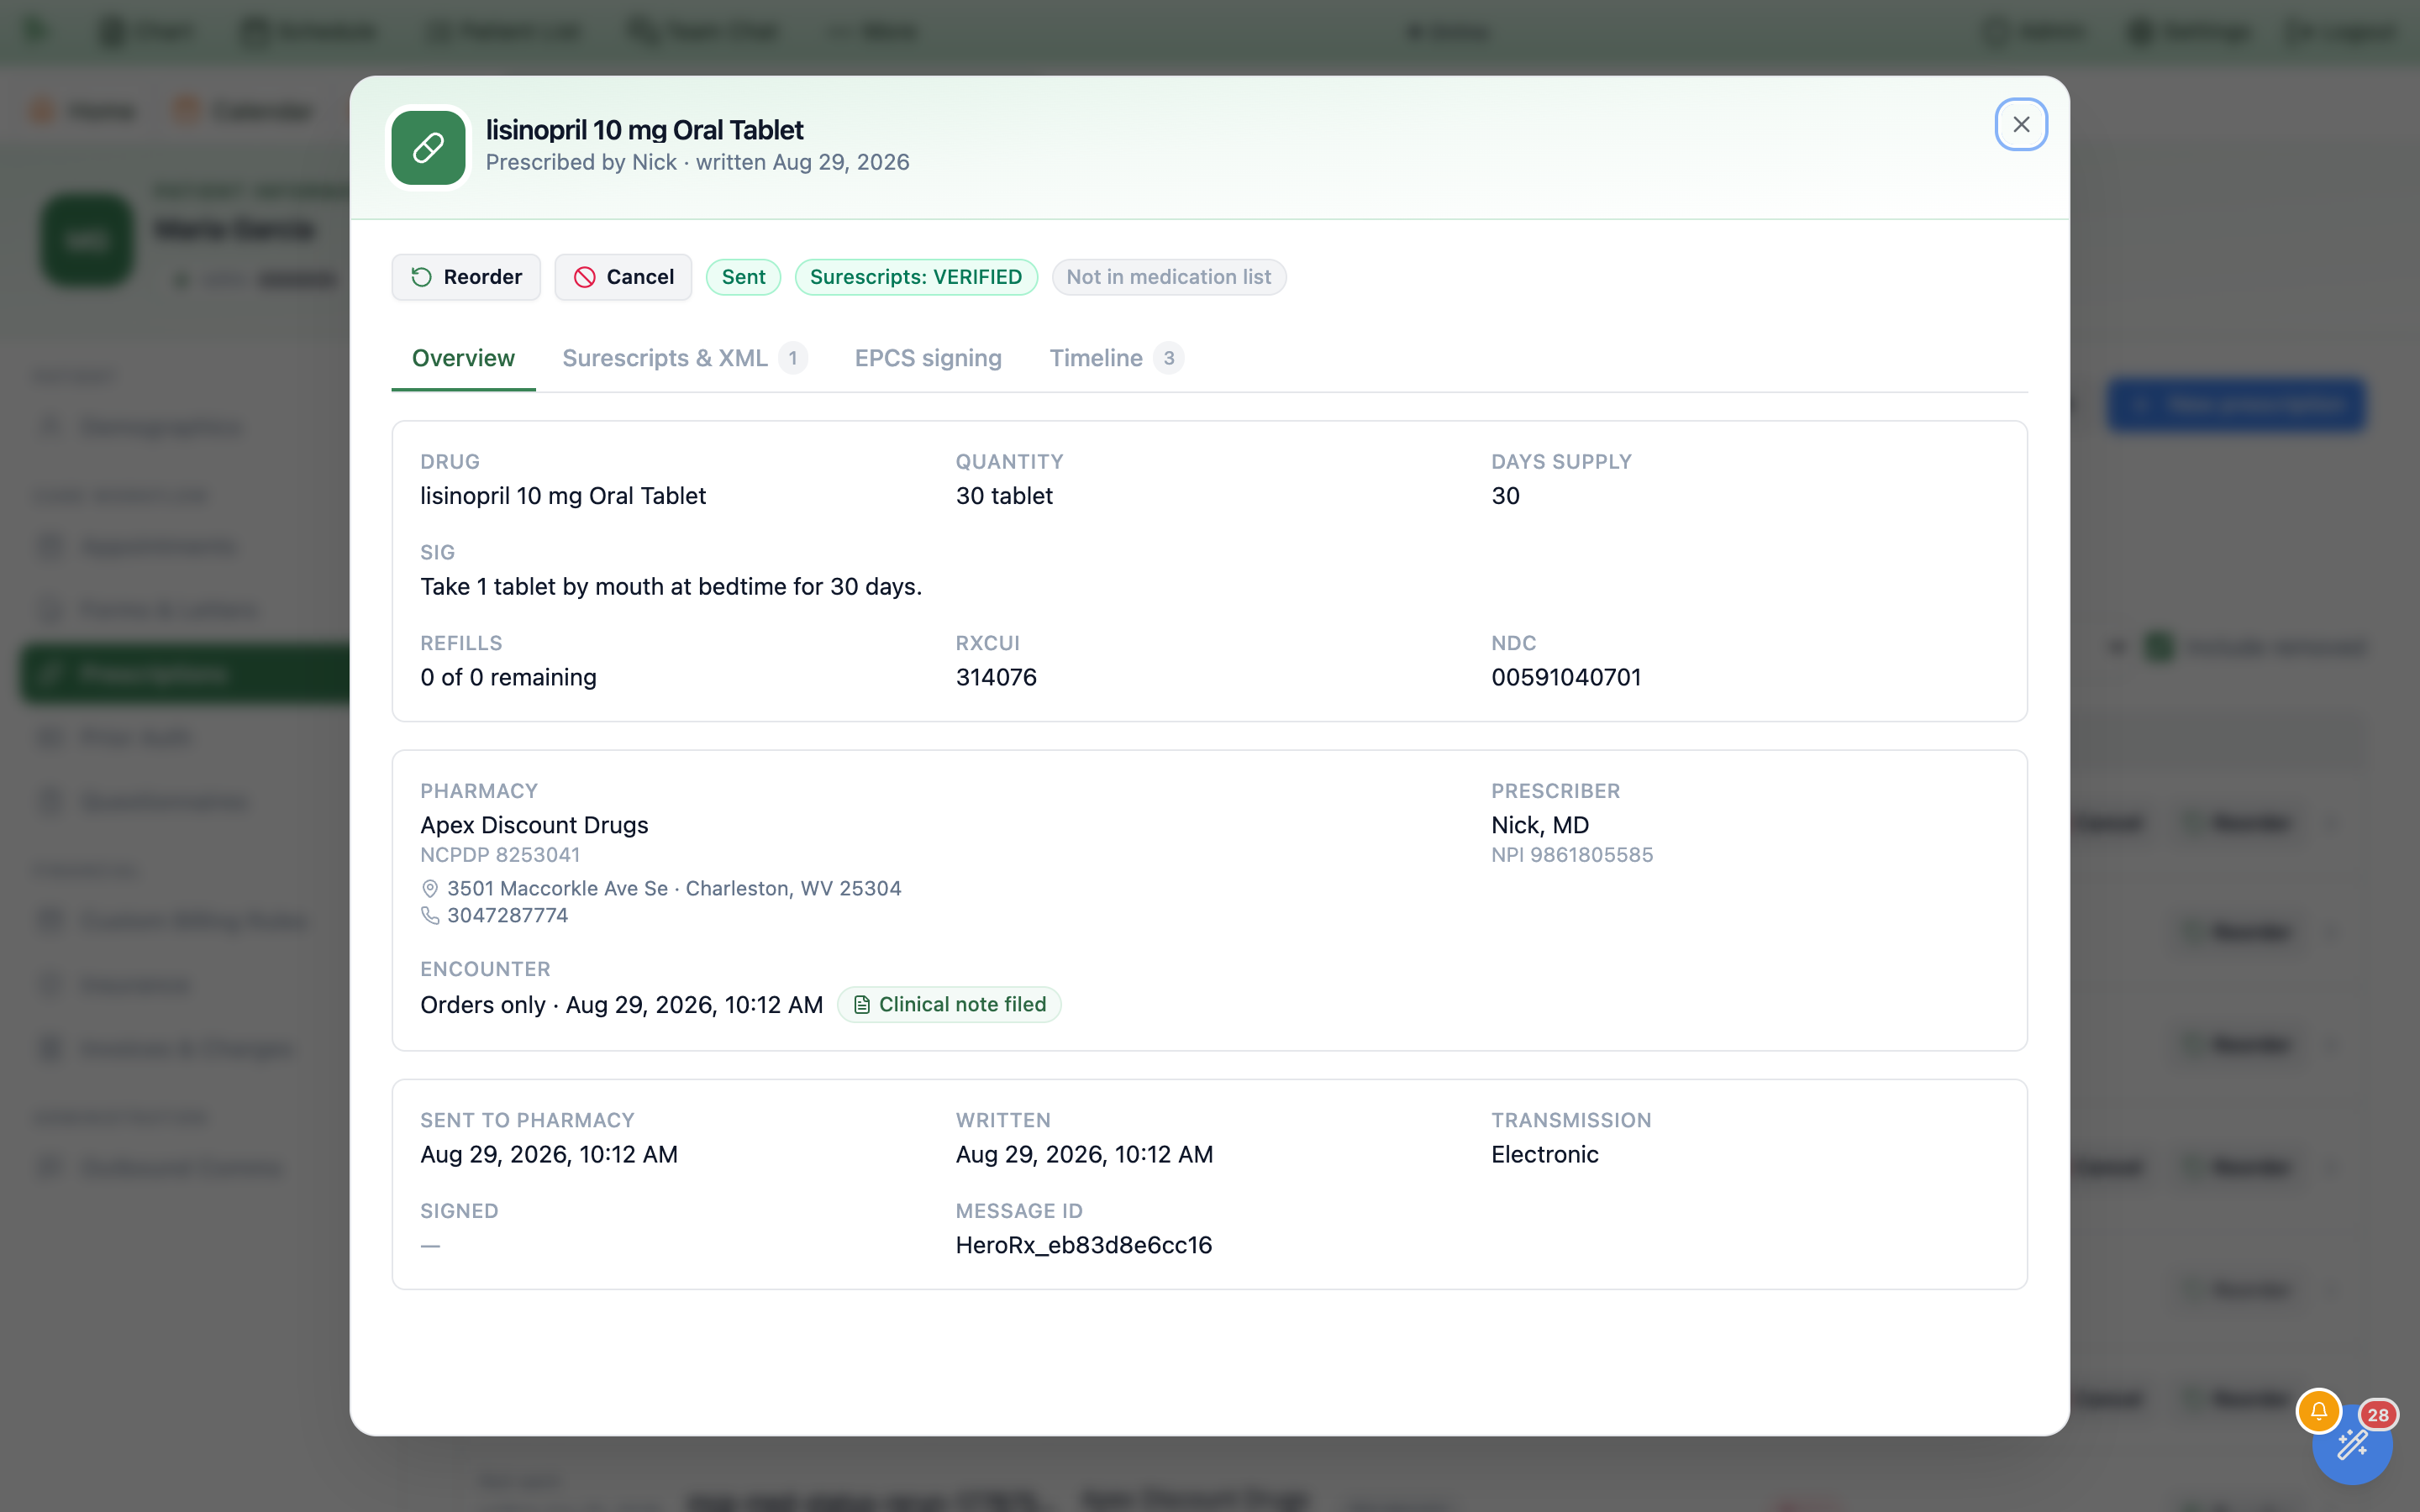
Encounter field is the receipt: which visit the order landed on, and whether a note went with it.Every letter and form for one patient, in one place
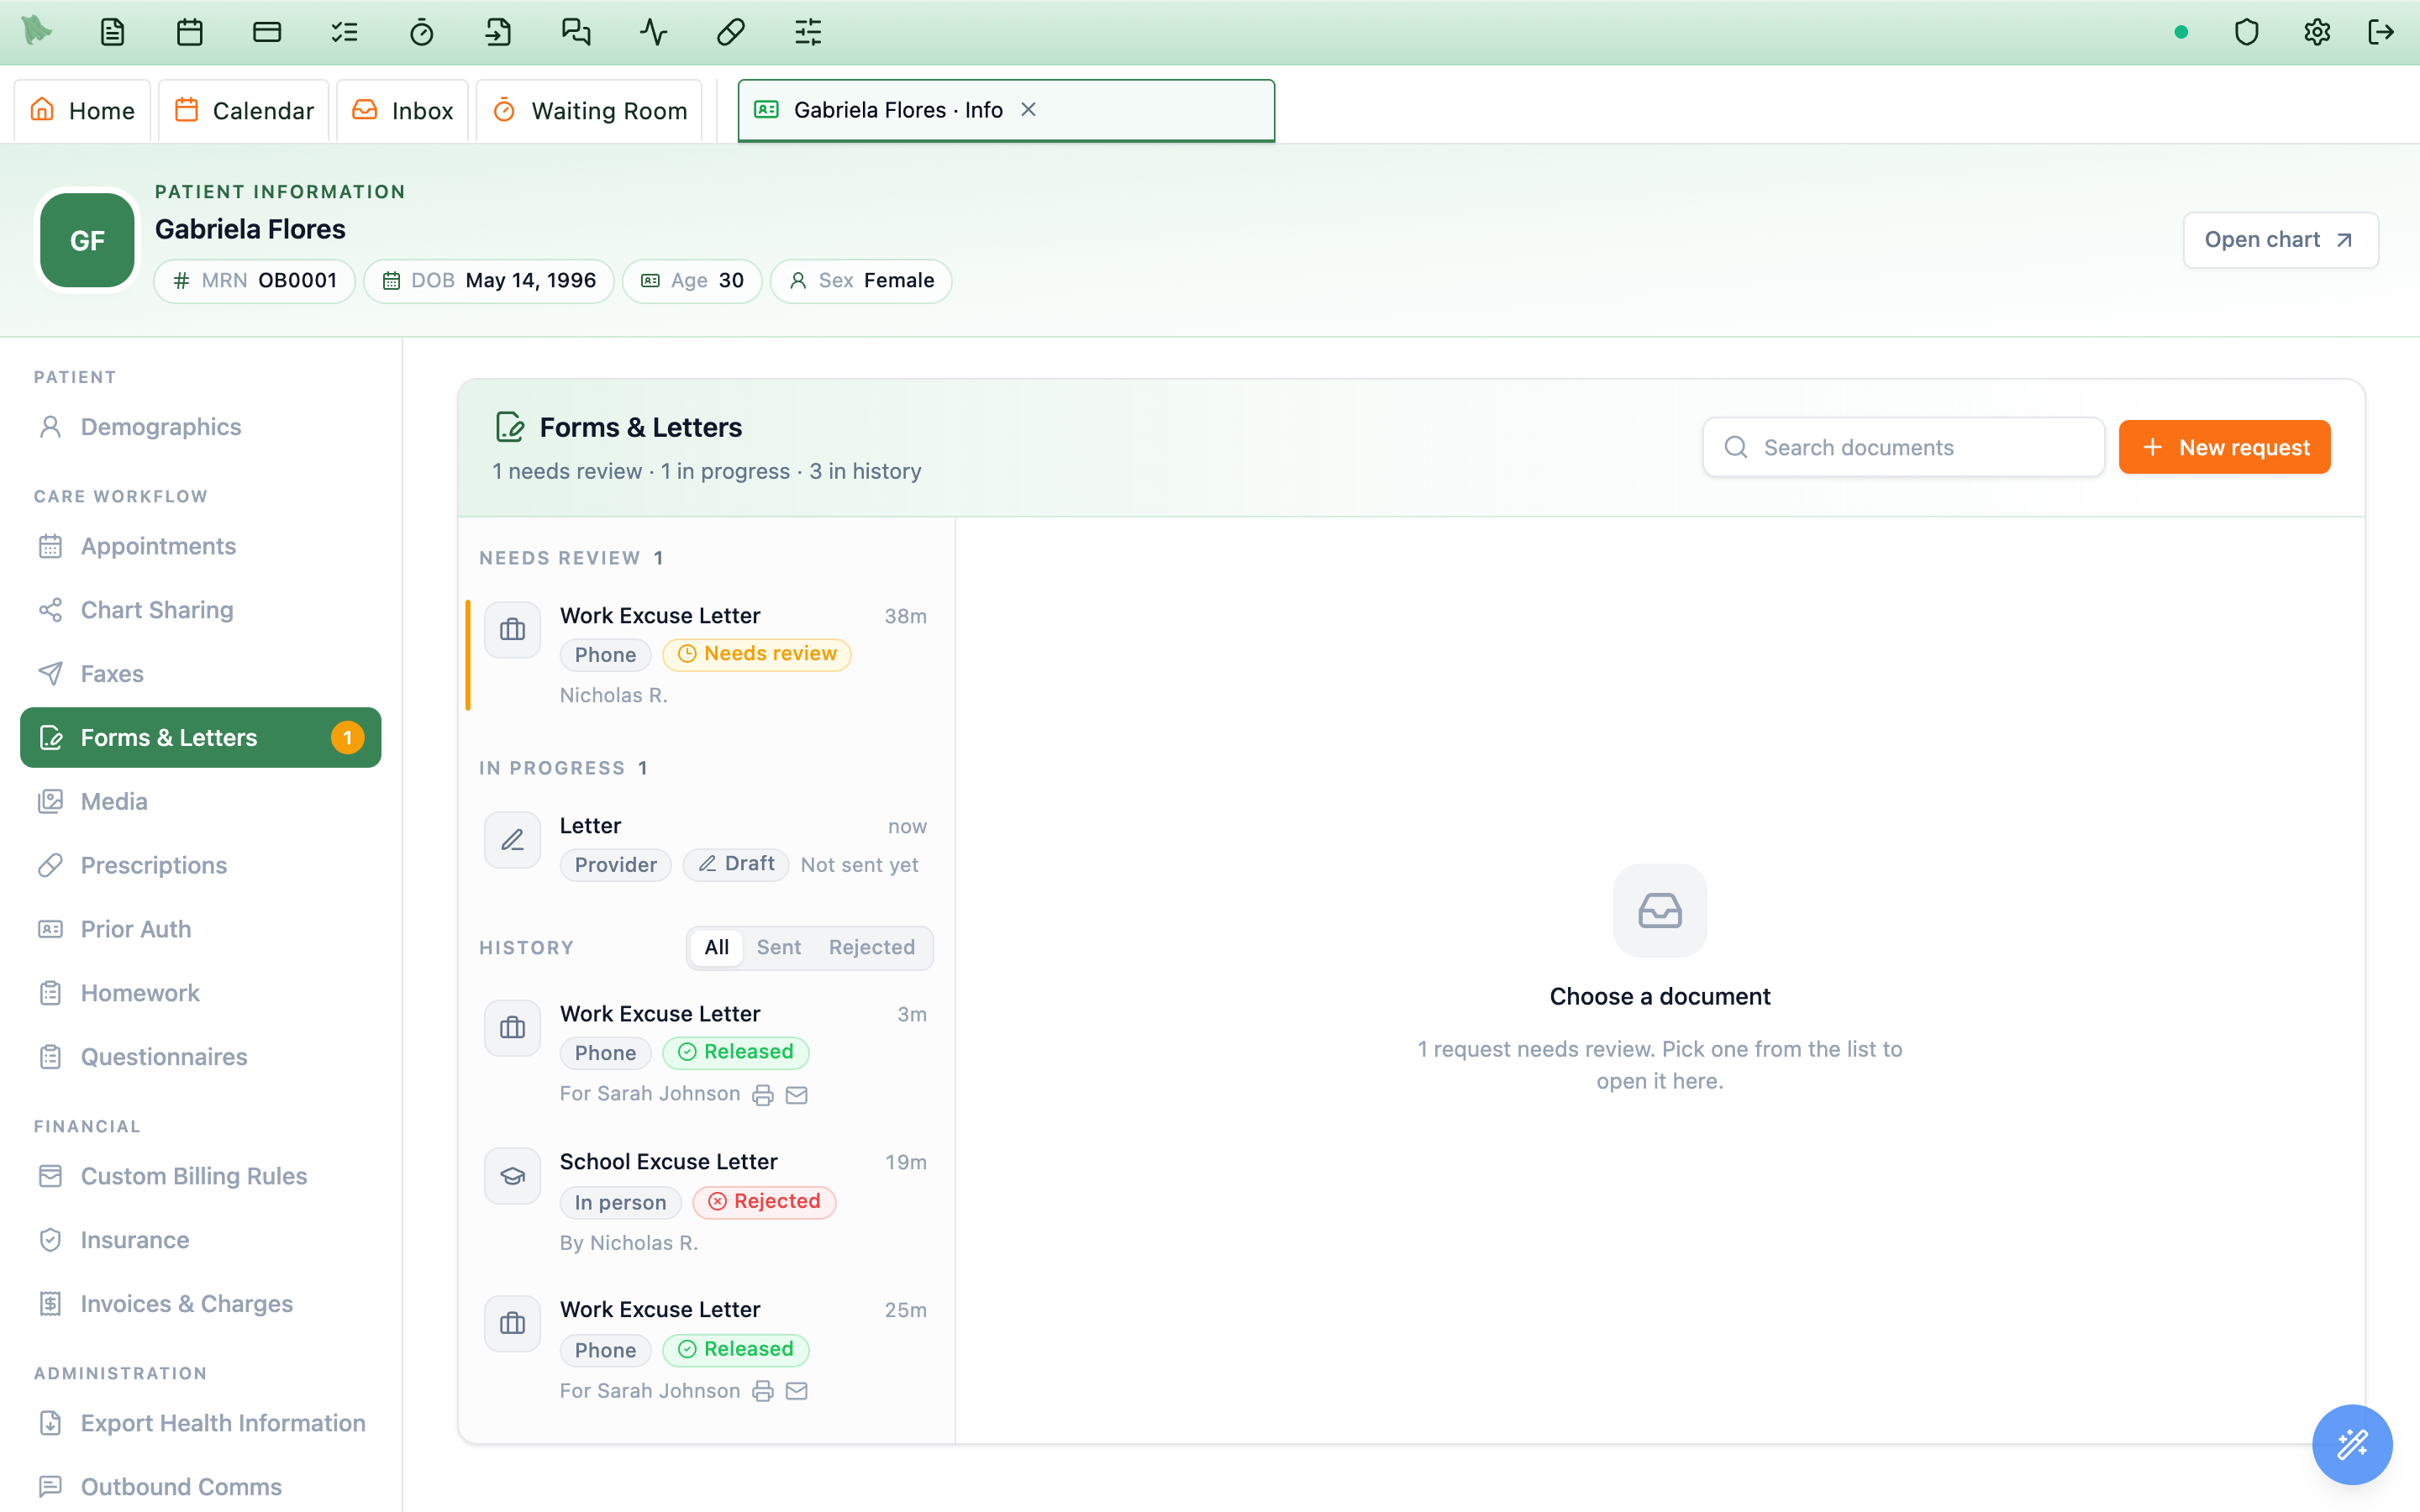
Forms & Letters under Care workflow is where the whole office works a patient’s letters and forms: work and school notes, FMLA and disability forms, the employer’s or school’s own PDF, and the provider’s own letters. The front desk starts a note for a patient who calls, a medical assistant or nurse checks the draft and releases it for the provider, and anyone who reads the chart can print what was released. Requests patients make in the portal land here too, so nothing has to be chased through the Inbox.
Who sees it and who can do what
The tab is there for providers, practice administrators, and staff who can open patient charts (patient.view). What each person can do depends on one staff permission, Forms & Letters (forms_letters.manage), which the Front Desk, Medical Assistant, Nurse, Clinical Staff, Office Manager, Intake Coordinator and Referral Coordinator role profiles include. Billers do not get it. An administrator can take it away from one person under Staff & assistants.
| Who | What they can do here |
|---|---|
| Providers | Everything: start requests, review, approve with their own signature, reject, edit, withdraw, print, fax and email. Only providers get Write a letter and Fill a form in New request. |
| Practice administrators | Start, review, release for a provider, reject, edit, withdraw, print, fax and email. |
| Staff with Forms & Letters (front desk, medical assistants, nurses, office managers, intake and referral coordinators) | Start a request for the patient, review it, release it for a provider, reject, edit, withdraw what they entered, print and email. Fax needs the practice’s permission to send faxes as well (below). |
| Other staff who can open charts, such as billers | Read the list and the documents, and Print and Download what was released. They cannot start, release, reject, edit or email. |
The buttons each person sees come from the server, so you never see a button that would fail. A staff member never signs as the provider: a staff release either carries the provider’s saved signature (only if that provider allowed it, 7.44) or the staff member’s name released for the provider, and either way the PDF names who released it (7.40).
Read the screen
-
The header.
Under the title a summary line reads, for example,
2 need review · 1 in progress · 14 in history(Nothing to reviewwhen nothing is waiting).Search documentsfilters the list by title, source, status and the people involved.New requeststarts a request (7.39). When something needs review, the tab itself carries a count, in the sidebar and in the dialog’s tab row. - Needs review. Drafts that are ready and waiting for someone to approve or reject them. Each row has an amber bar on its left edge.
-
In progress.
Documents still being drafted (
Drafting…, orEditing…while a quick edit runs), drafts that failed (Failed), and a provider’s unsigned letters (Draft). This group is hidden when it is empty, and the list refreshes on its own while something is drafting. -
History.
Released and rejected documents, newest first, with the chips
All,SentandRejected. Older ones load as you scroll, or withShow older documents. -
Read a row.
Each row shows the document’s icon and title, how long ago it was asked for or decided (
12m,2h,3d, then the date), a source chip —Portal,Phone,In person,Fax,EmailorOtherfor how the patient asked,Providerfor a provider’s own letter — and a status chip:Needs review,Drafting…,Editing…,Failed,Draft,ReleasedorRejected. A short line says who entered it (Maria L.), who it was released for (For Jane Romero) or who rejected it. Released rows show small printer, fax and mail icons once the document has been printed, faxed or emailed. - Open a document. Click a row (or move with the arrow keys and press Enter). On a wide screen it opens on the right; in the Patient Information dialog or a narrow window the list gives way to the document, with a back arrow to return.
?section=forms-letters&request=REQ-…, so a copied link opens the same document for a colleague who can see it. In the Inbox, a form request has Open in Forms & Letters, which opens the same document here for anyone who needs to print, fax or email it, or release it for a provider (7.43).A patient with nothing yet shows No forms or letters yet with four quick-start tiles: Work note, School note, Form from the library and Upload their form. Everything here also appears on the visit it came from, in the encounter’s Forms & Letters section, and the patient finds released documents in the portal under Letters & Forms (What the patient sees).
Start a work note, school note or form for a patient who asks
When a patient calls, walks in, faxes or emails for a note or a form, enter it here instead of asking them to use the portal. It becomes the patient’s own request: it shows in their portal like one they made themselves, and Hero checks the visits exactly as it does for a portal request.
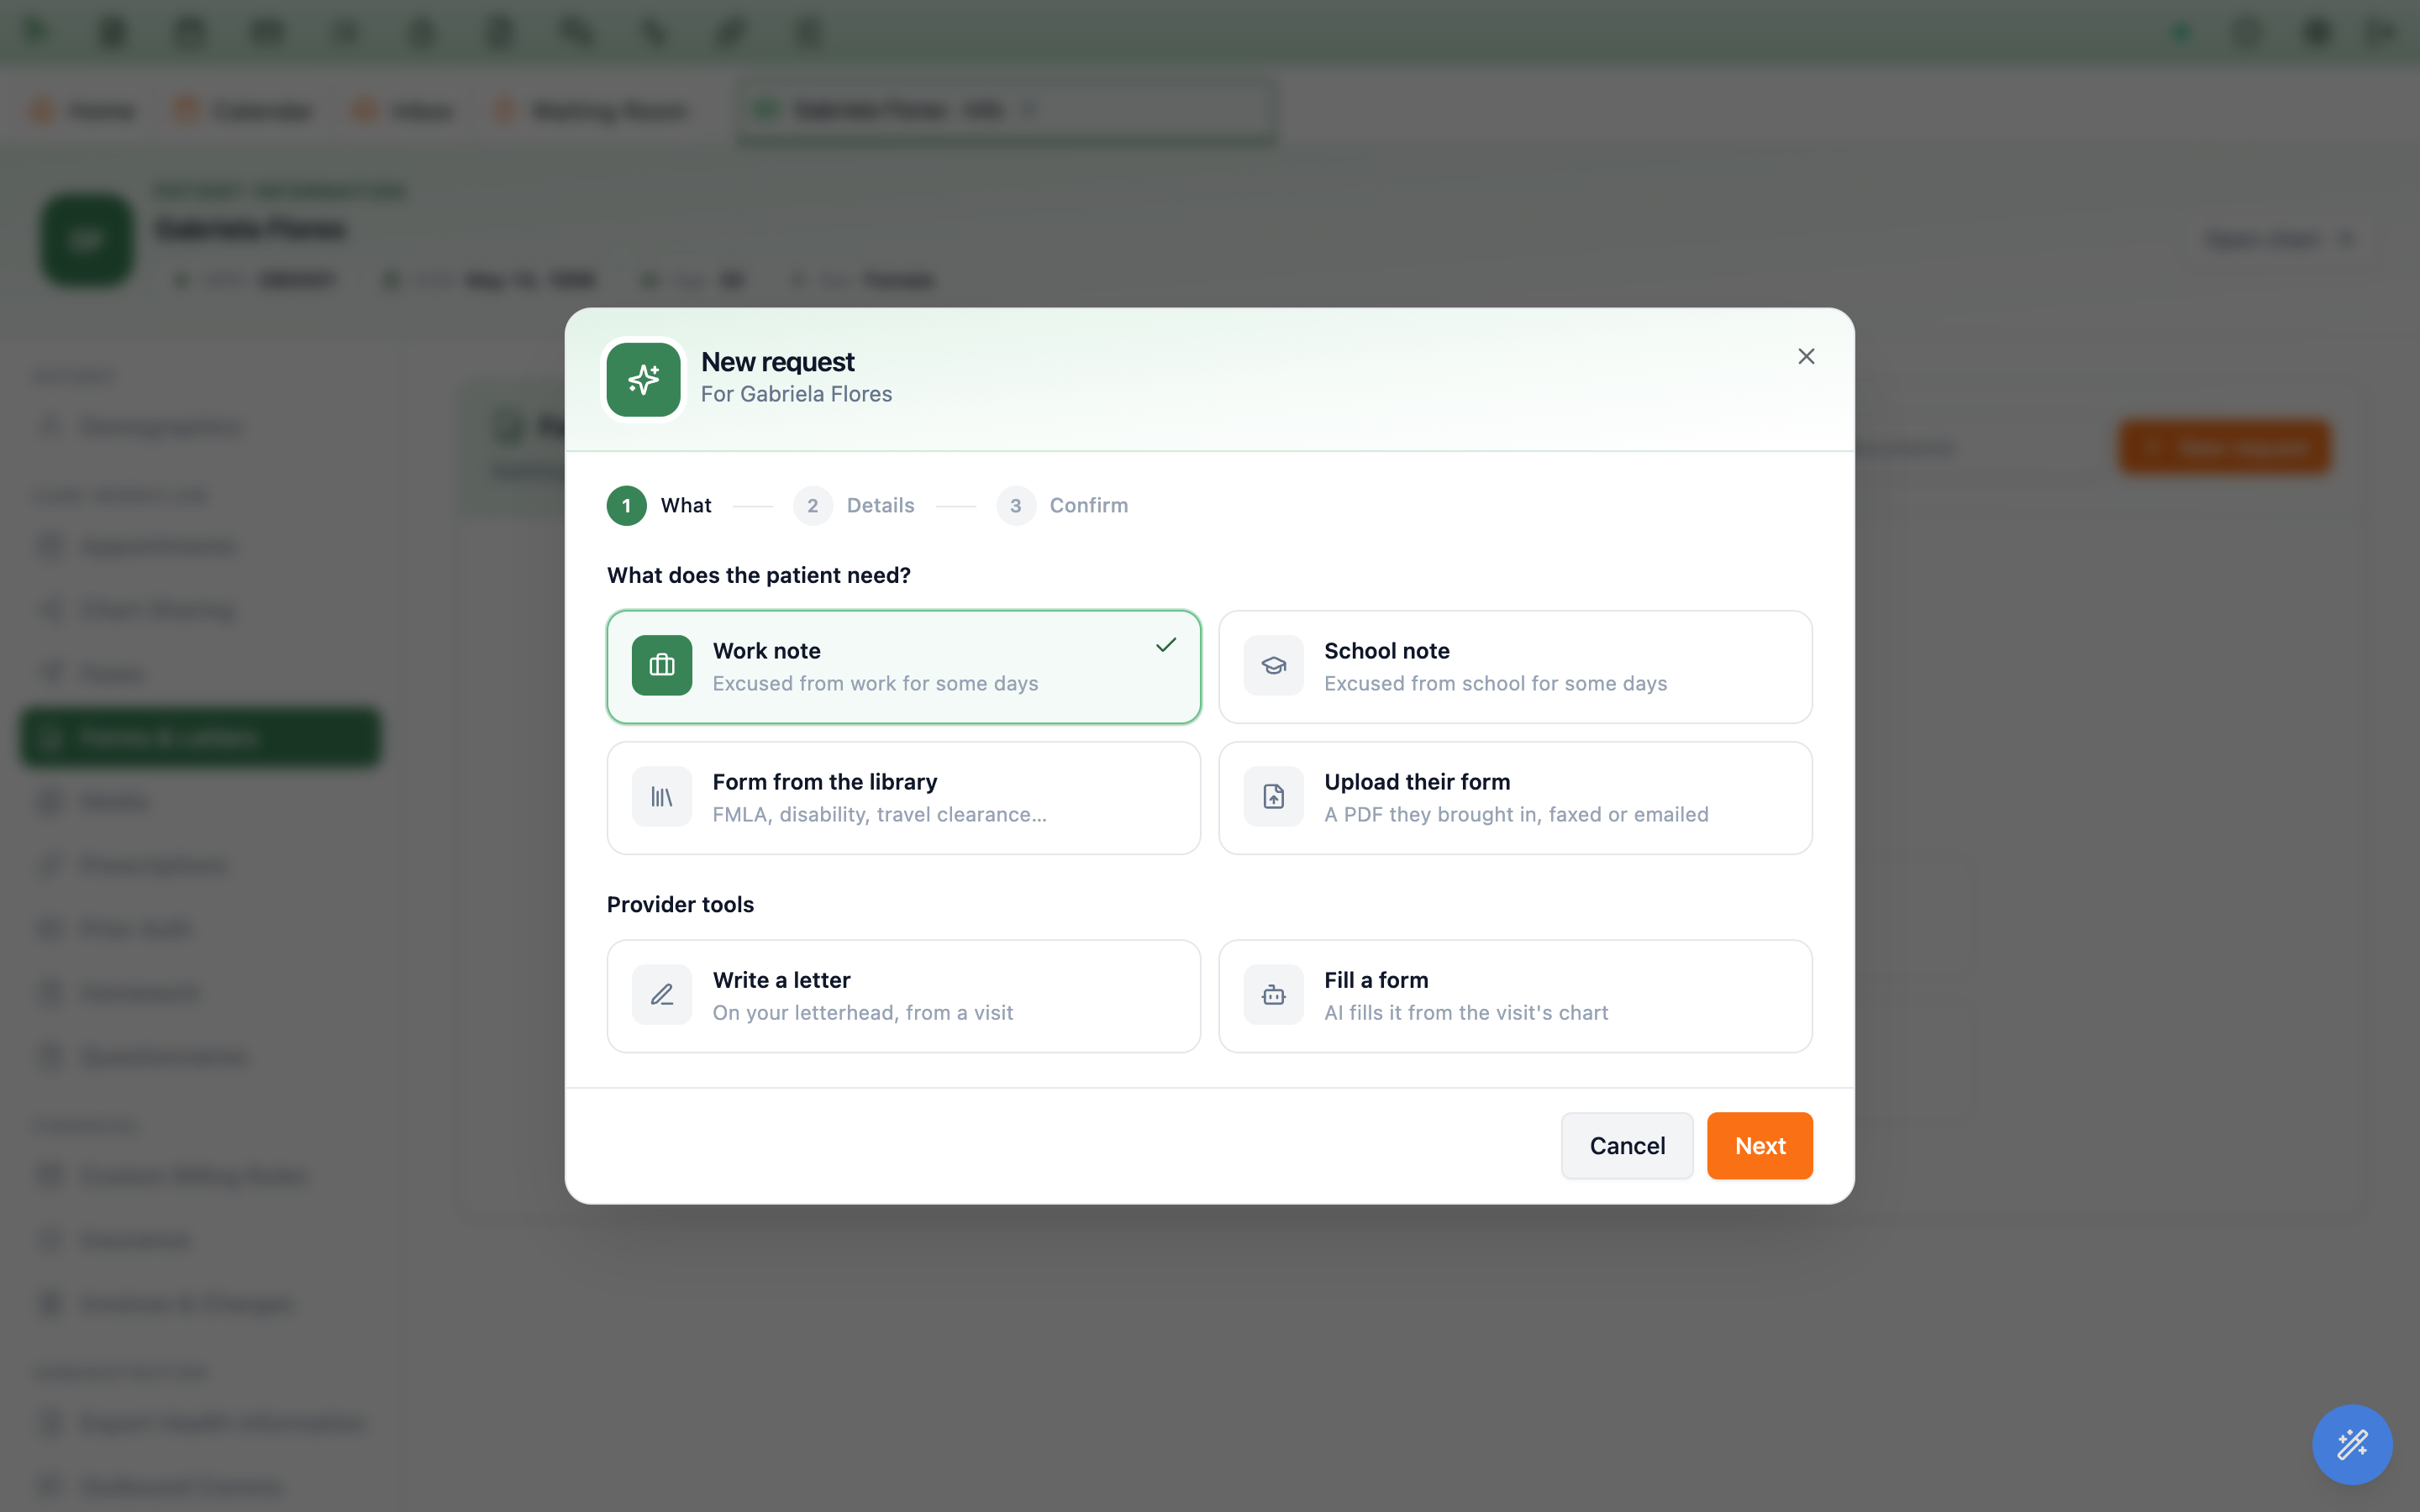
New request. Provider tools appear only for providers.-
Click
New request. The dialog has three steps:What,DetailsandConfirm. -
Choose what the patient needs.
Work note(excused from work for some days),School note(excused from school),Form from the library(FMLA, state paid leave, disability, travel clearance and the other forms in the library; search by name) orUpload their form(the PDF the patient brought in, faxed or emailed; PDF only, up to 50 MB). ThenNext. -
Pick the visits.
Under
Which visits?the patient’s visits show as chips, newest first, with the newest one already chosen — check that it is the visit the note is about (Show all … visitslists older ones). The document is written from the visits you pick, and the provider of the visit is the provider the note names. Only visits a letter can come from are offered; if there are none you seeNo visit can be used yet. A form or letter is written from one of the patient’s visits. -
For a work or school note, set the days.
First dayandLast daystart on today; the last day cannot be before the first. -
Write what they asked for (optional).
What did they ask for?carries the hintThe patient can see this.— write it the way you would to the patient, for example “Needs a note for work for the days out sick” or “Their employer needs it by Friday”. -
Say how they asked.
How did they ask?:Phone(the default),In person,Fax,EmailorOther. It becomes the source chip on the row. -
Check and start.
Confirmlists the request, the visits, the days, what they asked and how. ClickStart request.
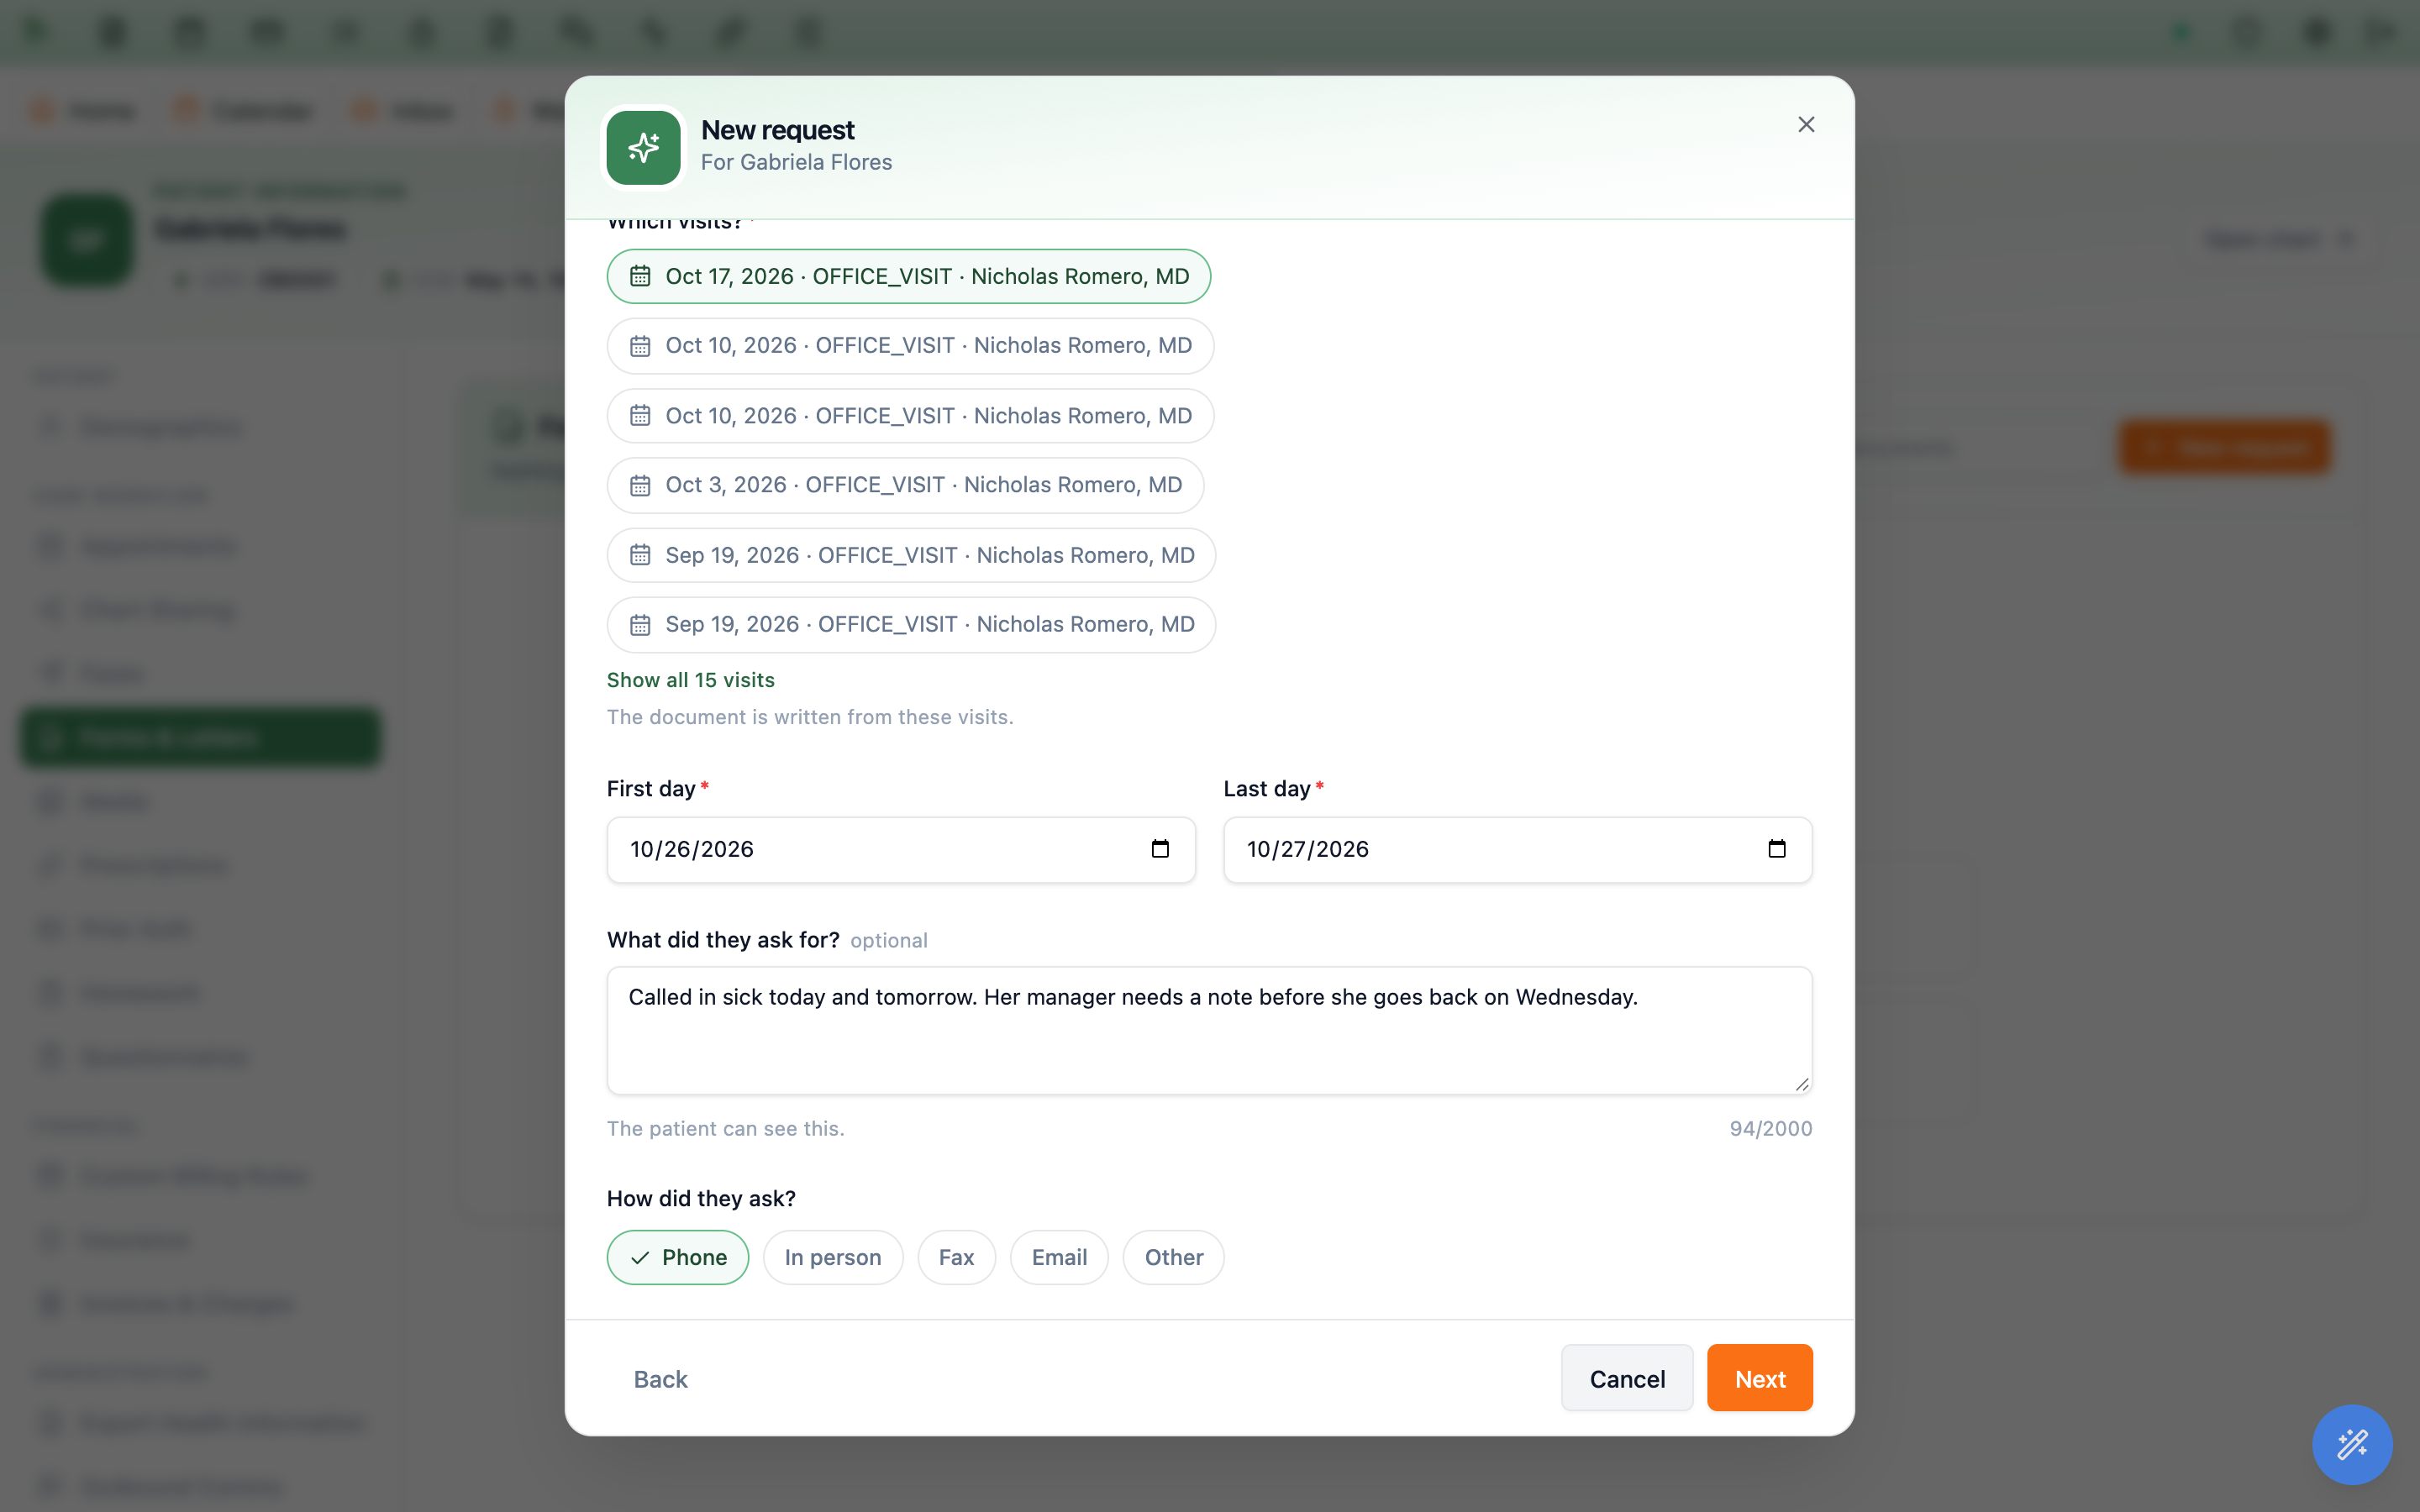
What happens next
- A work or school note is written straight away (no AI) and waits under
Needs review. - A form from the library or an uploaded form is drafted in the background. It shows under
In progresswithDrafting…(“This usually takes under a minute.”) and opens on its own when the draft is ready. - The patient sees the request in their portal at once, and the finished document only once it is released.
- Nothing goes out yet. Every request waits for someone to review and release it (7.40).
Providers also see Provider tools: Write a letter (“On your letterhead, from a visit”) and Fill a form (“AI fills it from the visit’s chart”). After you choose one visit they open the same tools as encounter completion — Write a letter and Fill a form with AI. A letter you save without signing shows under In progress as Draft, with Open the letter and Delete draft.
Check the draft, then Approve & send yourself or Sign for a provider
Open a row under Needs review. The header says how and when the patient asked, who entered it and which visit it came from, for example By phone on Oct 26, 2026 · entered by Maria L. · visit Oct 24, 2026 with Jane Romero, MD. Below it is the document itself (zoom and pages; after a quick edit, Original and Quick edit switch between versions). Below it (beside it on a wide screen):
Patient’s request: theDaysthey asked for andWhat they asked, in their words or yours.AI summary, for a form the AI filled.Sign for(staff and administrators) orSignature(a provider approving their own document).Activity, everything that has happened to it (7.43).
Read every field before you approve. The buttons along the bottom are Reject, Edit, Withdraw (for a request entered from this screen) and Approve & send.
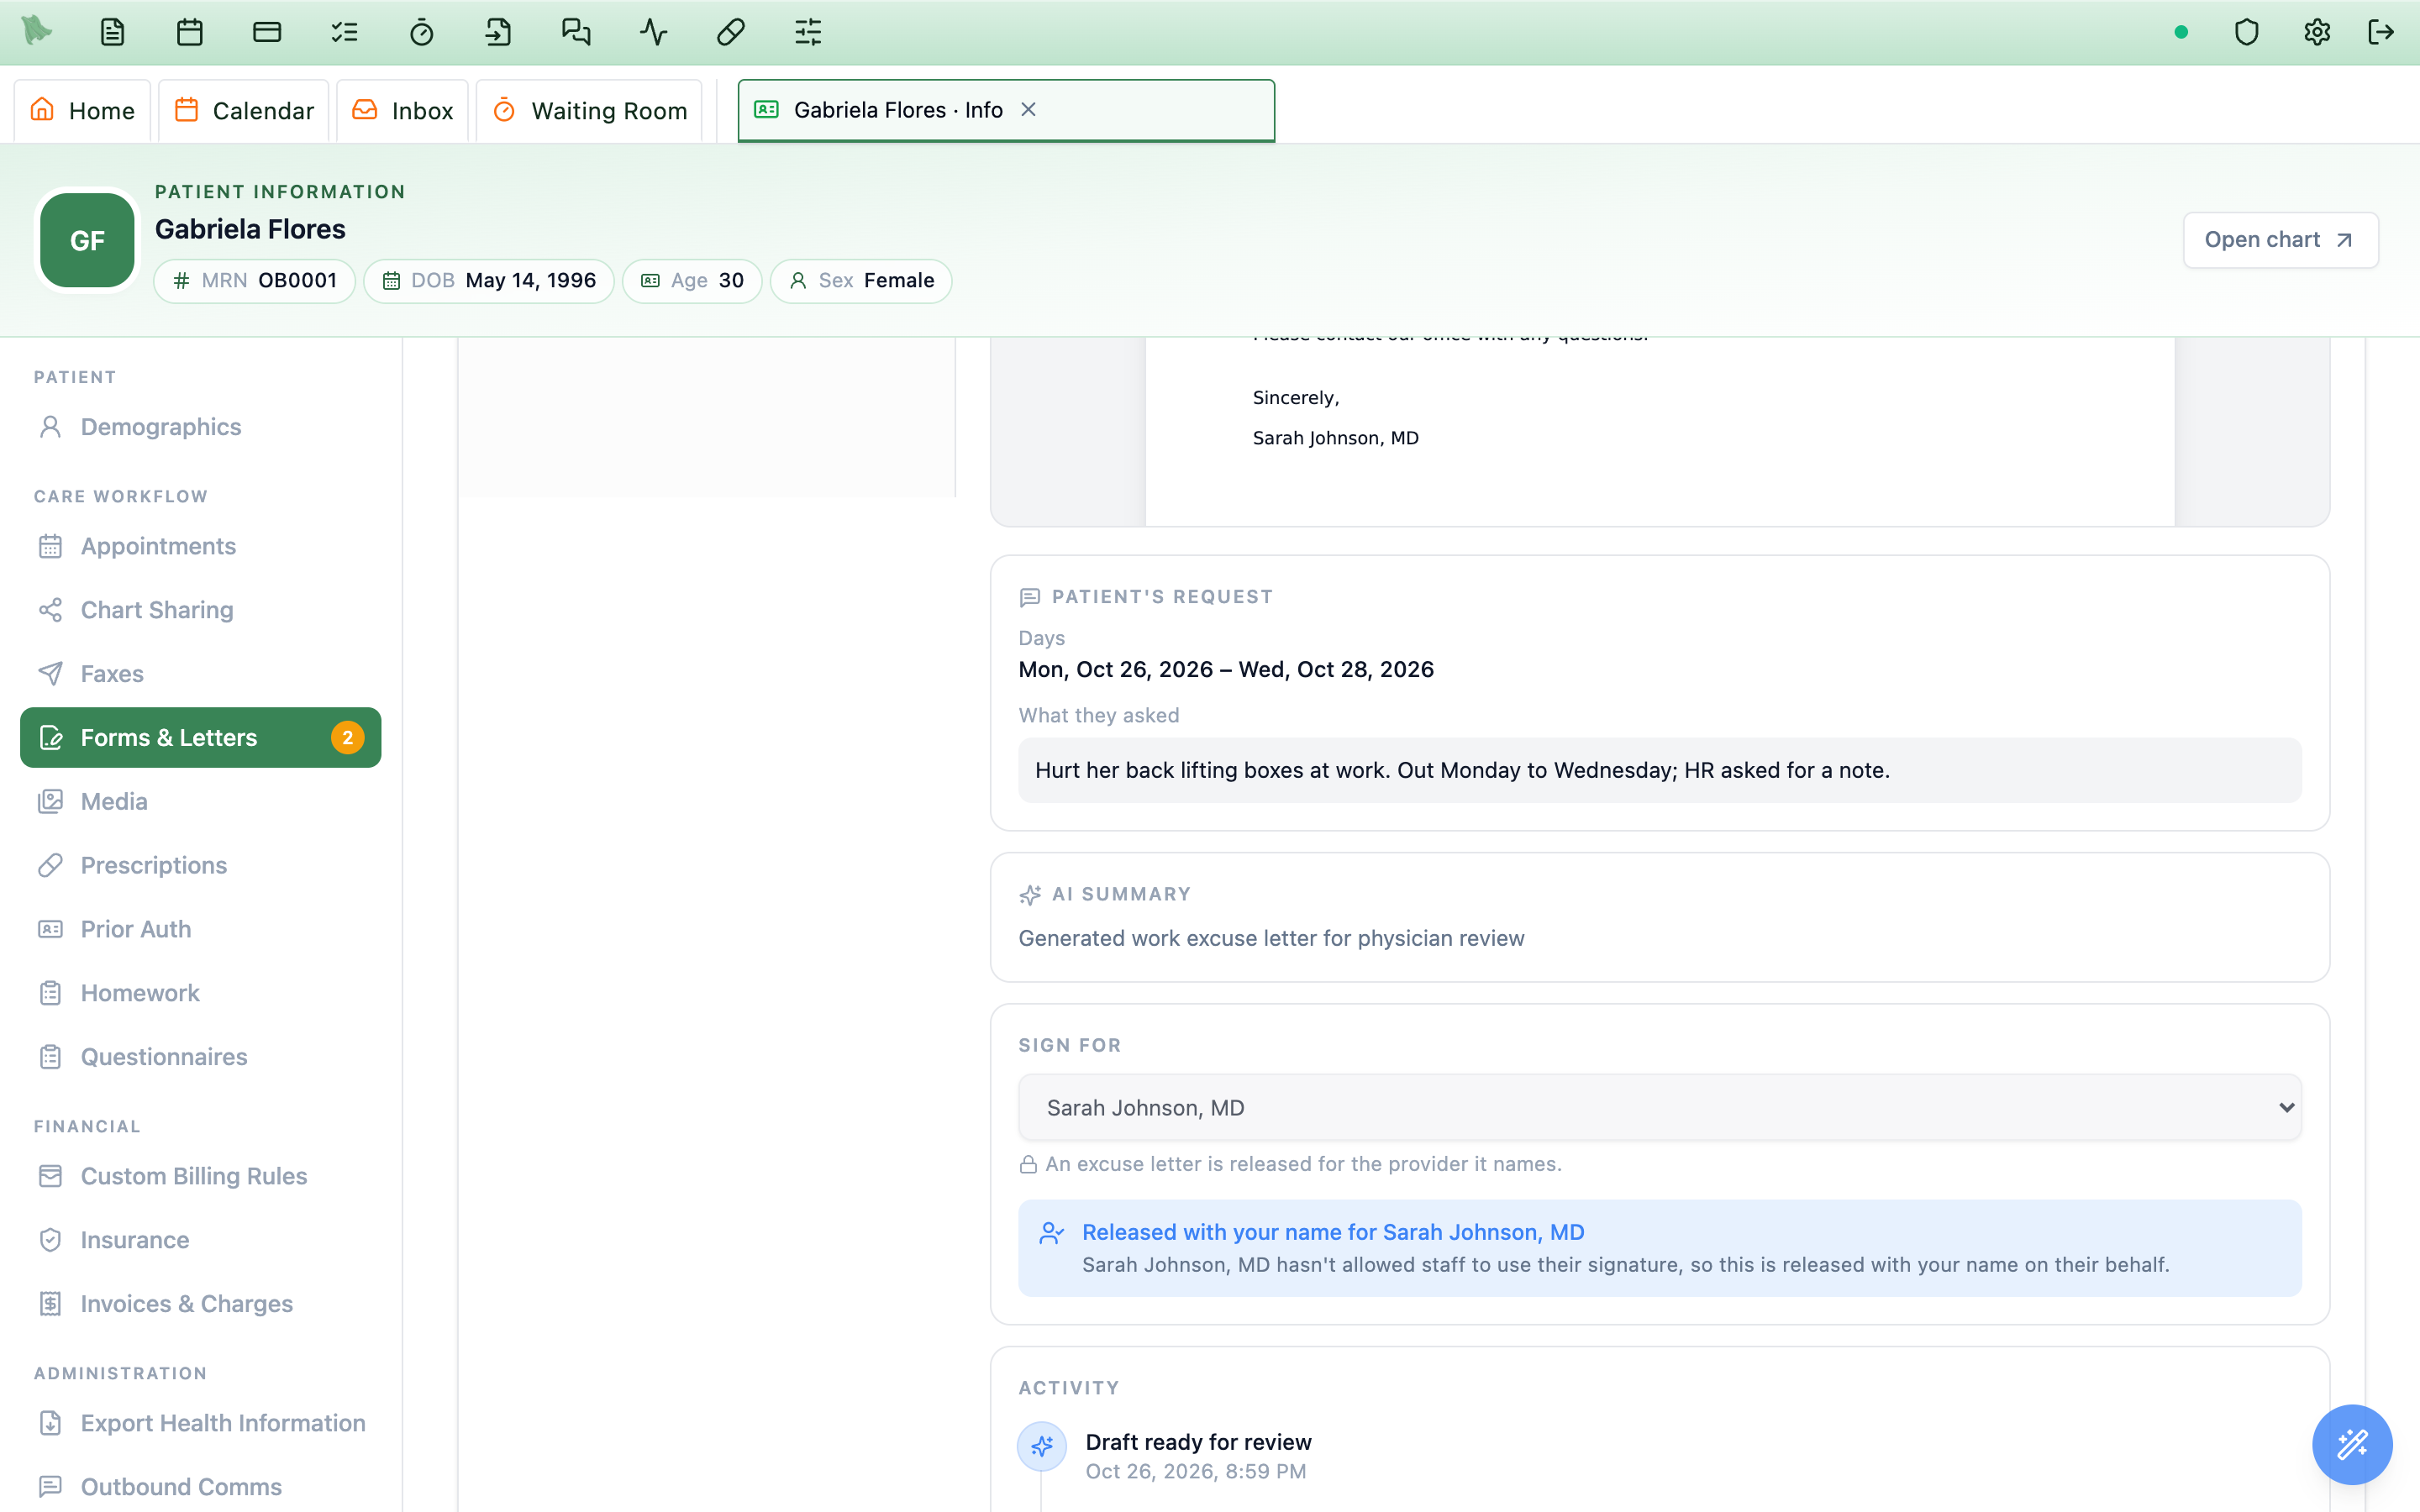
Sign for is locked to Dr. Johnson, and says plainly that Dr. Johnson’s signature will not be used.Sign for: who the document is released for
When a staff member or administrator approves, the Sign for card asks which provider the document is released for. It starts on the request’s provider. For a work or school note it is locked to the provider the letter names, with the line An excuse letter is released for the provider it names. For other forms, choose the provider in the menu; Approve & send stays unavailable until one is chosen. Under the menu the card says which of two things will happen:
With the provider’s signature
The card reads Uses Jane Romero, MD’s signature. The provider has turned on Let my staff release forms and letters with my signature and has a saved signature. Their signature is stamped as usual, with a line under it saying you released it: “Released by Maria Lopez (Medical Assistant) for Jane Romero, MD · Oct 26, 2026”.
With your name instead
The card reads Released with your name for Jane Romero, MD: the provider has not allowed staff to use their signature, or has no saved signature yet. No signature image is used. In its place the PDF carries “Approved for Jane Romero, MD by Maria Lopez (Medical Assistant) · Oct 26, 2026”.
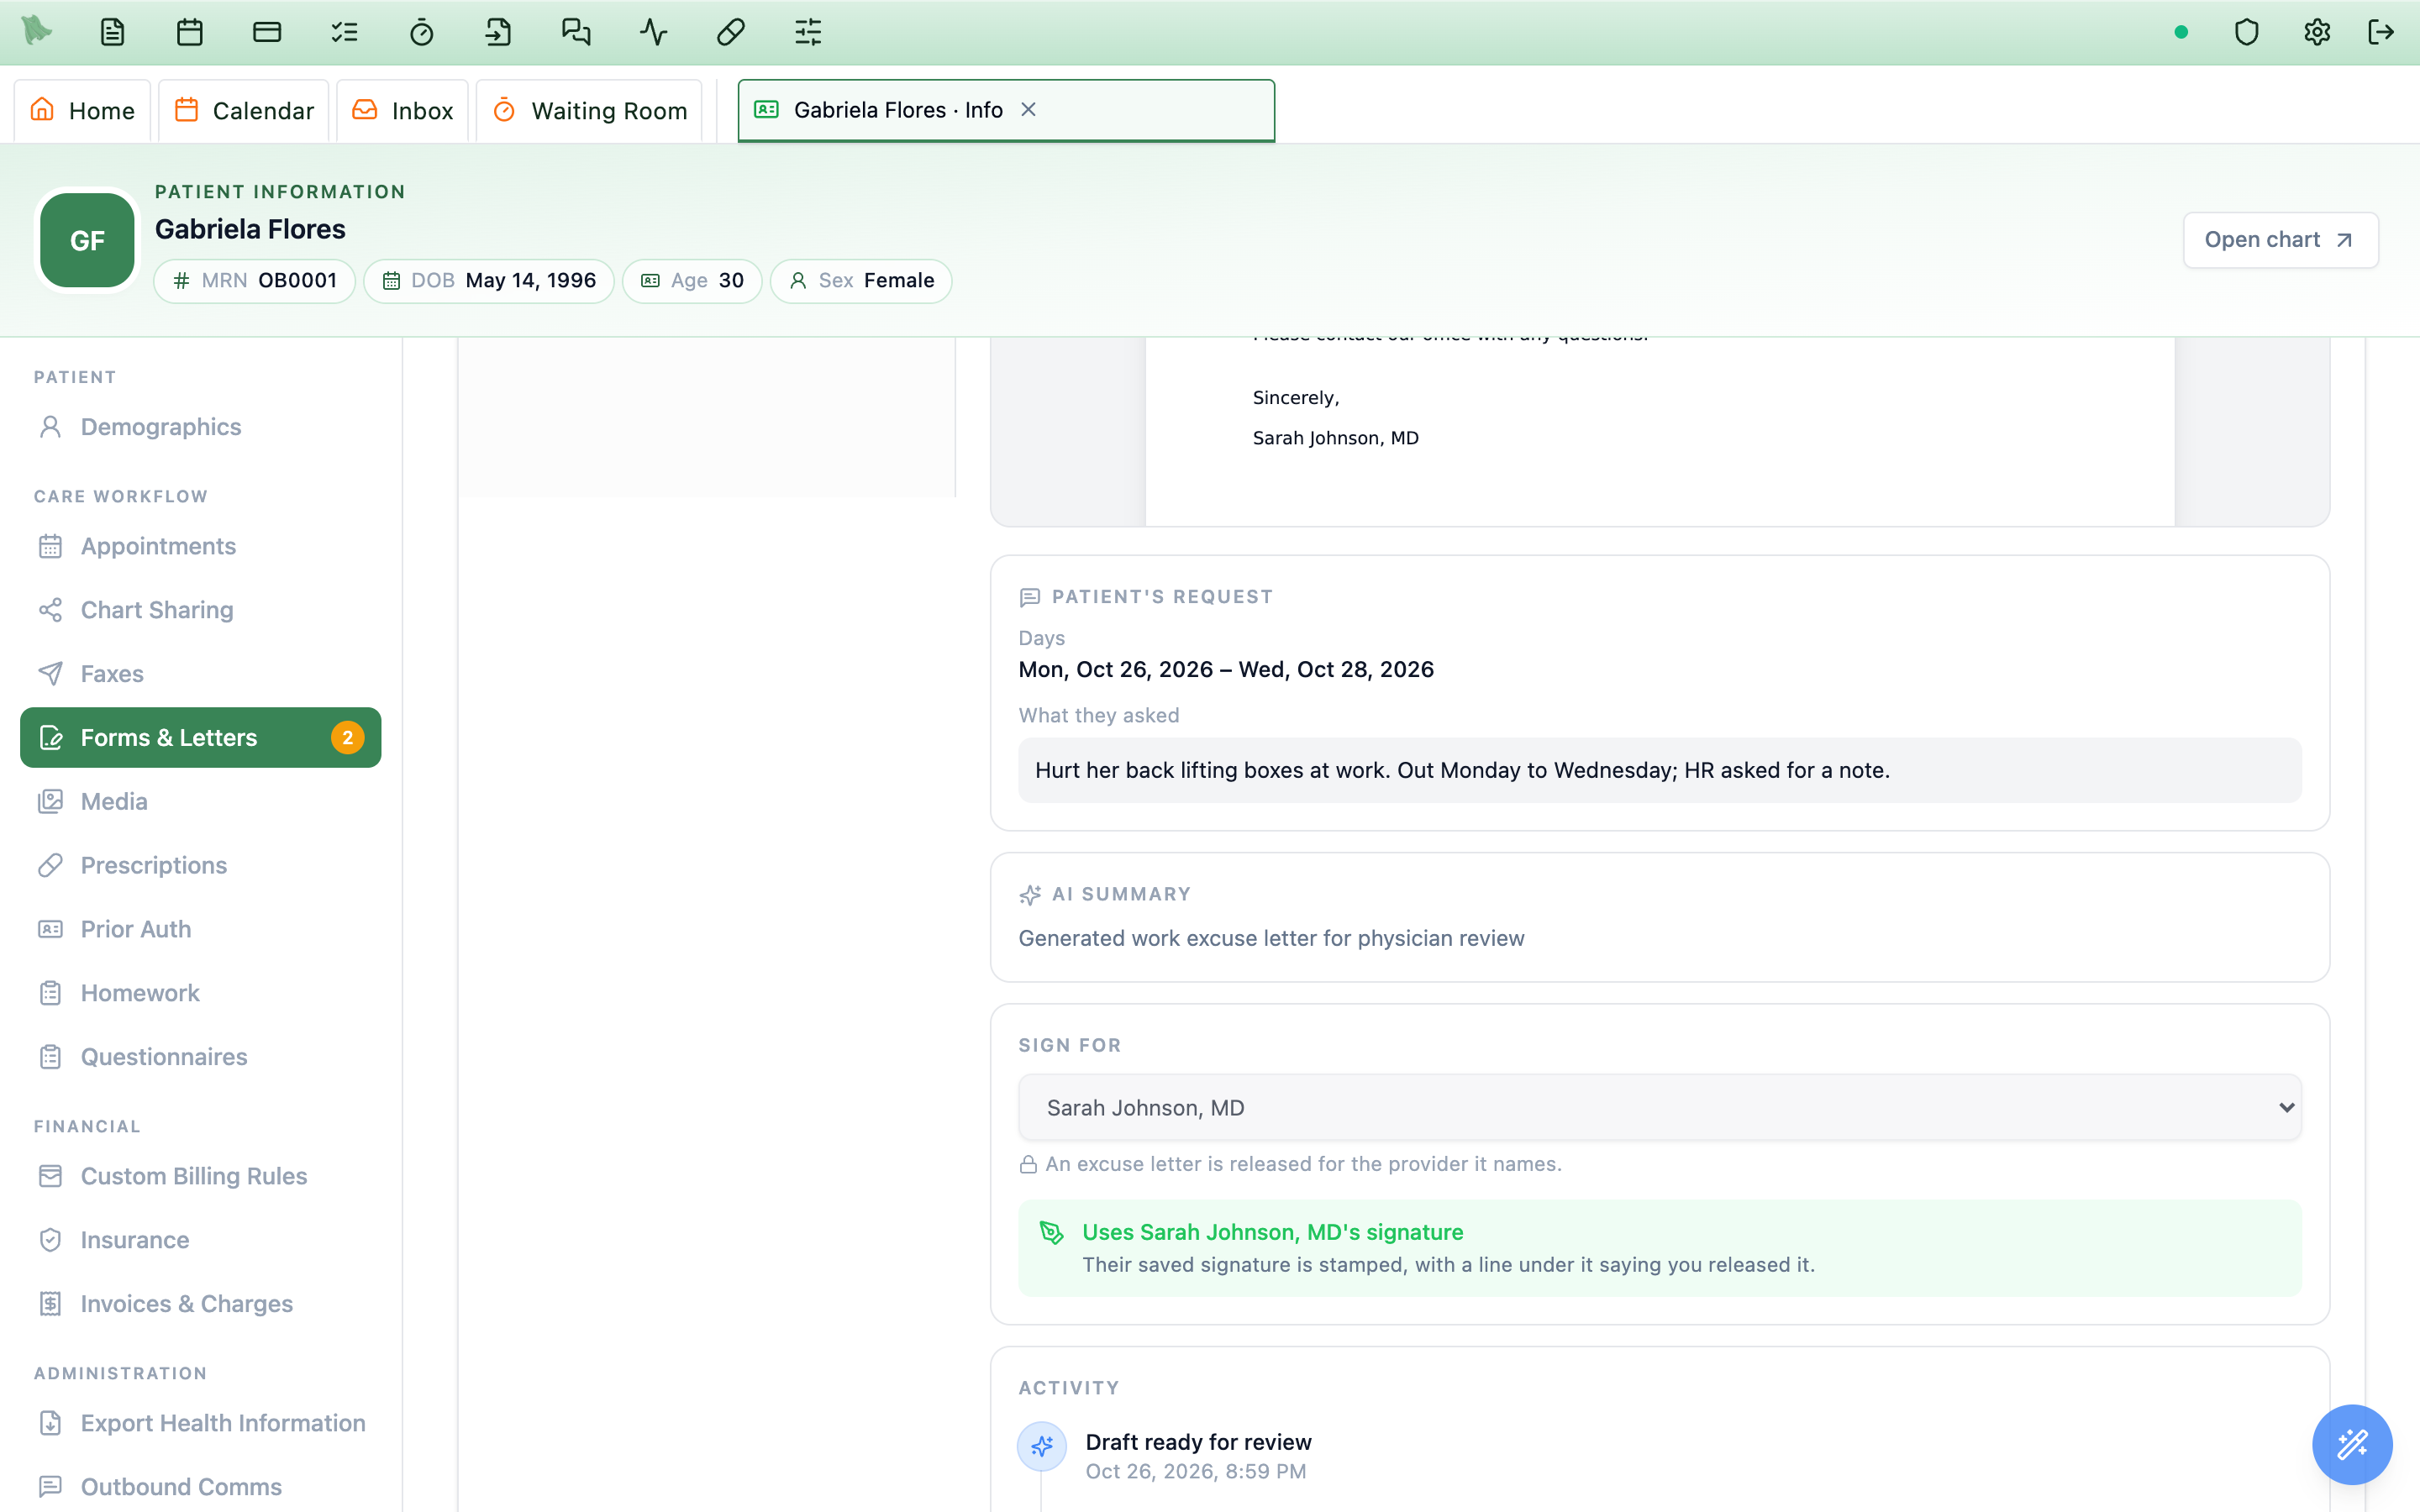
The name and role in that line are yours (your role profile, such as Medical Assistant or Front Desk; Administrator for an administrator) and the date is today in your practice’s time zone. The line goes where the signature would go: the form’s signature box, or beside its printed signature line. If the form has neither, approving opens Choose where to sign (with the provider’s signature) or Choose where the release note goes: click the spot on the page, then Release with Jane Romero, MD’s signature here or Place the release note here.
Approve & send
-
Click
Approve & send(Approve edit & sendwhile you are looking at a quick-edit version). -
Read the confirmation.
Staff see
Released for Jane Romero, MD— “The patient is told it is ready in their portal.” A provider approving their own seesApproved and sent. -
The document moves to History with a green banner, for example
Released Oct 26, 2026 by Maria L. for Jane Romero, MDand “Released without a signature image, with a line naming who released it and for whom.” A provider’s own approval readsSigned Oct 26, 2026 by Jane Romero, MD.
Providers approve with their own saved signature, exactly as in the Inbox; the Signature card shows Signed with your saved signature, or Create your signature before approving. with Create signature. A provider who approves a work or school note that names a different provider releases it for that provider, the same way staff do.
Not in portal, and its banner says “Filed in the chart; not shared in the patient’s portal.”Fix the draft, turn the request down, or take back one entered by mistake
Edit
Edit opens a menu with the tools that fit the document:
| Choice | What it does | Offered for |
|---|---|---|
Edit PDF | Opens the PDF editor: type into fields, fix values, then save. The saved PDF becomes the version you approve (“Review the updated document, then approve.”). | Every document waiting for review |
Quick edit (AI) | Type what should change under What should change? (“Return-to-work date is 11/2; restrict lifting to 10 lbs”) and click Rewrite. The edited version opens when it is ready; switch between Original and Quick edit to compare. | Forms and letters other than work and school notes |
Change dates | Change the dates asks for a new First day and Last day; the letter is written again with those days. Nothing is sent until it is approved. | Work and school notes |
If someone else releases or changes the document while you are editing, your edit is not saved over theirs: Hero refreshes the document and asks you to look again.
Reject
- Click
Reject. TheReject Form Requestdialog opens. - Write the note.
Add Rejection Notesis required. The patient sees it in their portal, so write it to them. - Attach a revised form if you have one (
Upload Revised Form (Optional), PDF up to 10 MB). - Click
Reject with Notes(Reject & Send Revised Formwith a file). The document moves to History asRejected, showing your note and, if you attached one,Download the revised form.
Withdraw a request entered by mistake
Withdraw appears only on a request someone entered from this screen (by phone, in person, fax, email or other) that has not been approved or rejected — for example one entered for the wrong patient. Withdraw this request? explains that it is removed from the patient’s list and that the activity keeps a record of it; add an optional reason under Why and click Withdraw. A request the patient made in the portal cannot be withdrawn; reject it with a note instead.
When a draft fails
A failed draft shows The draft could not be made. For a form from the library, Try again drafts it again. An uploaded form is not kept after a failure, so the button is Upload the form again, which opens New request with the visits, note and source already filled in. You can also reject the request with a note for the patient.
Send a released document where the patient needs it
Open any released document in History. Along the bottom are Print, Fax, Email and Download, all for the signed PDF, exactly as released.
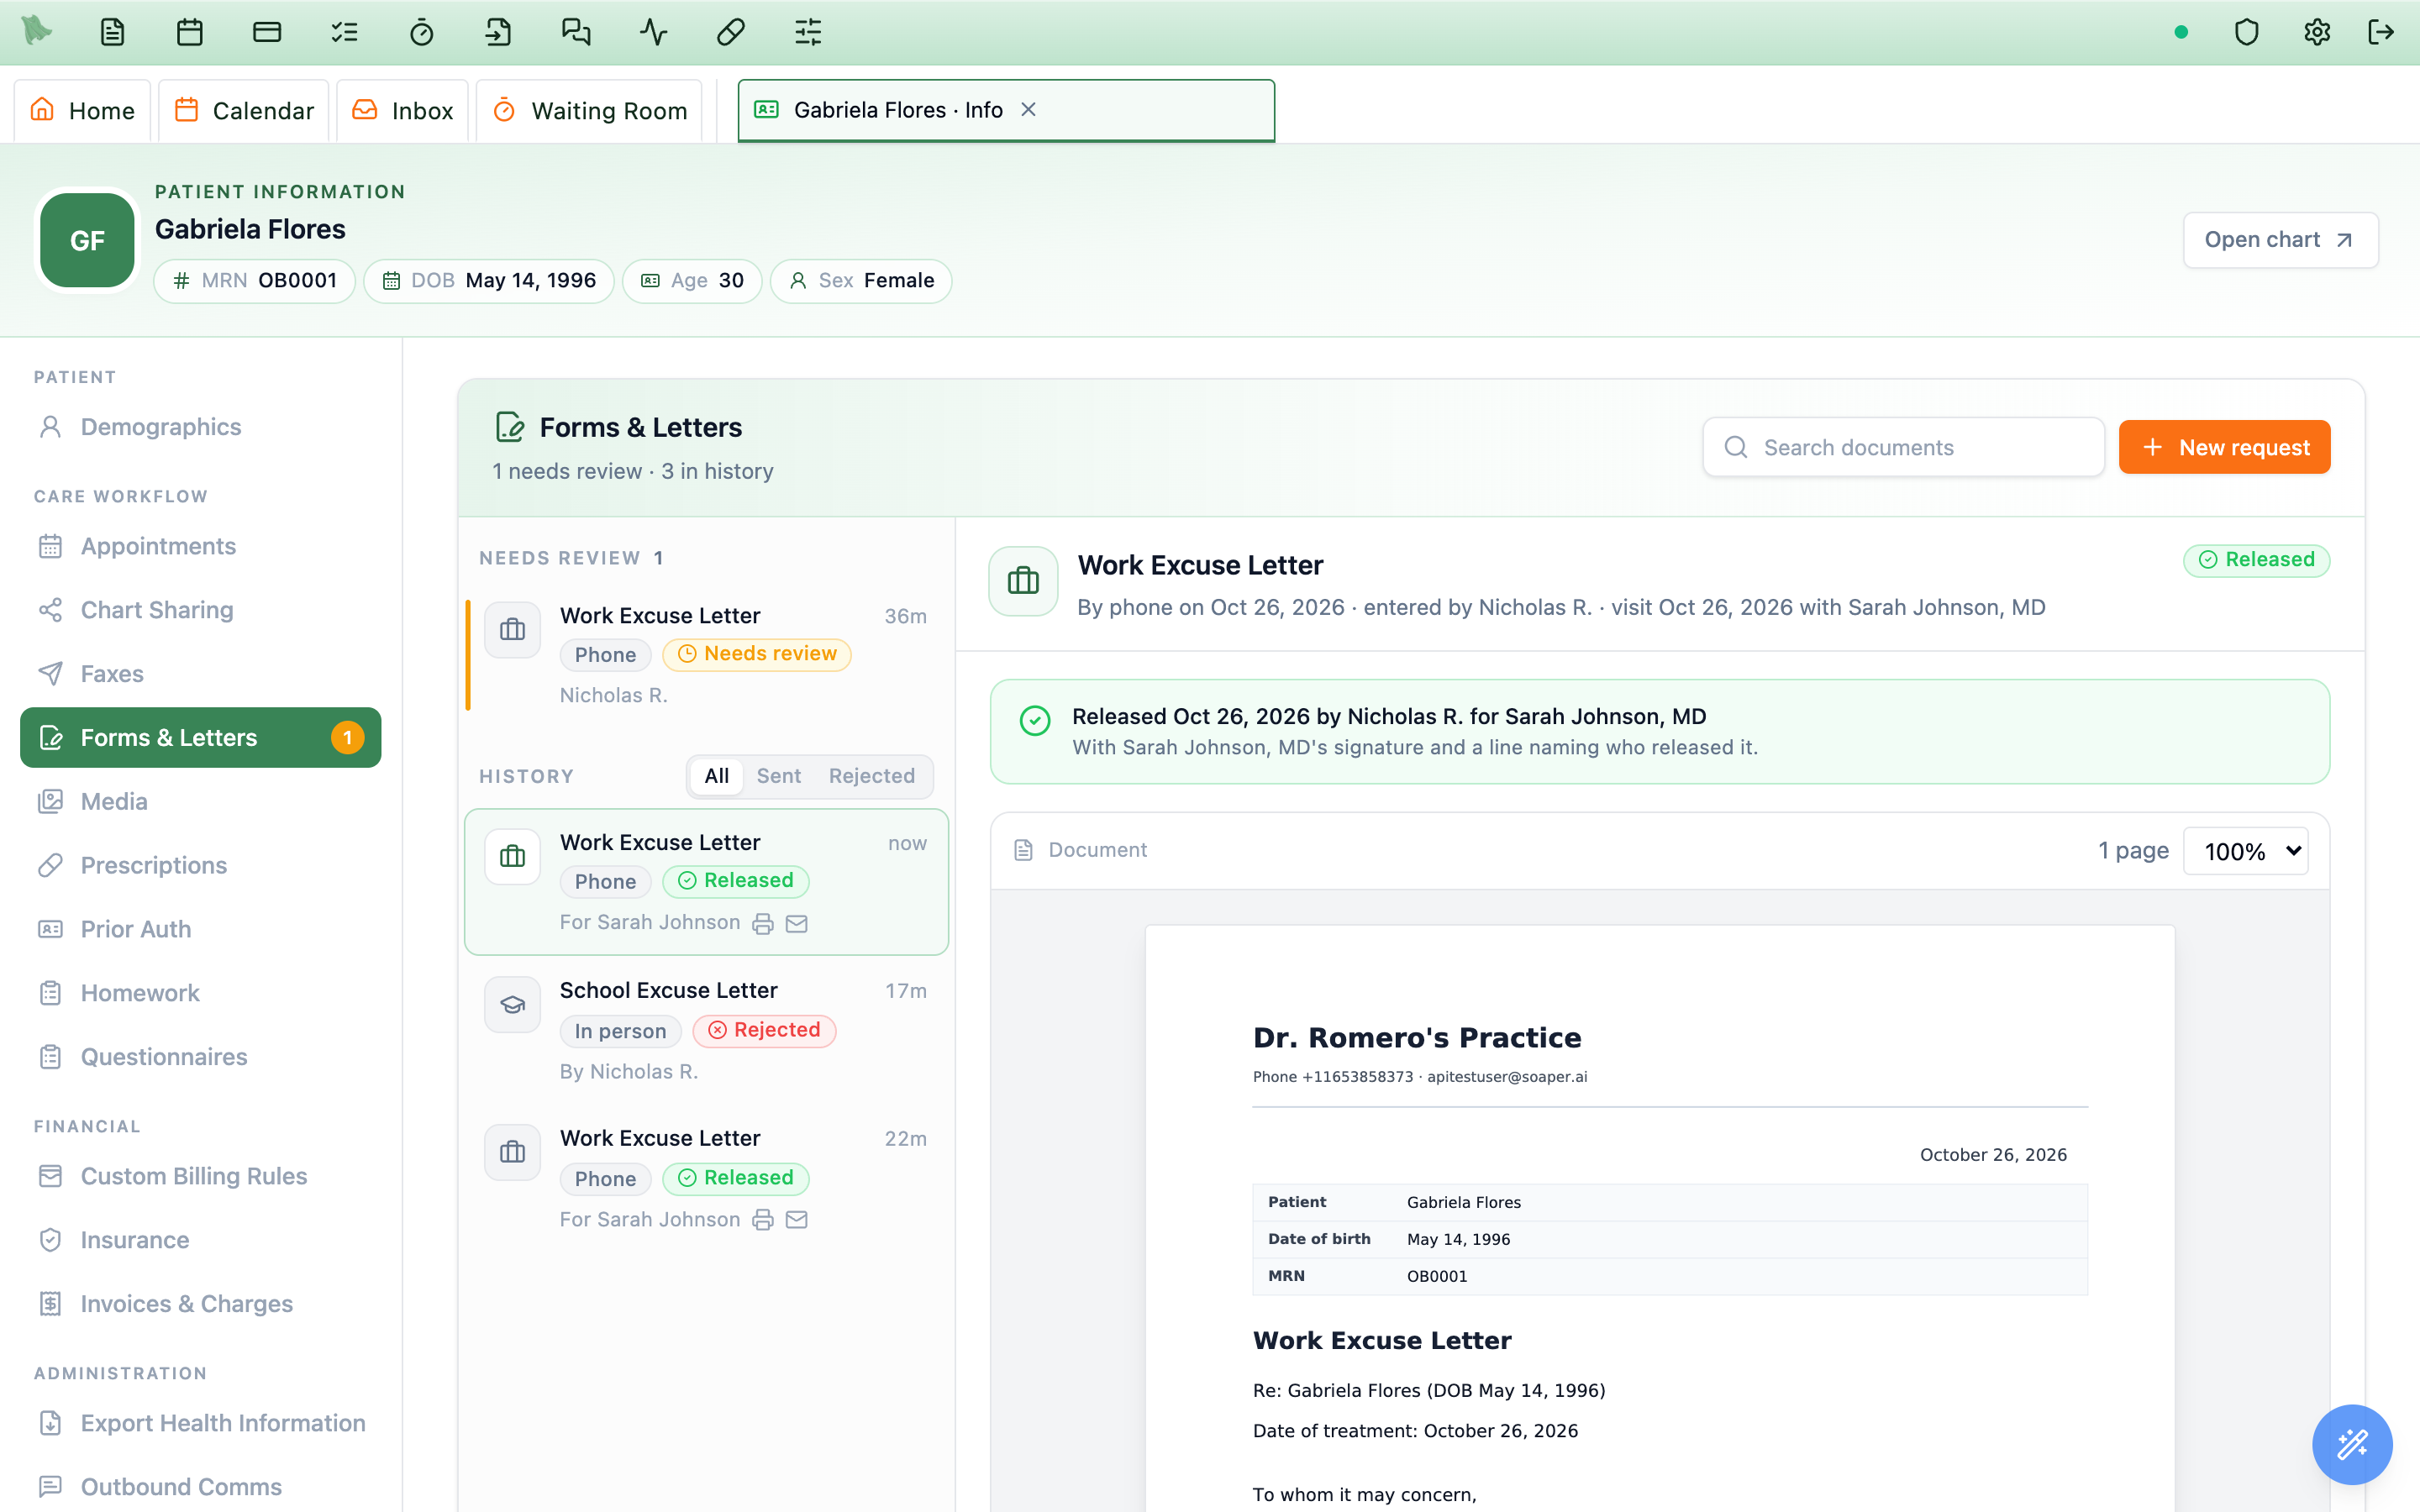
| Button | What it does | Who |
|---|---|---|
Print | Prints the released PDF. Every print is recorded in the chart’s audit log and in the document’s Activity. If the browser blocks it you see Printing didn’t start; download it and print from there. | Everyone who can see the tab |
Fax | Opens Send fax with the released PDF attached (“Faxes the released document. The fax shows in its activity.”). Choose the number, check the cover page, send. Only when your practice has a fax service. | Providers, and staff whose permissions include filing documents (Import documents into the medical record). The default Front Desk, Medical Assistant and Nurse profiles don’t include it, so they see an error when they send; a practice administrator can add it per person in Staff & assistants (4.3). |
Email | Sends a secure link, never the PDF itself (below). | Providers, administrators, staff with Forms & Letters |
Download | Saves the PDF to your computer. | Everyone who can see the tab |
Email a secure link
Email opens Email a secure link. The recipient gets an email holding only a link; to open it they also need an access code. The email never contains the document or any health details, and there is no message box, so nothing you type ends up in an email.
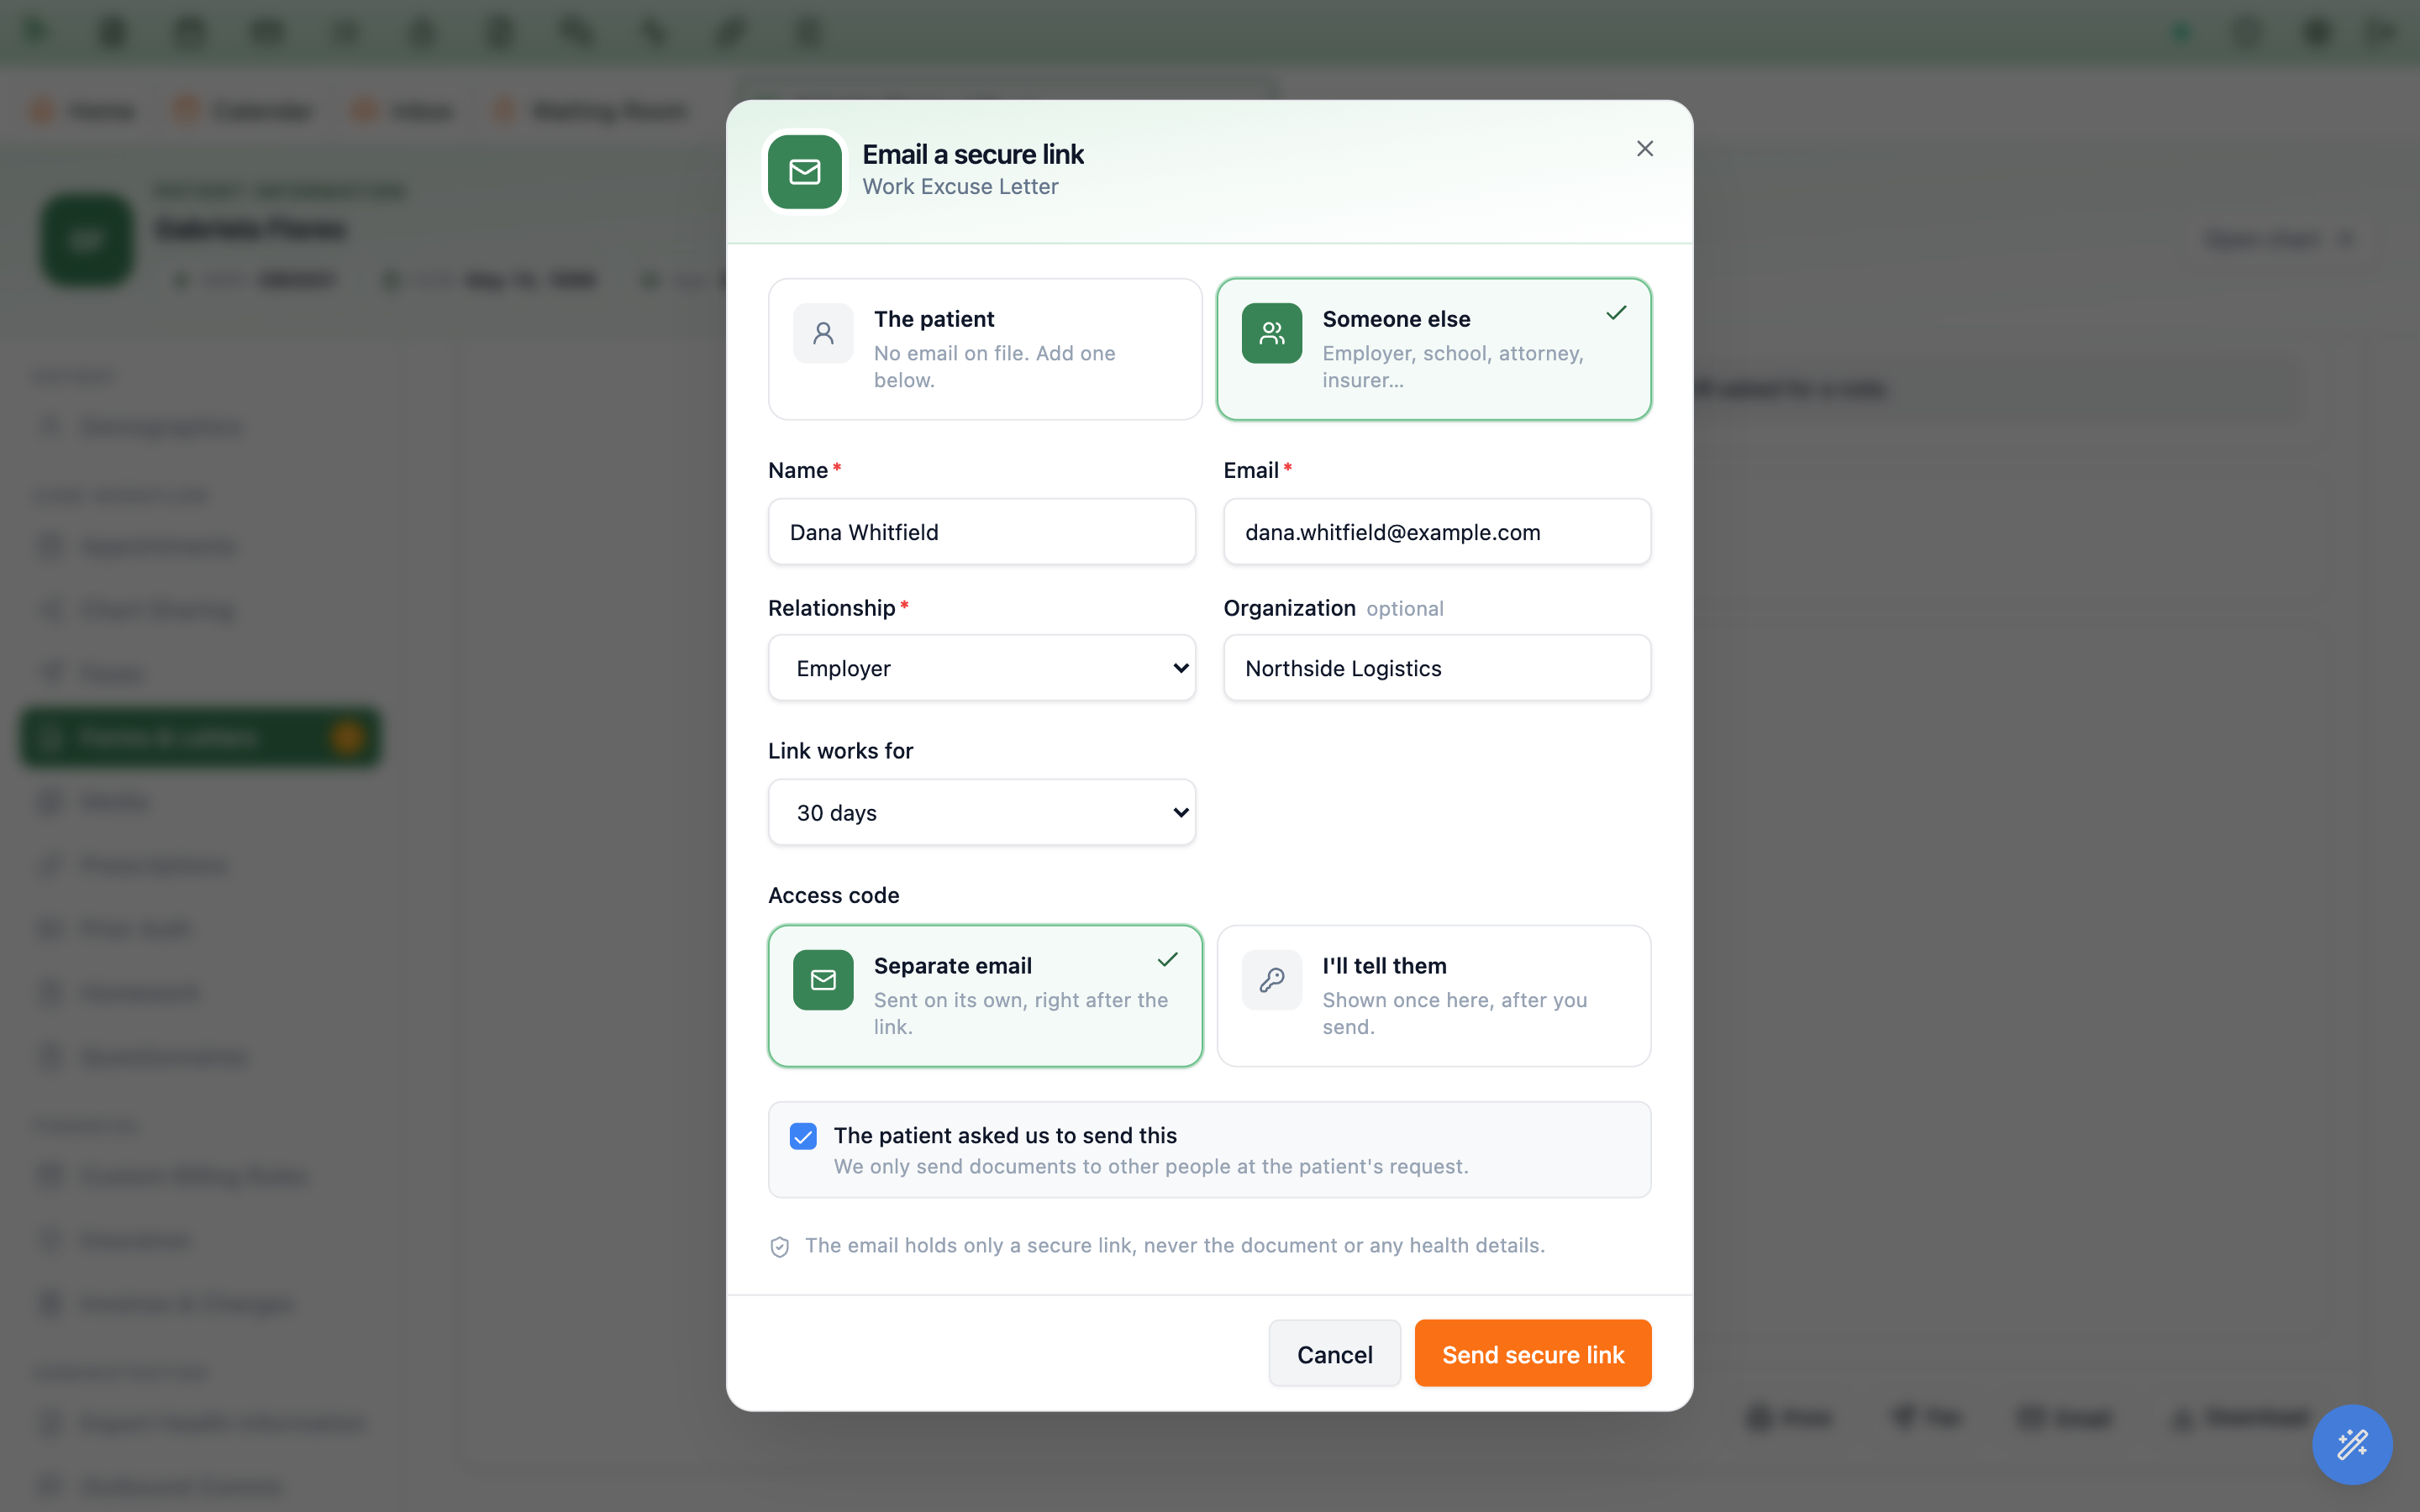
-
Choose who it goes to.
The patientuses the email on the chart (or asks for one when none is on file).Someone elseasks forName,Email,Relationship(Employer,School,Another provider,Legal representative,Attorney,InsurerorOther) and, optionally,Organization. -
Set how long it works.
Link works fordefaults to 30 days. -
Choose how the access code travels.
Separate email(the default) sends it on its own right after the link.I’ll tell themshows the code to you once, after you send, so you can read it out on the phone; it is never shown again. -
For anyone but the patient, confirm the patient asked.
Tick
The patient asked us to send this(“We only send documents to other people at the patient’s request.”). -
Click
Send secure link. Hero prepares the link (Preparing the secure link…) and emails it as soon as it is ready. Its progress and status show in the document’s Activity (7.43).
These links are Chart Sharing links for one document. Staff with Forms & Letters can send them without the Chart Sharing permission, and people with Share chart records also see them in the patient’s Chart Sharing tab.
See everything that happened to a document, and manage its links
Every document has an Activity card, newest first, with who did each thing and when (in your practice’s time zone). This is where you answer “who released this letter, and did the employer get it?”
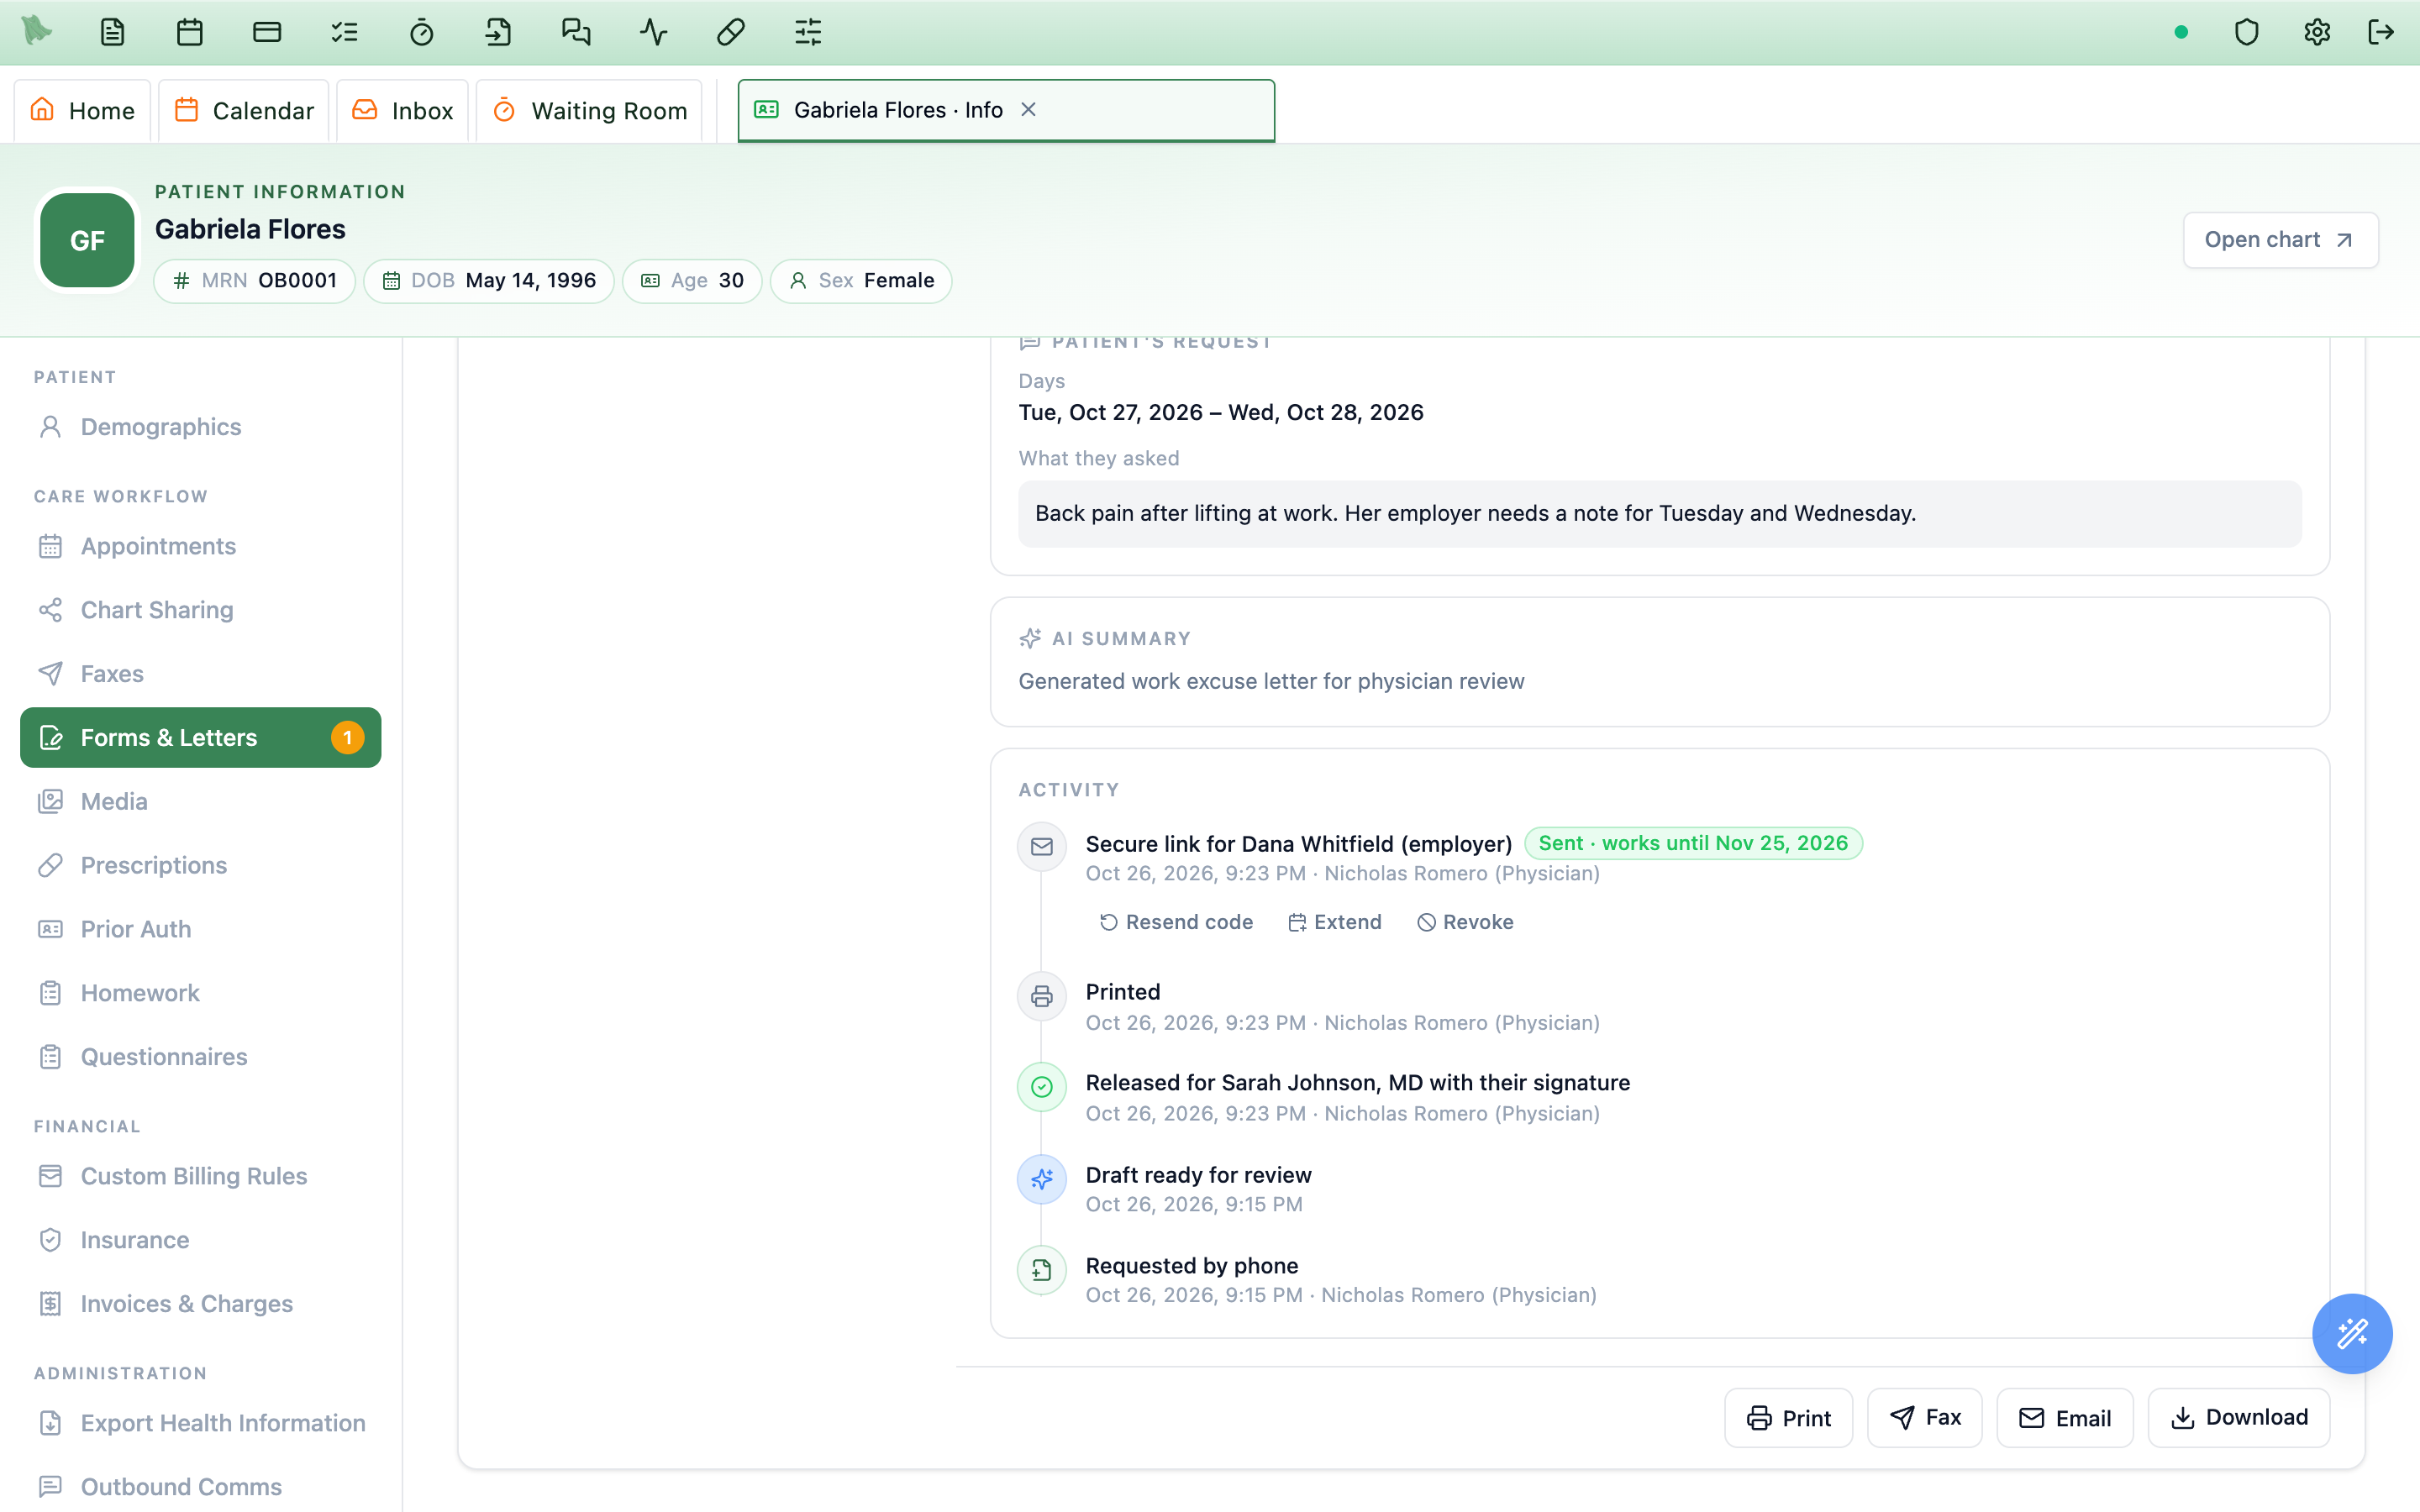
| Entry | Means |
|---|---|
Requested by phone (or in person, by fax, by email, in the portal) | The request was started, and by whom. |
Draft ready for review / The draft could not be made | The draft finished or failed. Draft started again follows a Try again. |
PDF edited, Quick edit, Dates changed | Someone edited the draft. |
Released for Jane Romero, MD / Released for Jane Romero, MD with their signature / Approved and signed | Released by staff with their name, released by staff with the provider’s signature, or approved by the provider themselves. The entry names the person who did it and their role. |
Rejected / Rejected with a revised form | Turned down, with or without a revised PDF. |
Withdrawn | Taken back as entered by mistake, with the reason if one was given. |
Printed | Each print. |
Faxed to … | Each fax, with its live status: Sending…, Delivered, Failed (hover for the reason) or Cancelled. |
Secure link for … | Each emailed link, with its status: Preparing the link…, Sent · works until …, The email didn’t go out, The access code email didn’t go out, Couldn’t be prepared, Revoked or Expired, and how many times it was opened. |
Manage a secure link
Under each link, people who can email documents get three buttons:
Resend code(orResend link) sends the emails again — use it when the recipient lost the code or an email did not go out.Extendadds days to a link that is about to run out (choose how many, thenExtend).Revokestops the link at once (“Revoke the link? It stops working at once.”) — use it when it went to the wrong address.
From the Inbox
A form request in the Inbox’s Forms/Letters view has Open in Forms & Letters, which opens the same document here. When a provider cannot approve it in the Inbox — for example a work note that names another provider — the Inbox says why, beside the same button, so it can be released for the right provider from here.
For providers: decide whether staff releases carry your signature
Staff can release a patient’s letter or form for you whatever you choose here. This setting decides only what the released PDF carries: your saved signature, or the staff member’s name released on your behalf. It is off until you turn it on, and only you can change it — not an administrator, not your staff.
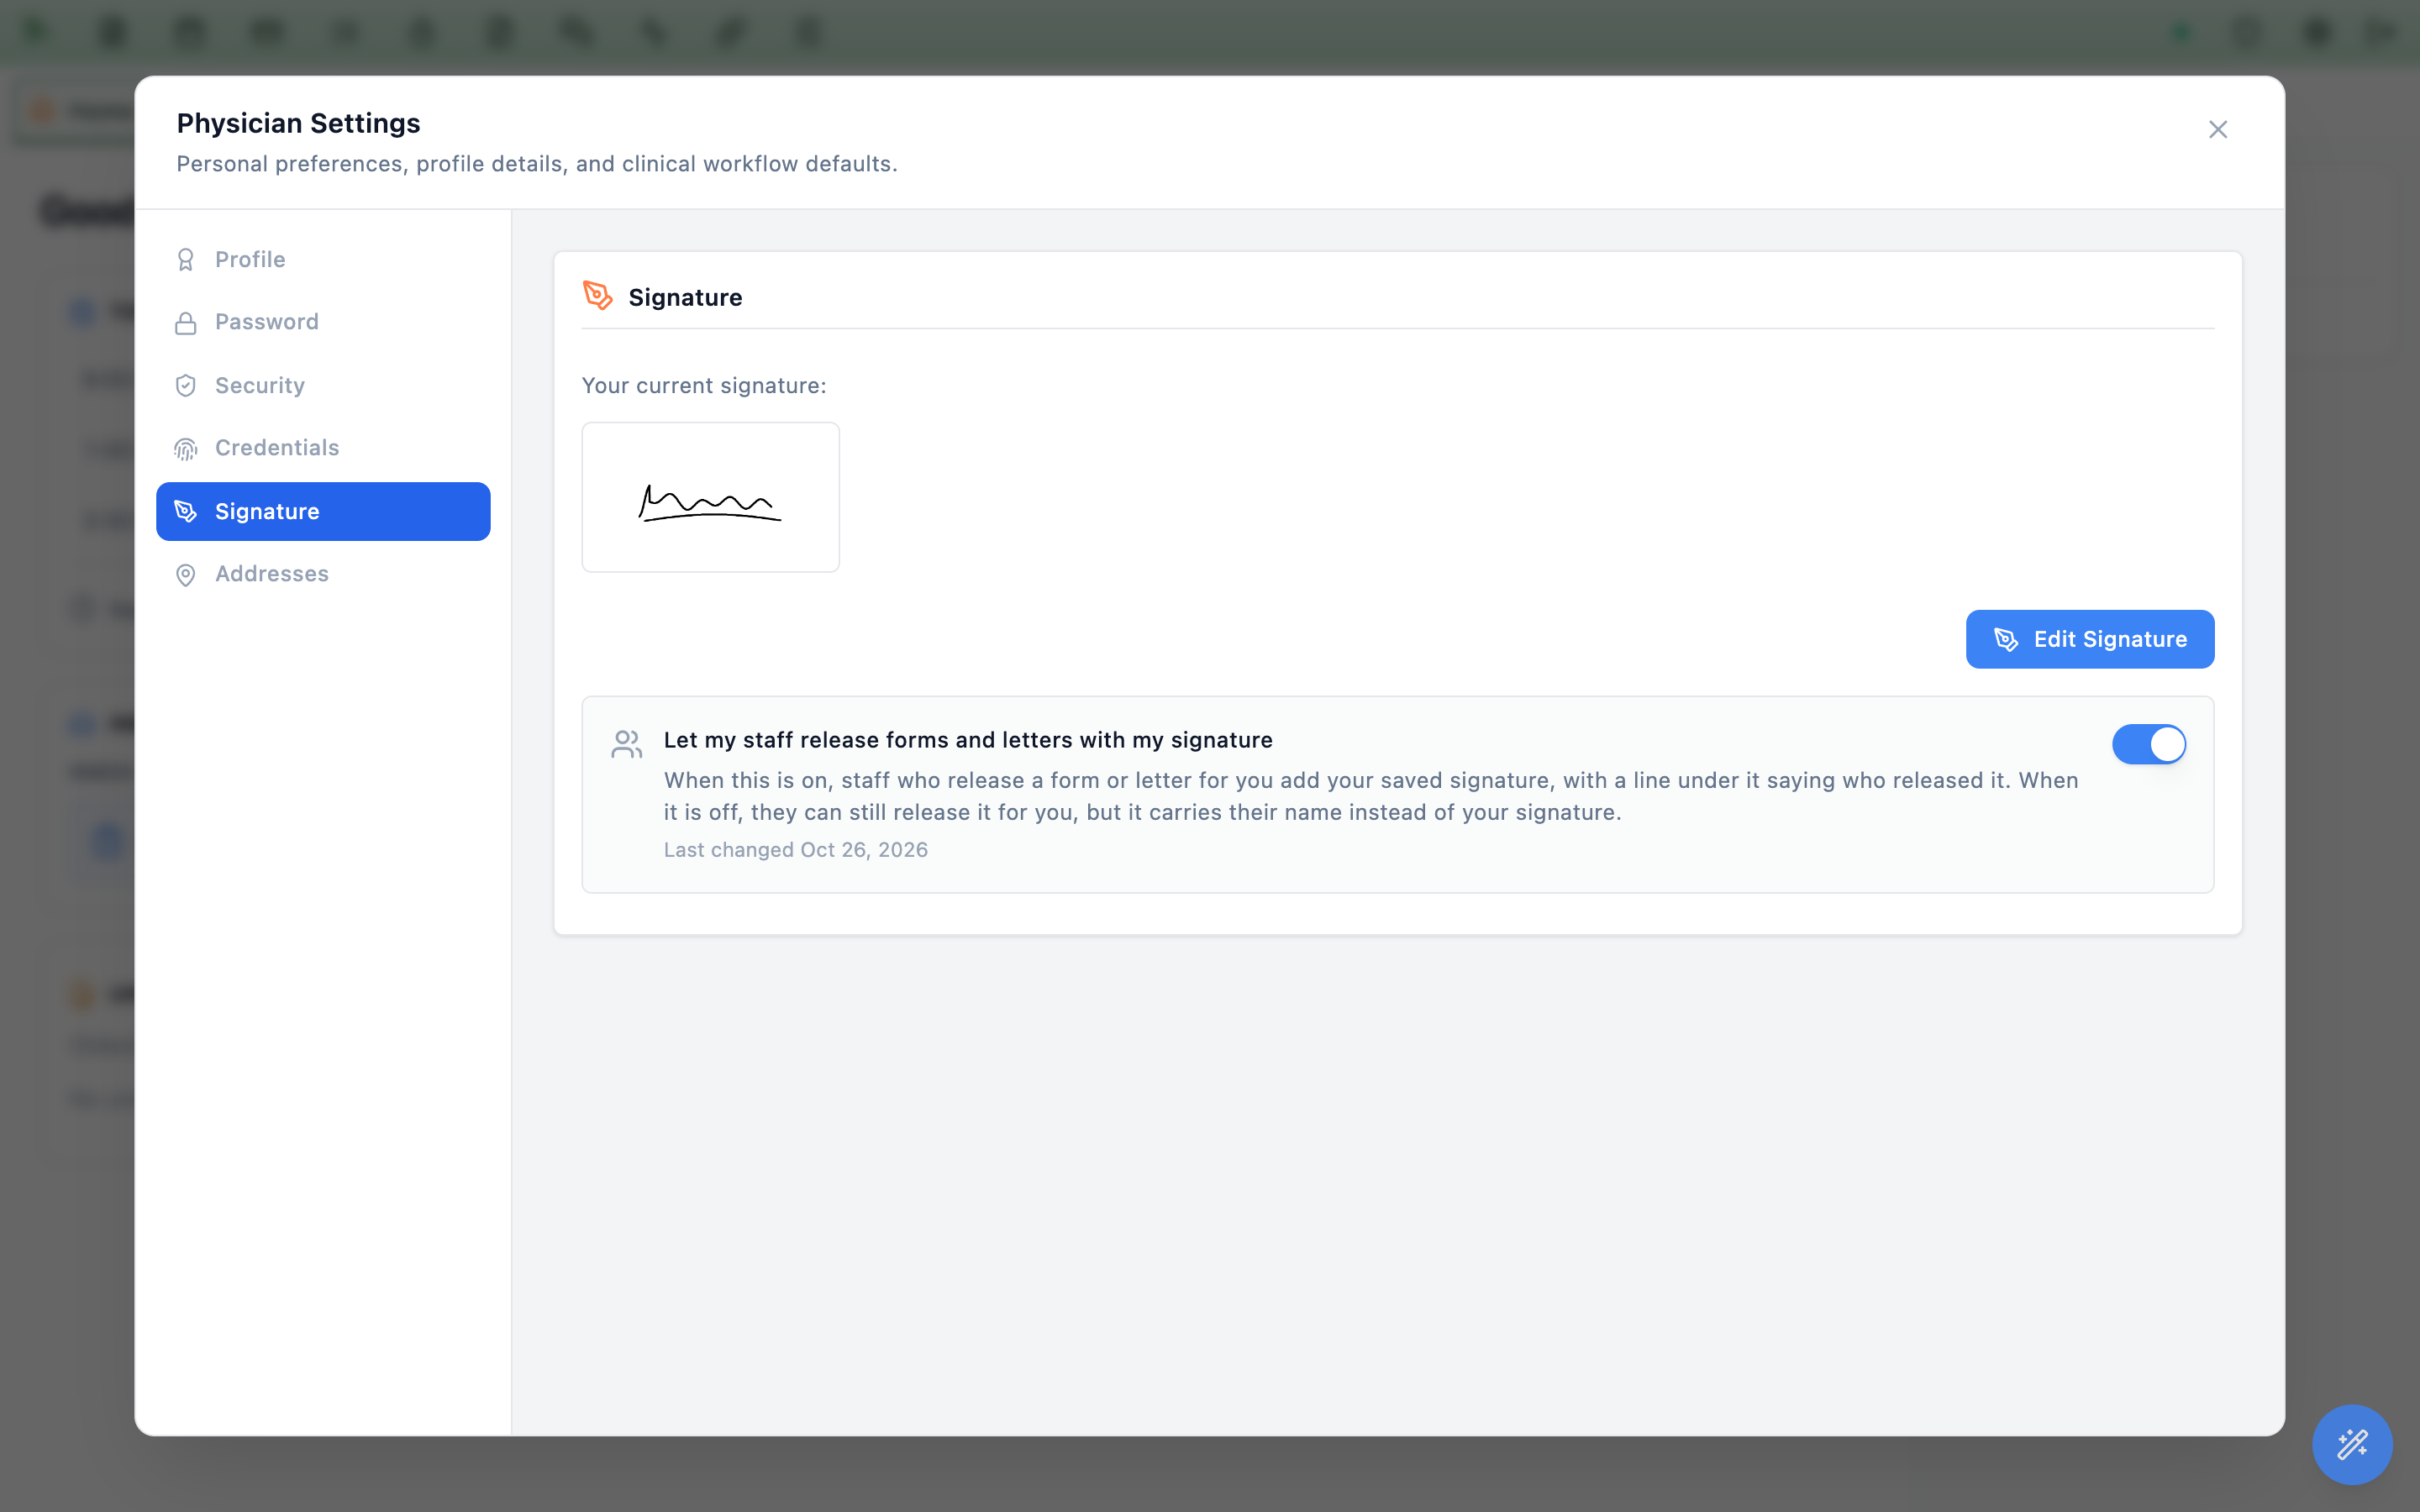
- Open your settings. Click
Settingsin the top bar, thenProfile Settings. ThePhysician Settingsdialog opens. - Open the
Signaturetab. Save a signature first ifNo signature has been saved.shows (Create Signature). - Turn on
Let my staff release forms and letters with my signature. It saves at once and showsLast changedwith the date. Turn it off the same way at any time.
On
“Staff who release a form or letter for you add your saved signature, with a line under it saying who released it.” Their Sign for card reads Uses Jane Romero, MD’s signature.
Off (the default)
“They can still release it for you, but it carries their name instead of your signature.” Their card reads Released with your name for Jane Romero, MD.
If the switch is on but you have no saved signature, it warns Save a signature above so staff can use it. and staff releases carry their name until you save one. If you turn it off while someone is approving, their release stops and they are asked to try again, so your signature is never used after you switched it off. Your own approvals always use your signature, whatever this switch says.
Fax a letter to the patient’s doctors, and follow every fax
Faxes under Care workflow appears when your practice has a fax service, for providers and for staff who can view patients. The top card, Fax a letter, lists the patient’s Care team with each doctor’s fax number (marked no fax when one is missing) and the six fax letters: pre-surgical clearance, cardiac clearance, medical records request, lab & test results, care coordination update and consultation report. A provider clicks one and it opens addressed to the right doctor, filled in with their usual choices and filed with the patient’s latest visit; staff see “A provider signs and faxes these letters. You can follow this patient’s faxes below.”
The lower card, Sent faxes, is “Everything faxed from this chart, newest first”: the subject, who it went to and the number, the page count, the time, the reason when a fax failed, and a status chip (Queued, Sending, Delivered, Failed or Cancelled) that updates while a fax is going out. Writing, signing and sending a fax letter are covered in Fax letters.
Track authorizations, approved units, and expiry dates
Prior Auth under Care workflow is where a payer’s approval gets recorded so it can be spent down and watched. The banner states the deal: “Track insurance prior authorizations for {first name}. Approved units are drawn down automatically as linked visits are completed and billed, and staff are alerted before each authorization expires.” Physicians and admins see the tab and may add and edit authorizations without any billing permission; other staff see it only with billing.prior_auth.manage (the Biller and Billing Manager role profiles include it, and they reach it from the Billing workspace’s Patient billing dialog without chart access). Grants are managed under Staff accounts & permissions.
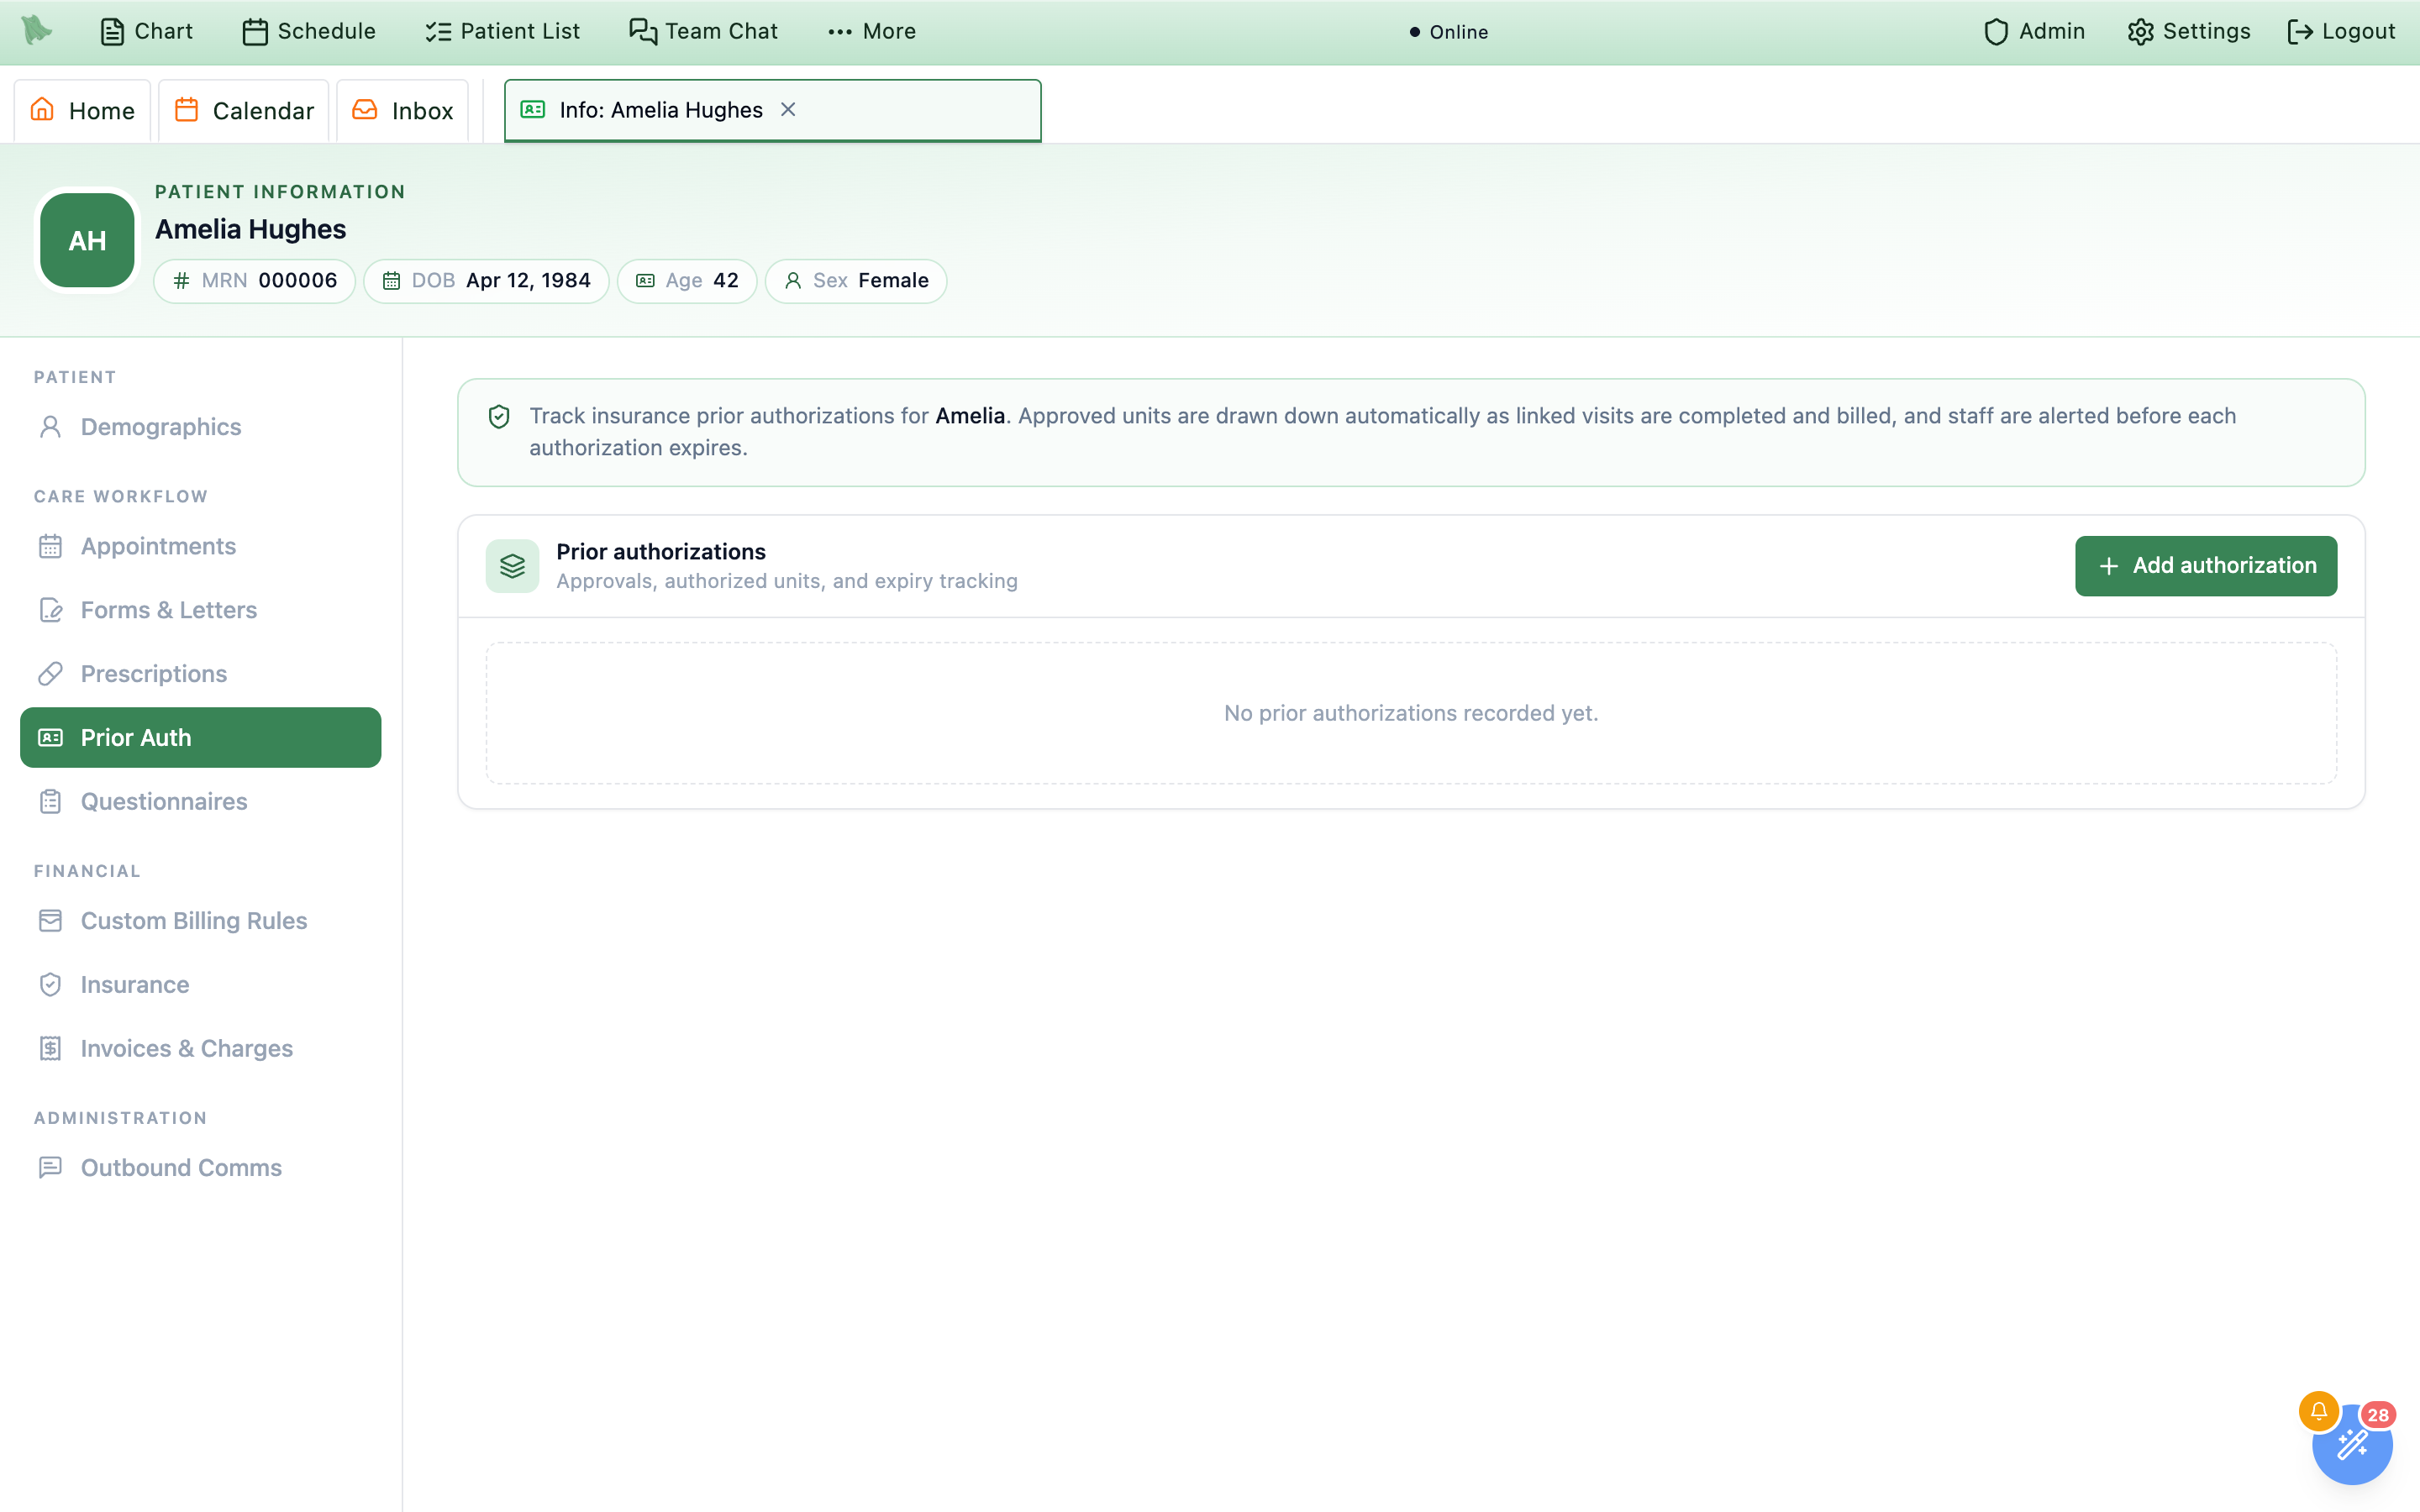
Add authorization is disabled until the patient has at least one insurance policy.-
Start from a policy.
An authorization always belongs to a specific insurance policy, so if the patient has none the card reads “Add an insurance policy on the Insurance tab before recording a prior authorization” and
Add authorizationis disabled with the tooltipAdd an insurance policy first. Add the coverage on Insurance first. -
Record the approval.
Add authorizationopensAdd prior authorization, subtitledFor {first name}.Insurance policyandAuthorization numberare required; everything else is optional. Save withAdd authorization. -
Read the card.
Each authorization is one row: the authorization number, its status pill, an expiry chip when one applies, then a muted line with the policy,
{n} units requested,Follow-up {date},Services:andDiagnoses:when codes are listed, the units, and the effective window. Free-textNotesappear underneath, andCheck visitslists which visits will get the number (see Prior auth letters & corrections). The pencil at the end of the row reopens the same dialog asEdit prior authorization, where the primary button becomesSave changes; the ban icon beside it isEntered in error. -
Let the units look after themselves.
In edit mode a read-only
Units usedbox appears, captioned “Tracked automatically as linked visits are completed and billed” — you set what the payer approved, Hero counts what has been spent. Units readUnits not trackedwhen you left the field blank, otherwise{used} of {authorized} used · {remaining} remaining.
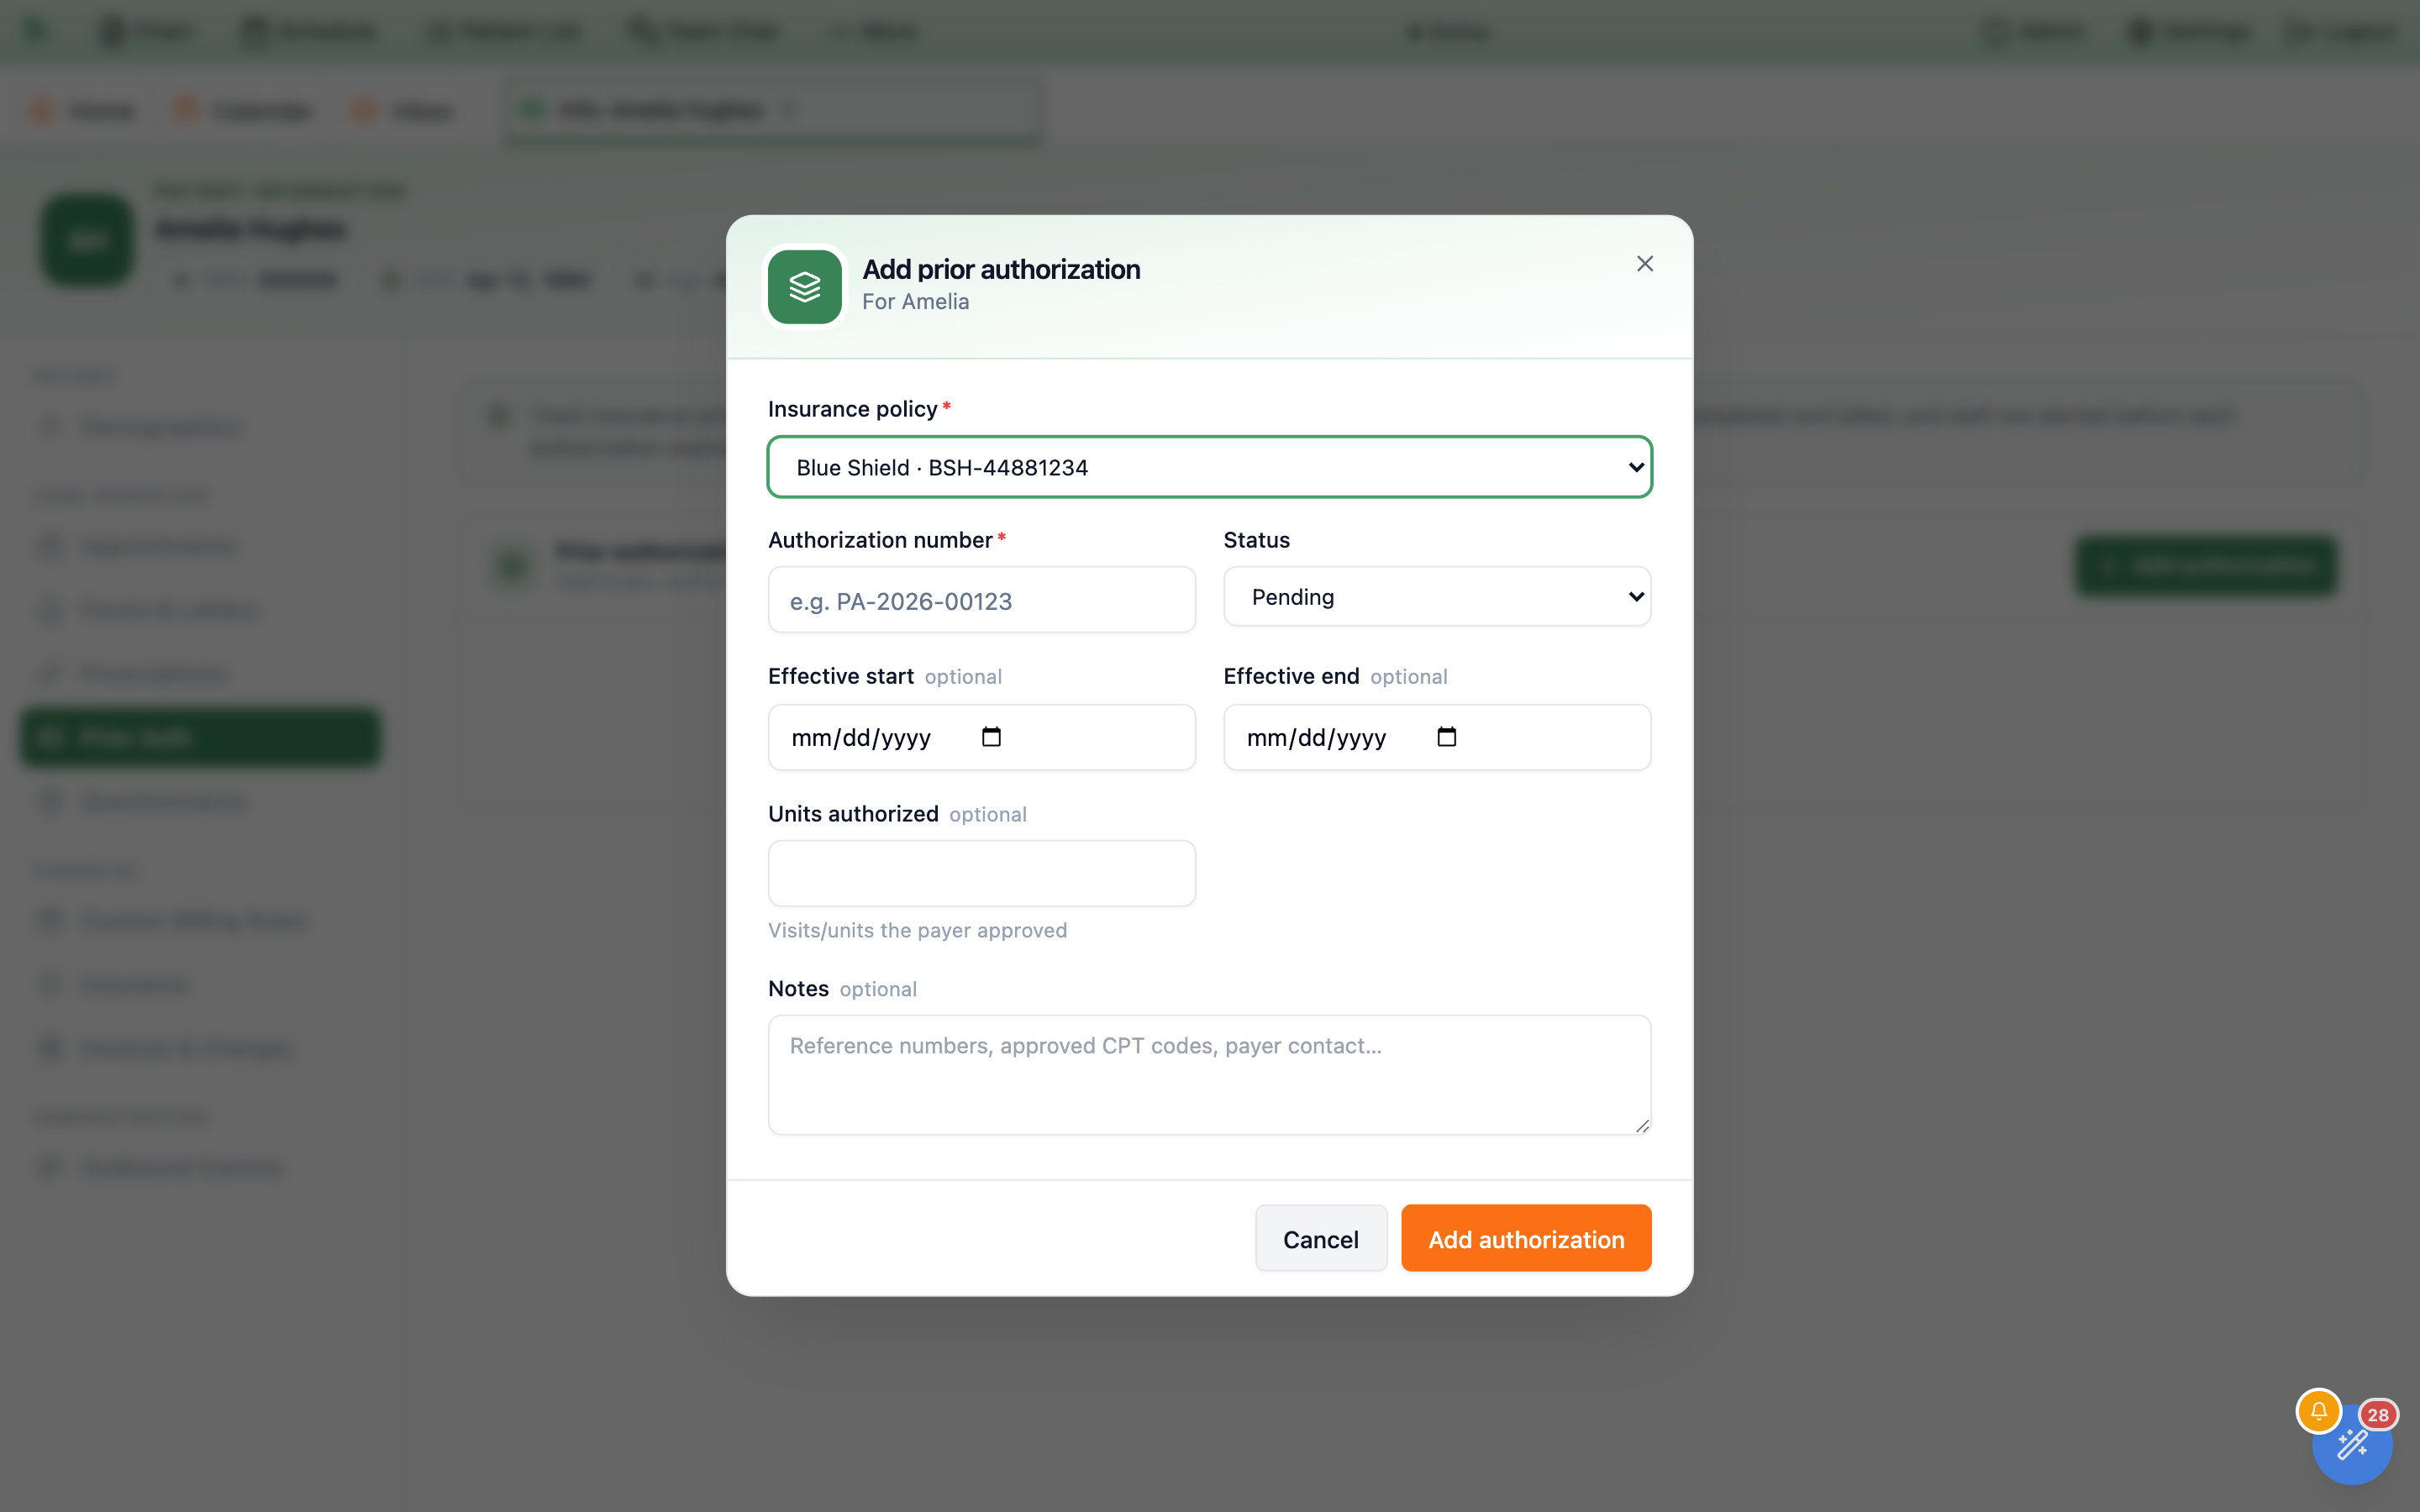
Status starts at Pending; the policy cannot be changed once the authorization is saved. (Since this picture the dialog also asks for Units requested, Follow-up date, Authorized CPT / HCPCS codes and Authorized diagnosis codes.)| Field | What to enter |
|---|---|
Insurance policy (required) | Opens on Select a policy… and lists the patient’s policies as {payer} · {policy number}. Locked when editing. |
Authorization number (required) | The payer’s reference, e.g. PA-2026-00123. It is sent on claims, so words such as N/A or pending are refused (see Numbers Hero refuses). |
Status | Pending, Approved, Denied, Fully used, or Expired. New authorizations start at Pending. An Expired authorization is still sent on claims for visits inside its effective dates. |
Effective start / Effective end | Optional dates; the end can’t be before the start. The end date is what drives the expiry chips. |
Units requested | Optional non-negative whole number. When fewer units are approved than requested, the form and the card show Partial approval. |
Units approved | Optional whole number — “Visits/units the payer approved”. Leave blank and units simply aren’t tracked. |
Follow-up date | Optional date for the next payer follow-up; it also appears in the practice-wide Prior Auths queue. |
Authorized CPT / HCPCS codes | Optional, comma-separated (placeholder Blank: any procedure): “Leave blank unless the payer approved only certain procedures. Only visits that bill one of these codes get this authorization number and use an approved unit. Leave it blank for a VA referral.” Leave it empty and any visit inside the dates on that policy qualifies. A VA referral approves an episode of care, and the codes printed on it are usually not the codes you bill, so typing them here keeps its number off the claims. |
Authorized diagnosis codes | Optional, comma-separated ICD-10 codes (placeholder M25.561), for reference only: “A visit coded with a different diagnosis still gets the number; its claim shows a warning.” |
Notes | Optional free text — “Payer contact and additional reference information…” |
Beside the status pill, a card can carry one expiry chip: Expired when the status says so, Past end date when the end date has gone by, Expires today, or Expires in {n}d within a fortnight of the end date. Beyond fourteen days — or with no end date at all — there is no chip. The chips are an at-a-glance advisory; the authoritative expiry sweep, and the staff alert that comes with it, runs on the server overnight.
The form refuses to save with a message in the dialog banner: Select the insurance policy this authorization belongs to., Authorization number is required., Units approved must be a whole number., Units requested must be a non-negative whole number., Enter valid five-character CPT/HCPCS codes and ICD-10 diagnosis codes, separated by commas., or Effective end must be on or after the start date. A rejection from the server shows its own wording, falling back to Could not save the authorization. Try again.
Entered in error, not a status. There is still no delete, but setting Status to Denied or Expired is not the way to take one back: an Expired authorization can still go on claims for visits inside its dates. The ban icon on the row marks it Entered in error with a reason, so its number is never sent on a claim; once a visit has used one of its units, edit it with the pencil instead. See Prior auth letters & corrections. The policy behind an authorization can never be changed, so one filed against the wrong coverage is marked entered in error and added again on the right policy.A card shows Partial approval when approved units are fewer than requested. To work all patients’ requests, pending decisions, partial approvals, and upcoming expirations, open Billing → Prior Auths.
Per-patient billing rules, the money already on the account, and superbills
Two sidebar items in the Financial group cover one patient’s money, and they are deliberately different jobs. Custom Billing Rules is settings — how this patient will be charged. Invoices & Charges is the ledger — what they have been charged. Neither appears for a plain physician. Custom Billing Rules needs an account that can see financial amounts plus either organization admin or the staff permission billing.settings.manage; Invoices & Charges needs financial amounts plus admin or one of billing.charges.manage, billing.ar.manage, or billing.sensitive (billing.payments.collect alone, as a medical assistant or nurse has, no longer shows it). Billing staff also open both from any patient name in the Billing workspace, in the Patient billing dialog. If either panel ever fails to render it says so in place — Custom billing rules could not be displayed. or Invoices & charges could not be displayed. — with a Retry button, leaving the rest of the workspace usable.
Custom Billing Rules
The whole tab is one draft: tick boxes and type rates, then press Save changes in the bar at the bottom. The bar reads All changes saved, or Unsaved changes with Discard and Save changes, and confirms “Billing rules saved.” Leaving the tab or closing the dialog with unsaved edits asks first. The Exceptions card holds three checkboxes:
Bypass insurance (treat as cash pay)— “Visit pricing and collection use the cash fee schedule instead of eligibility/copay rules, and encounter signing will not create insurance claim charges without an explicit override. Mirrors the Insurance tab control.” This is the one exception a staff account cannot touch withoutbilling.settings.manage; without it the box is disabled.Bypass card on file— “Card requirements will not block booking for this patient.”Bypass booking collection— “Booking-required collection moves to check-in for this patient.” The patient’s portal and billing view then read Deposit due at check-in instead of at booking.
Under Insurance claims, Automatically file secondary claims is on by default: when the primary insurance finishes a claim and leaves a patient balance, the remainder is filed to the patient’s active secondary policy instead of being billed to the patient. Uncheck it to bill this patient directly.
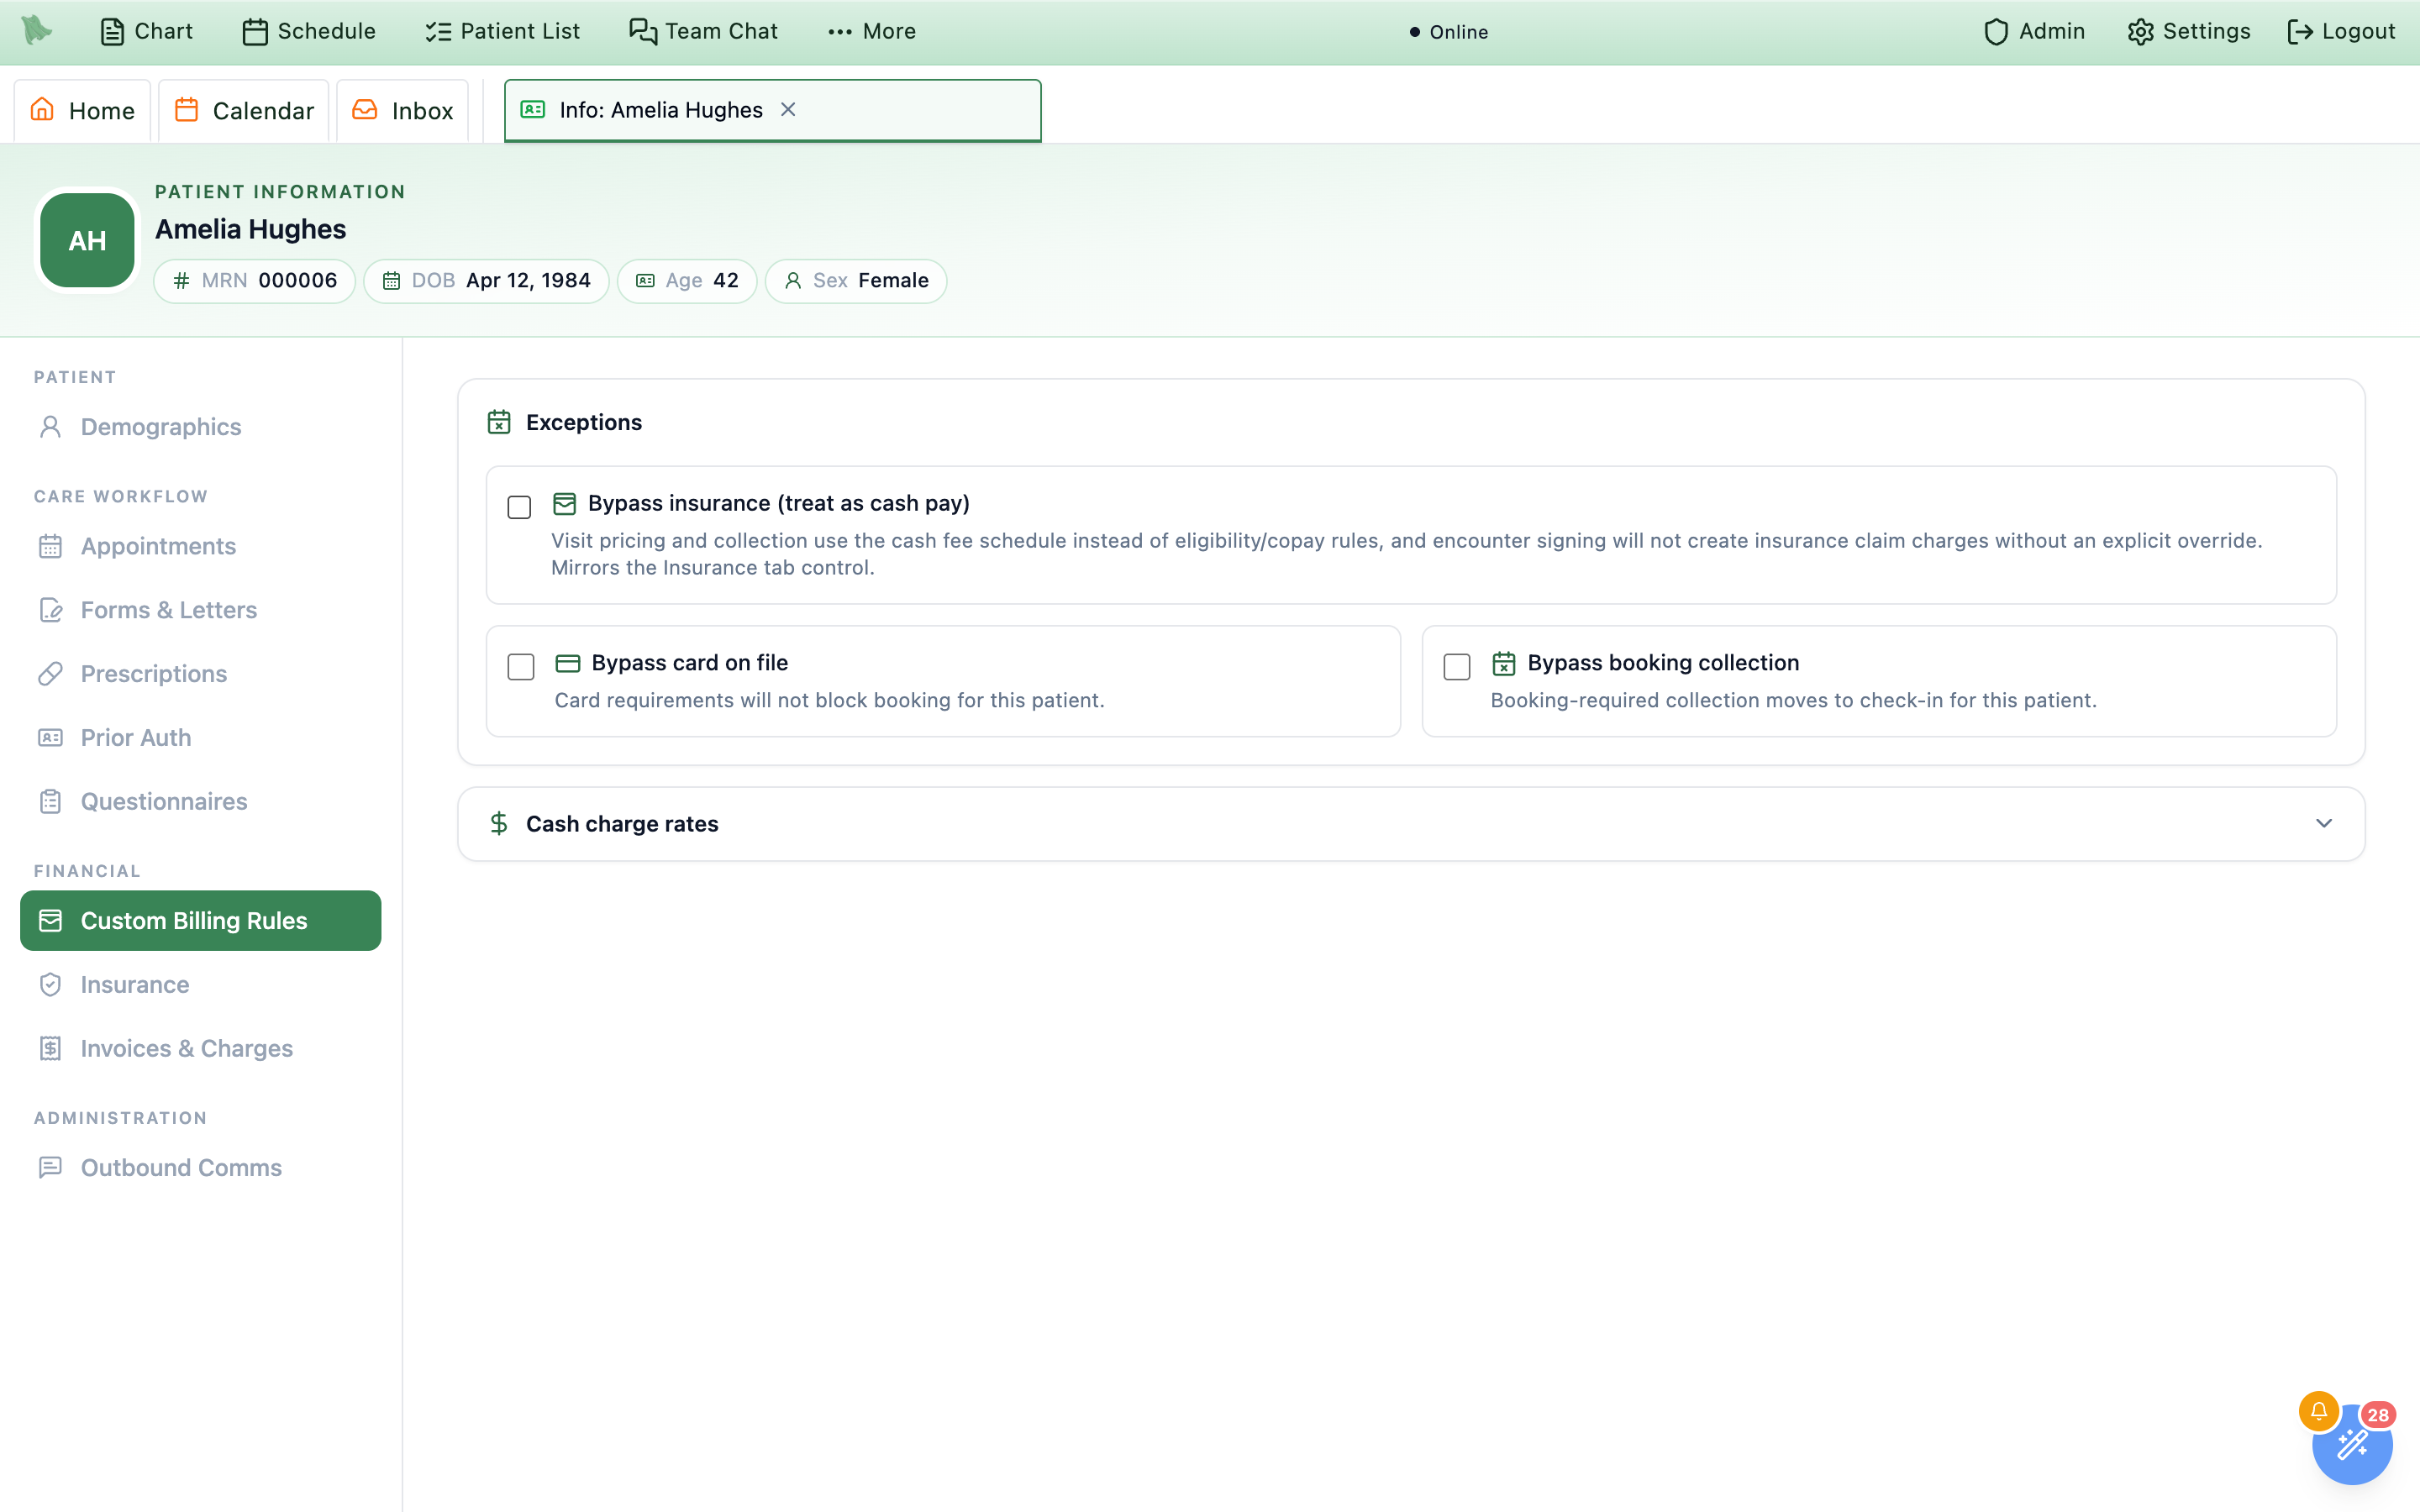
Cash charge rates collapsed. The rate table is not built until you open it.Below them, Cash charge rates is a collapsed accordion — click the button of that name to open the per-visit-type price overrides for this patient. Nothing inside it is loaded until you expand it, which keeps a long provider list from slowing the tab down; once opened it stays available even after you collapse it again. Inside: Search provider or visit type, which matches every word you type across both (a surname plus Standard finds that provider’s Standard visit; rows show the provider’s formal name, so a nickname won’t match), then a row per provider and visit type with Visit type (and its duration, e.g. 45 min / Online), Provider, the read-only Service rate your organization charges, and a Patient cash rate box prefixed with $ and placeheld Default. Type an amount to override; a rate that already has an override also gains a reset button, Use the service rate for {visit type}, which clears it in the draft. In a DPC practice, membership-covered services read Covered by membership as their service rate, with “Not used in DPC: this visit is covered by membership.” For a patient billed through insurance, a rate is charged only on a visit type set to Cash only; elsewhere a saved rate reads “Not charged: insurance bills this visit type for this patient. It applies when the visit type is Cash only.” Saving a rate re-prices the patient’s upcoming unpaid visits of that type, and today’s visit when the patient is already checked in and the note hasn’t been started (its unpaid check-in fee takes the new price, or is cancelled at 0). Set this patient's price on a cash-priced visit (in Take payment, or the visit’s Payment & charges) opens this accordion already expanded, searched to that visit type with the visit’s own row marked. Bad input is refused inline with Enter a valid amount. (and the bar reads Fix the highlighted rate before saving.). The fee schedule these overrides sit on top of, and the rest of the patient-exception model, are documented in Patient exceptions.
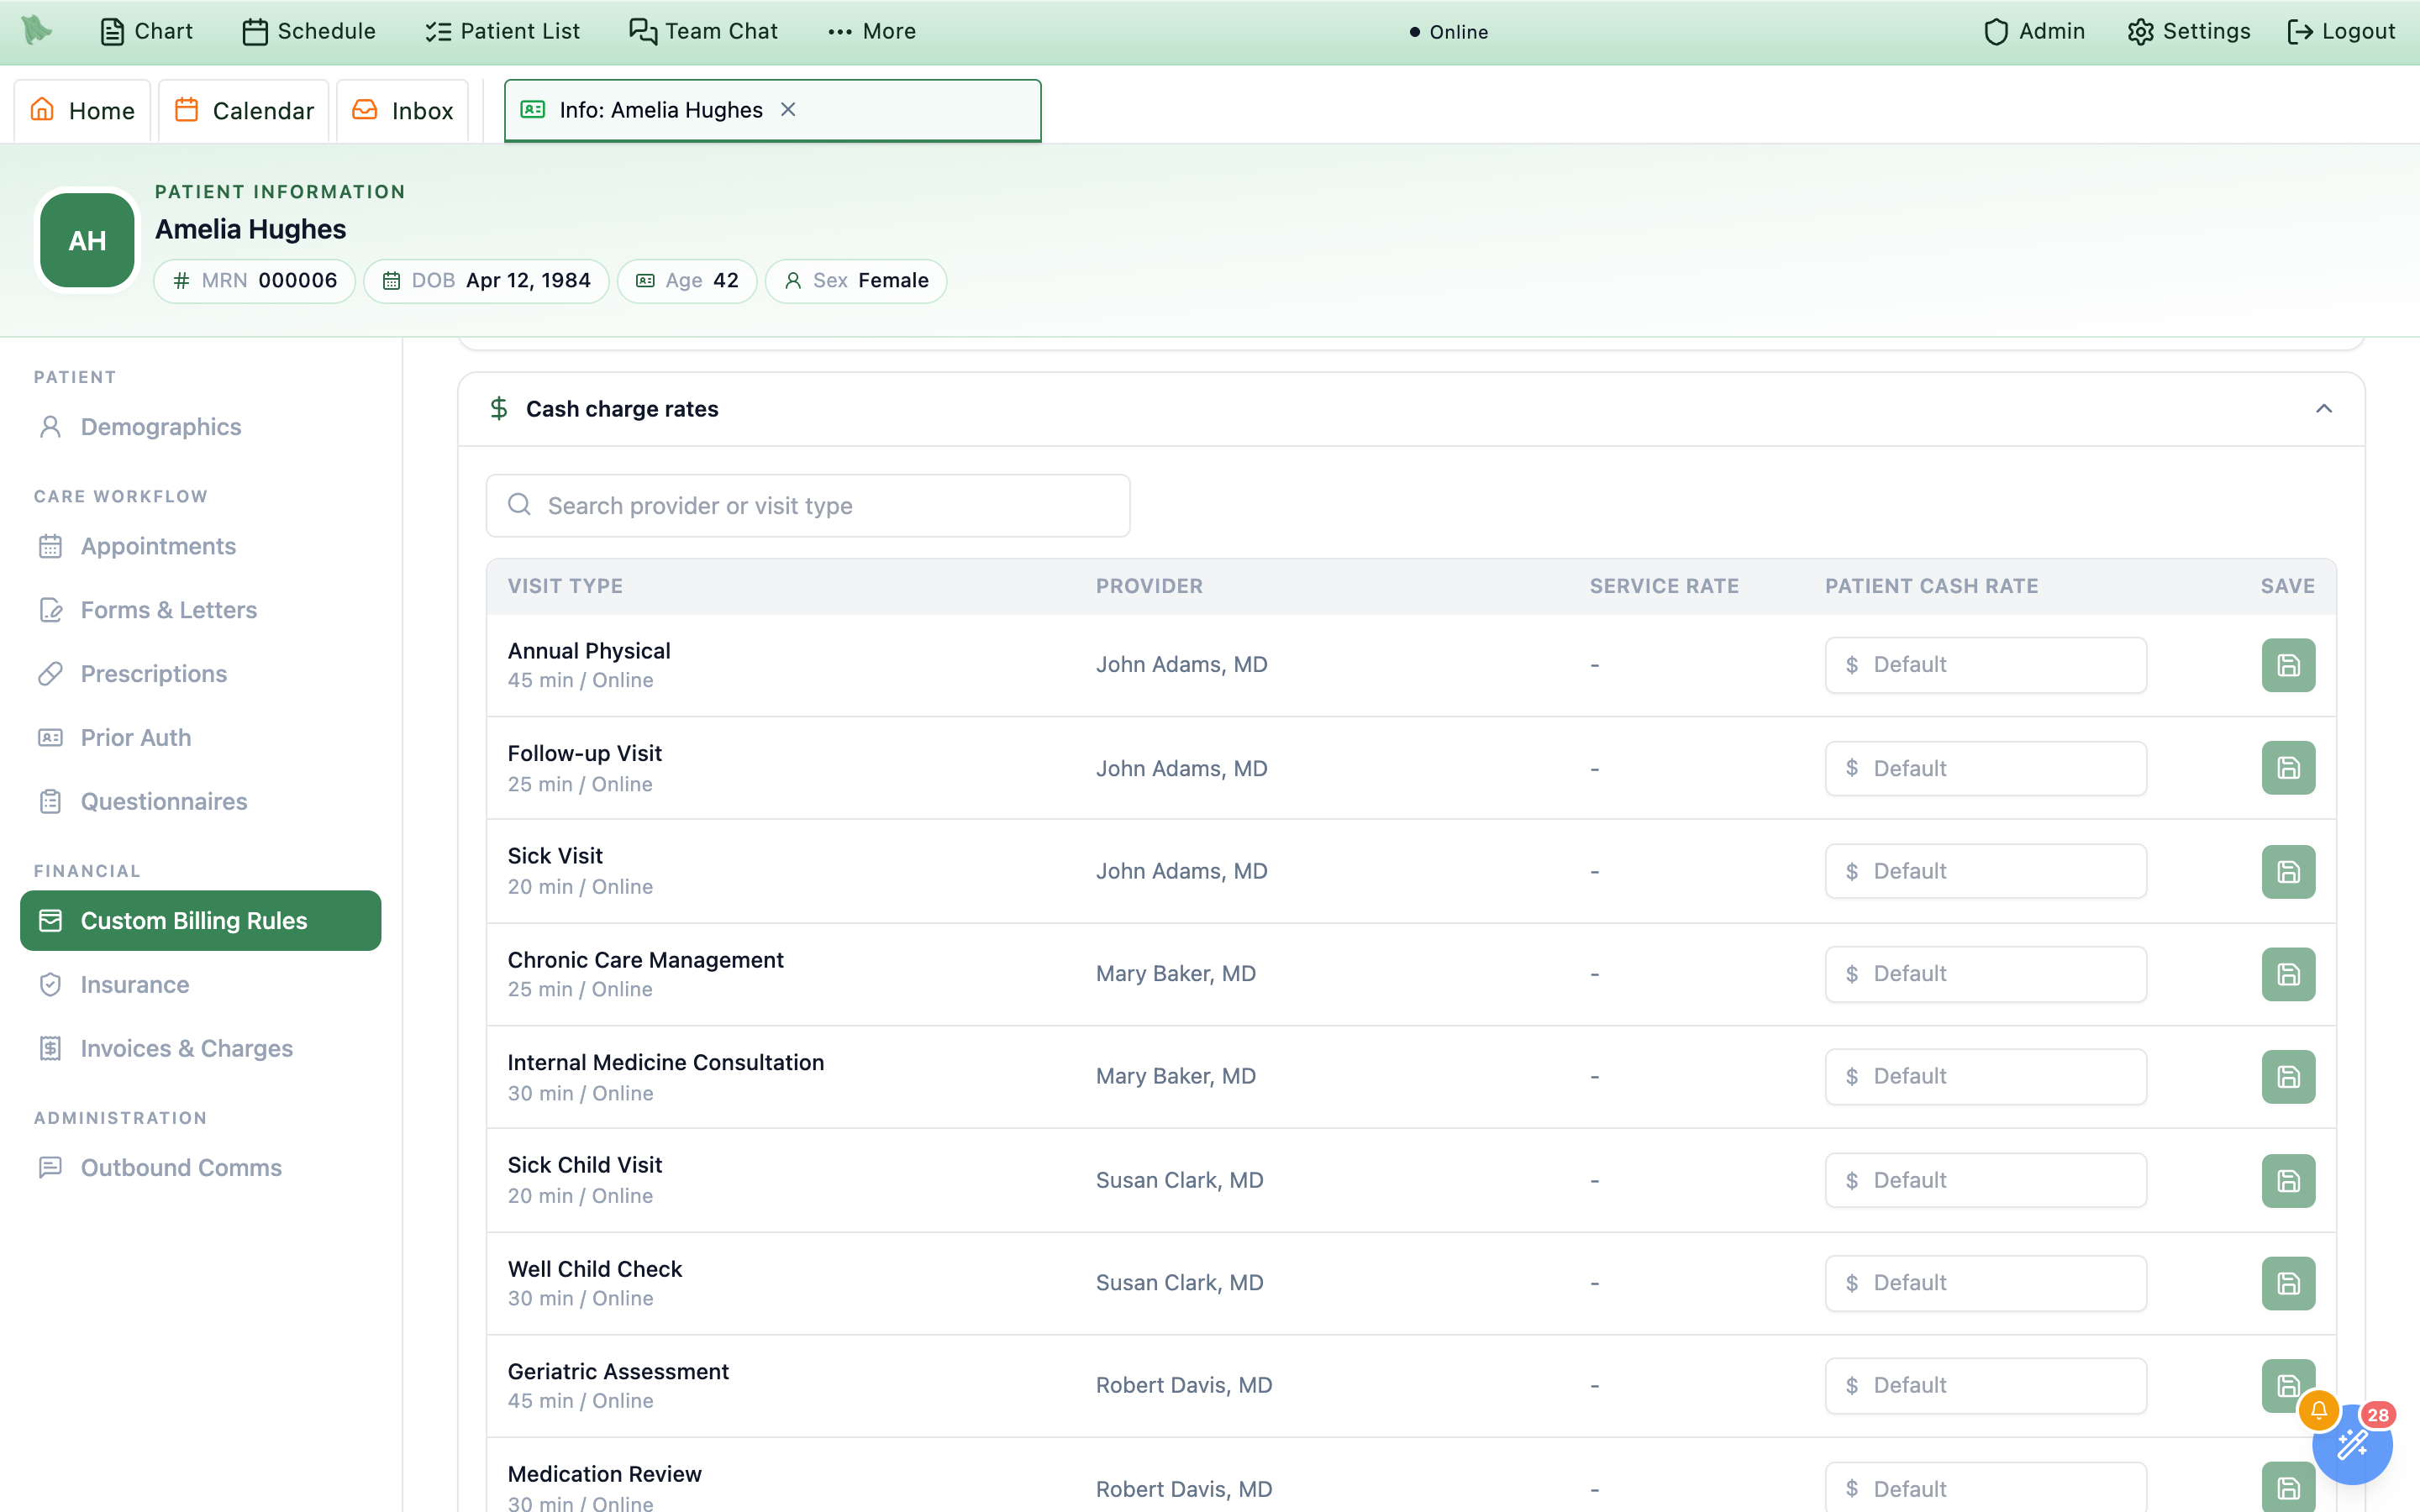
Save changes bar at the bottom of the tab.
Invoices & Charges
Four stacked blocks, all for one patient, in this order: Invoices, Patient portal billing view, Issue a charge or credit, and Issued charges & credits. Invoices comes first and is the same record the billing workspace uses: a left rail of invoices — open balances first, then those with insurance or in insurance review, then paid, then cancelled — and the detail opens on the first open invoice. Each carries a status pill (Balance due, Partially paid once the patient has paid part, Paid, With insurance, Insurance review, …), an optional Claim · {status} pill and a date, beside a detail pane carrying the reconciling tiles (Billed, Insurance paid, Paid/credits, Adjustments), the service lines, any Explanation of benefits, and an Insurance claim panel with its journey chips, Filed service lines, and Remittances (EOBs). Open in Claims Pipeline jumps to that claim — see the claims pipeline. An invoice still with the payer shows its invoice number and billed amount, its service lines, and a box that says where it stands instead of a balance: Awaiting {payer} — “The patient owes nothing until the payer decides.”; Claim being prepared — “Not sent to the payer yet — the claim is still being prepared.”; or Insurance review — “The payer’s answer needs billing review before the patient is billed.” An invoice whose patient share is held for a pending secondary claim reads Awaiting {payer} in amber, with “{payer} hasn’t processed this visit yet, so nothing is due until it does.”; it lists after the open balances and the detail doesn’t open on it. While that claim is pending no card can be charged for the share, but a cash or check payment the patient hands you can still be recorded; the hold ends when the secondary claim stops being pending (see Patient balances for the full rule). A patient invoice with a balance carries the payment actions for staff who collect payments: Collect card payment, Record cash/check payment, and Record external card payment — for a card your own terminal or a phone payment already took (“Hero records it and updates the balance; it doesn’t charge the card.”), reviewed on a Confirm external card payment step before Confirm and record payment; every payment dialog has Cancel. The same actions appear on the invoice in Patient AR and in Take payment. The invoice of a cancelled or no-show visit whose refund has completed reads Paid, with an Appointment balance released line for the unpaid balance the cancellation released, so it no longer shows as owed here or in Patient AR. A no-show or late-cancellation fee invoice carries Waive fee for admins and staff with billing.sensitive: the dialog (“Waive the no-show fee of $50.00…”) takes a reason, and anything already paid toward the fee stays paid. For balances and collections as a workflow rather than a record, use Patient balances.
Under the invoices, Patient portal billing view mirrors what the patient sees — “Patient-safe balances, saved-card readiness, and payment actions.” — with tiles for Patient balance, Available credit, and a count of Open charges, then membership, saved cards, and three columns: Portal-visible charges, Payment history, and Statements. Portal-visible charges read the way the patient sees them — Visit charge · Paid $25.00, or Visit charge · With insurance · nothing due yet — with no $0.00 rows and no cancelled or refunded charges, and their status uses the same words as the invoice that holds them: Balance due, Partially paid only when the patient paid part (a charge only the payer paid reads Balance due), With insurance. The rows under Issued charges & credits follow the same rule; credits, write-offs, and voids keep their own labels. A share held for a pending secondary claim reads $10.00 pending other insurance · Awaiting {payer} with “Nothing can be charged to a card until the secondary claim is processed. Cash and check payments can be recorded from the invoice above.”, the Patient balance tile adds + $10.00 pending other insurance, and Charge saved card doesn’t appear on it (nor on any charge with nothing payable).
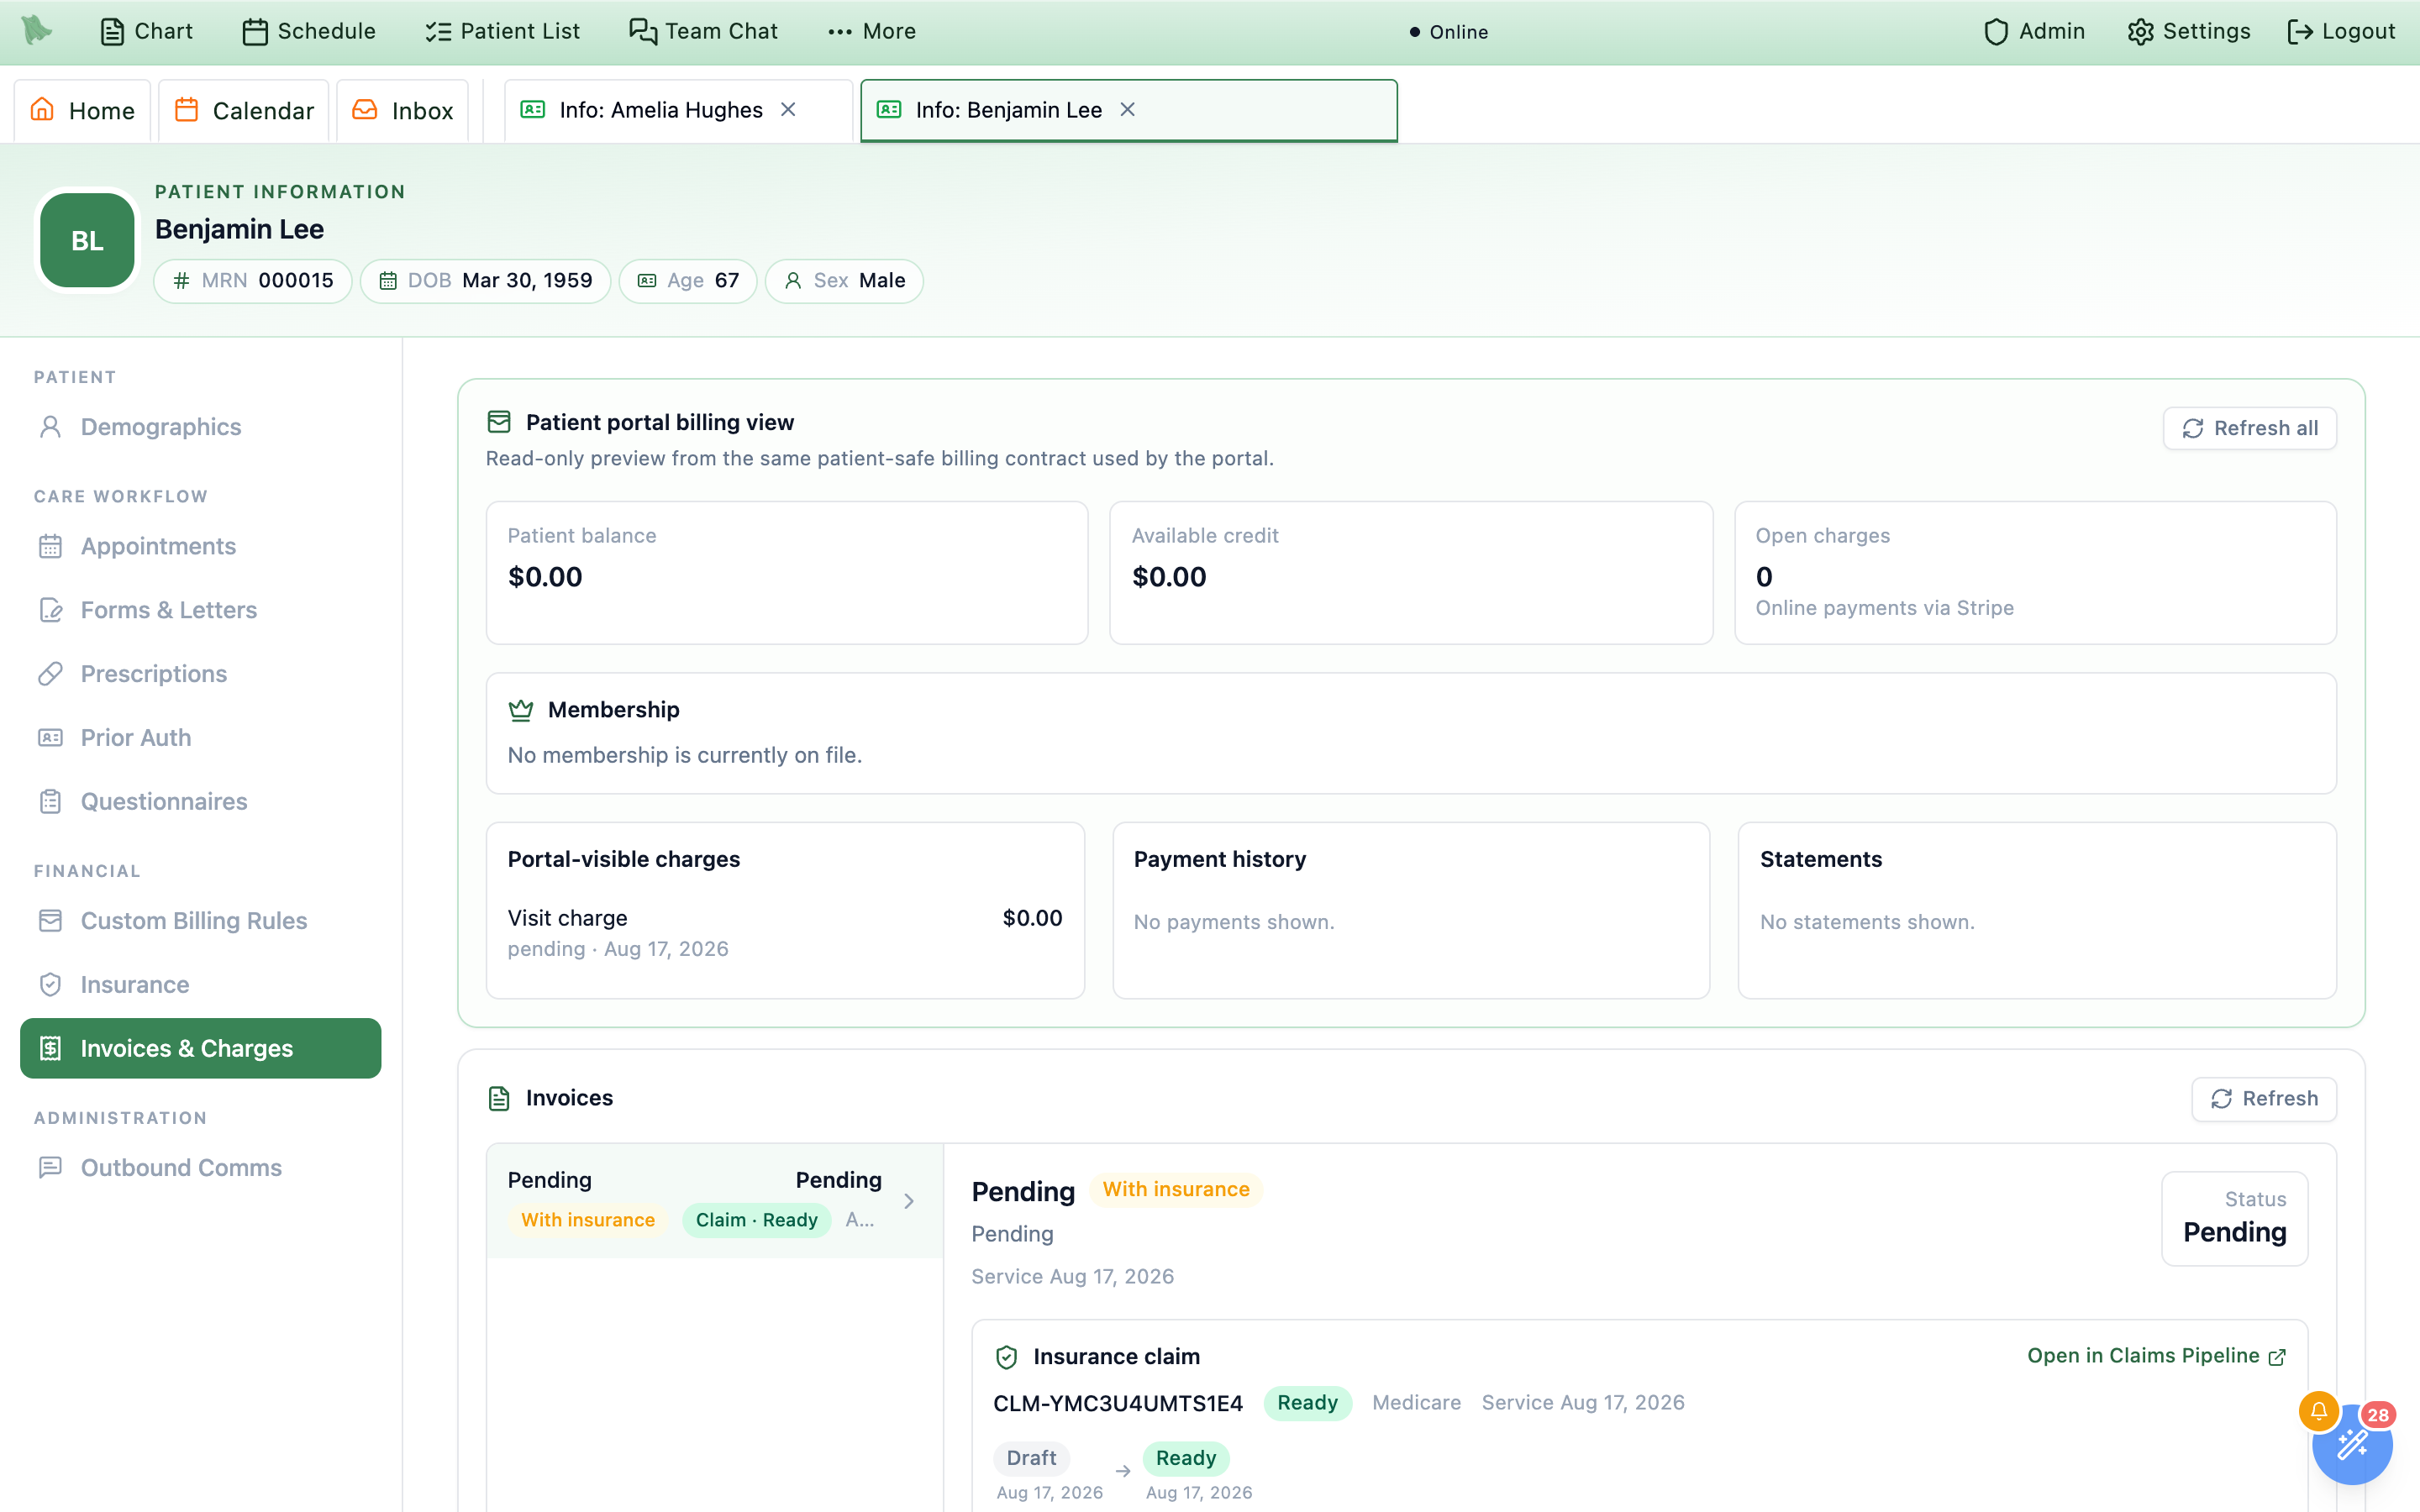
Financial documents: superbills, Good Faith Estimates, and receipts
Below the invoice list, Superbills, estimates, statements and receipts opens the patient’s document shelf. It is the same panel under a patient’s invoices in Patient AR. Everyone who can see the invoices can download from it; admins and staff with billing.charges.manage can also prepare documents and record delivery. Both documents open already filled in, so most need only a check and two clicks to issue. For a cash-pay, uninsured, or out-of-network visit, the same two documents are also one click from the visit’s Charges section.
- What fills in by itself. The provider is the visit’s physician, or the practice’s only physician; with more than one, a physician picker shows the choice and switching it changes the billing name and NPI. Support and system accounts are never offered. The provider’s NPI, tax ID, address, and phone come from Billing Identity, folded into one line;
Edit detailsopens them, and they open by themselves when something is missing. Each service is priced at your CPT List Prices price for that code, or, for a code without one, at your practice’s standard multiple of Medicare; a line under the services says which. Typing a new code fills in its name and price. Each line carries the visit’s diagnoses, at most 12 (the most one service line holds). - Prepare a superbill.
Prepare superbillopens the visit’s superbill with the invoice’s CPT/HCPCS lines. Before the visit has an invoice (opened fromCharges), it uses the codes and diagnoses already entered on the visit — “Filled in from the codes in this visit’s charges. If the codes change before signing, update them here too.” If the visit already has a superbill, the dialog shows it, withMake a correction. - Prepare a Good Faith Estimate.
Prepare Good Faith Estimatefills in the services expected: this visit’s codes, the codes set up for the patient’s next booked visit type, the codes billed most often for that visit type, the patient’s last visit, or your practice’s most billed service, in that order; a line under the services says which. Planned date is the next booked visit’s date (changing it changes every line); Requested on starts at today. “The patient is uninsured or not using insurance for this care.” is already ticked when Hero knows the patient pays out of pocket, with the reason (cash pay, no insurance on file, or out of network with their insurer); for an insured patient you tick it only when they chose not to use their insurance. Other providers or services scheduled separately starts as none; open it to list them. - Cash price or list prices. When the visit has a cash price — a fixed price on the visit type in the Service Menu, or this cash-pay visit’s price — the document opens at that price, and Price with shows both choices with their totals:
Cash priceandList prices(each service at your list price, or your standard multiple of Medicare). One click switches every line. TickRemember my choice for estimates(orfor superbills) and your next one opens on the same choice; untick it to go back to the cash price. The choice is saved for you, not for the whole practice. An invoice’s superbill always shows what was actually charged. - Preview, then issue.
Previewopens the document on screen — “Draft — nothing is saved until you issue it.” — withDownload draftandBack to editing. Anything still needed is listed under Before issuing, andIssue superbill…(Issue estimate…) waits until it is done. It then asks once: “Issue this superbill for $120.00? By issuing it you confirm you checked the provider, services, codes and amounts. It’s saved permanently in the patient’s record; a mistake is fixed by issuing a correction.” —BackorIssue superbill(Issue estimate). To correct an issued document, useCorrectnext to it in the list (orMake a correction); the earlier version is kept and marked Replaced by a later document. - Deliver it, then record delivery. After issuing,
Download PDForPrint, give or send it the way the patient asked, and record how with one click (Handed to patient today,Mailed today, orSent securely today). From the list,Record deliverytakes the method (Paper handed to patient, Postal mail, or Secure electronic delivery) and date; the list shows Delivery not yet recorded until you do. Issuing does not send an email or collect money; patients with billing portal access can download issued documents. For a Good Faith Estimate, deliver within 3 business days of a request, or sooner for care scheduled soon. - Download receipts and statements. The same panel lists payment receipts (
Download receipt), past statements (Download historical statement— older ones without a retained copy download as a labelled summary), andDownload current statement.
Manual charges and credits
Issue a charge or credit records an account adjustment. Staff need charge-management permission to issue charges and billing-adjustment permission for credits; administrators can do both. Pick Charge or Credit, enter Amount, choose Encounter, and enter a Reason for the patient’s statement. The default is Account charge (no clinical visit) or Account credit (no visit). The amount must be $0.01–$100,000.00 with no more than two decimal places. Review the confirmation before issuing.
For taxable account items, the practice can enable Charge sales tax; review the displayed rate, tax, and patient total. Visit fees are not taxed. See Sales tax. Eligible invoice charges can also receive self-pay discounts.
The Issued charges & credits history offers Void charge, Reverse credit, or Reverse write-off when the entry and your permissions allow it. Enter a correction reason; the original history is retained. A paid taxable item can instead offer Cancel charge — item returned: this reverses its tax and turns money already paid into account credit unless already refunded. Returning money to a card is a separate refund.
When enabled for the practice, Send add-card link lets authorized staff send the patient a secure portal link to save a card. The result reports delivery or its failure reason; sending the link does not collect payment.
Every reminder, receipt, and message this patient has been sent
Outbound Comms is the only item in the Administration group and the answer to “did we tell them?” The heading reads Outbound communications over “A record of reminders, confirmations, receipts and messages sent to {first name}. This is an audit view — two-way conversations live in the inbox.” It is for organization admins and staff holding admin.outbound_comms.view; a plain physician never sees the item, on the server as well as in the sidebar. Sending from here needs the further admin.outbound_comms.manage grant. Verification and login codes are deliberately excluded from the log. Ongoing conversations belong in patient threads, and bulk outreach to a list of patients in campaign messaging.
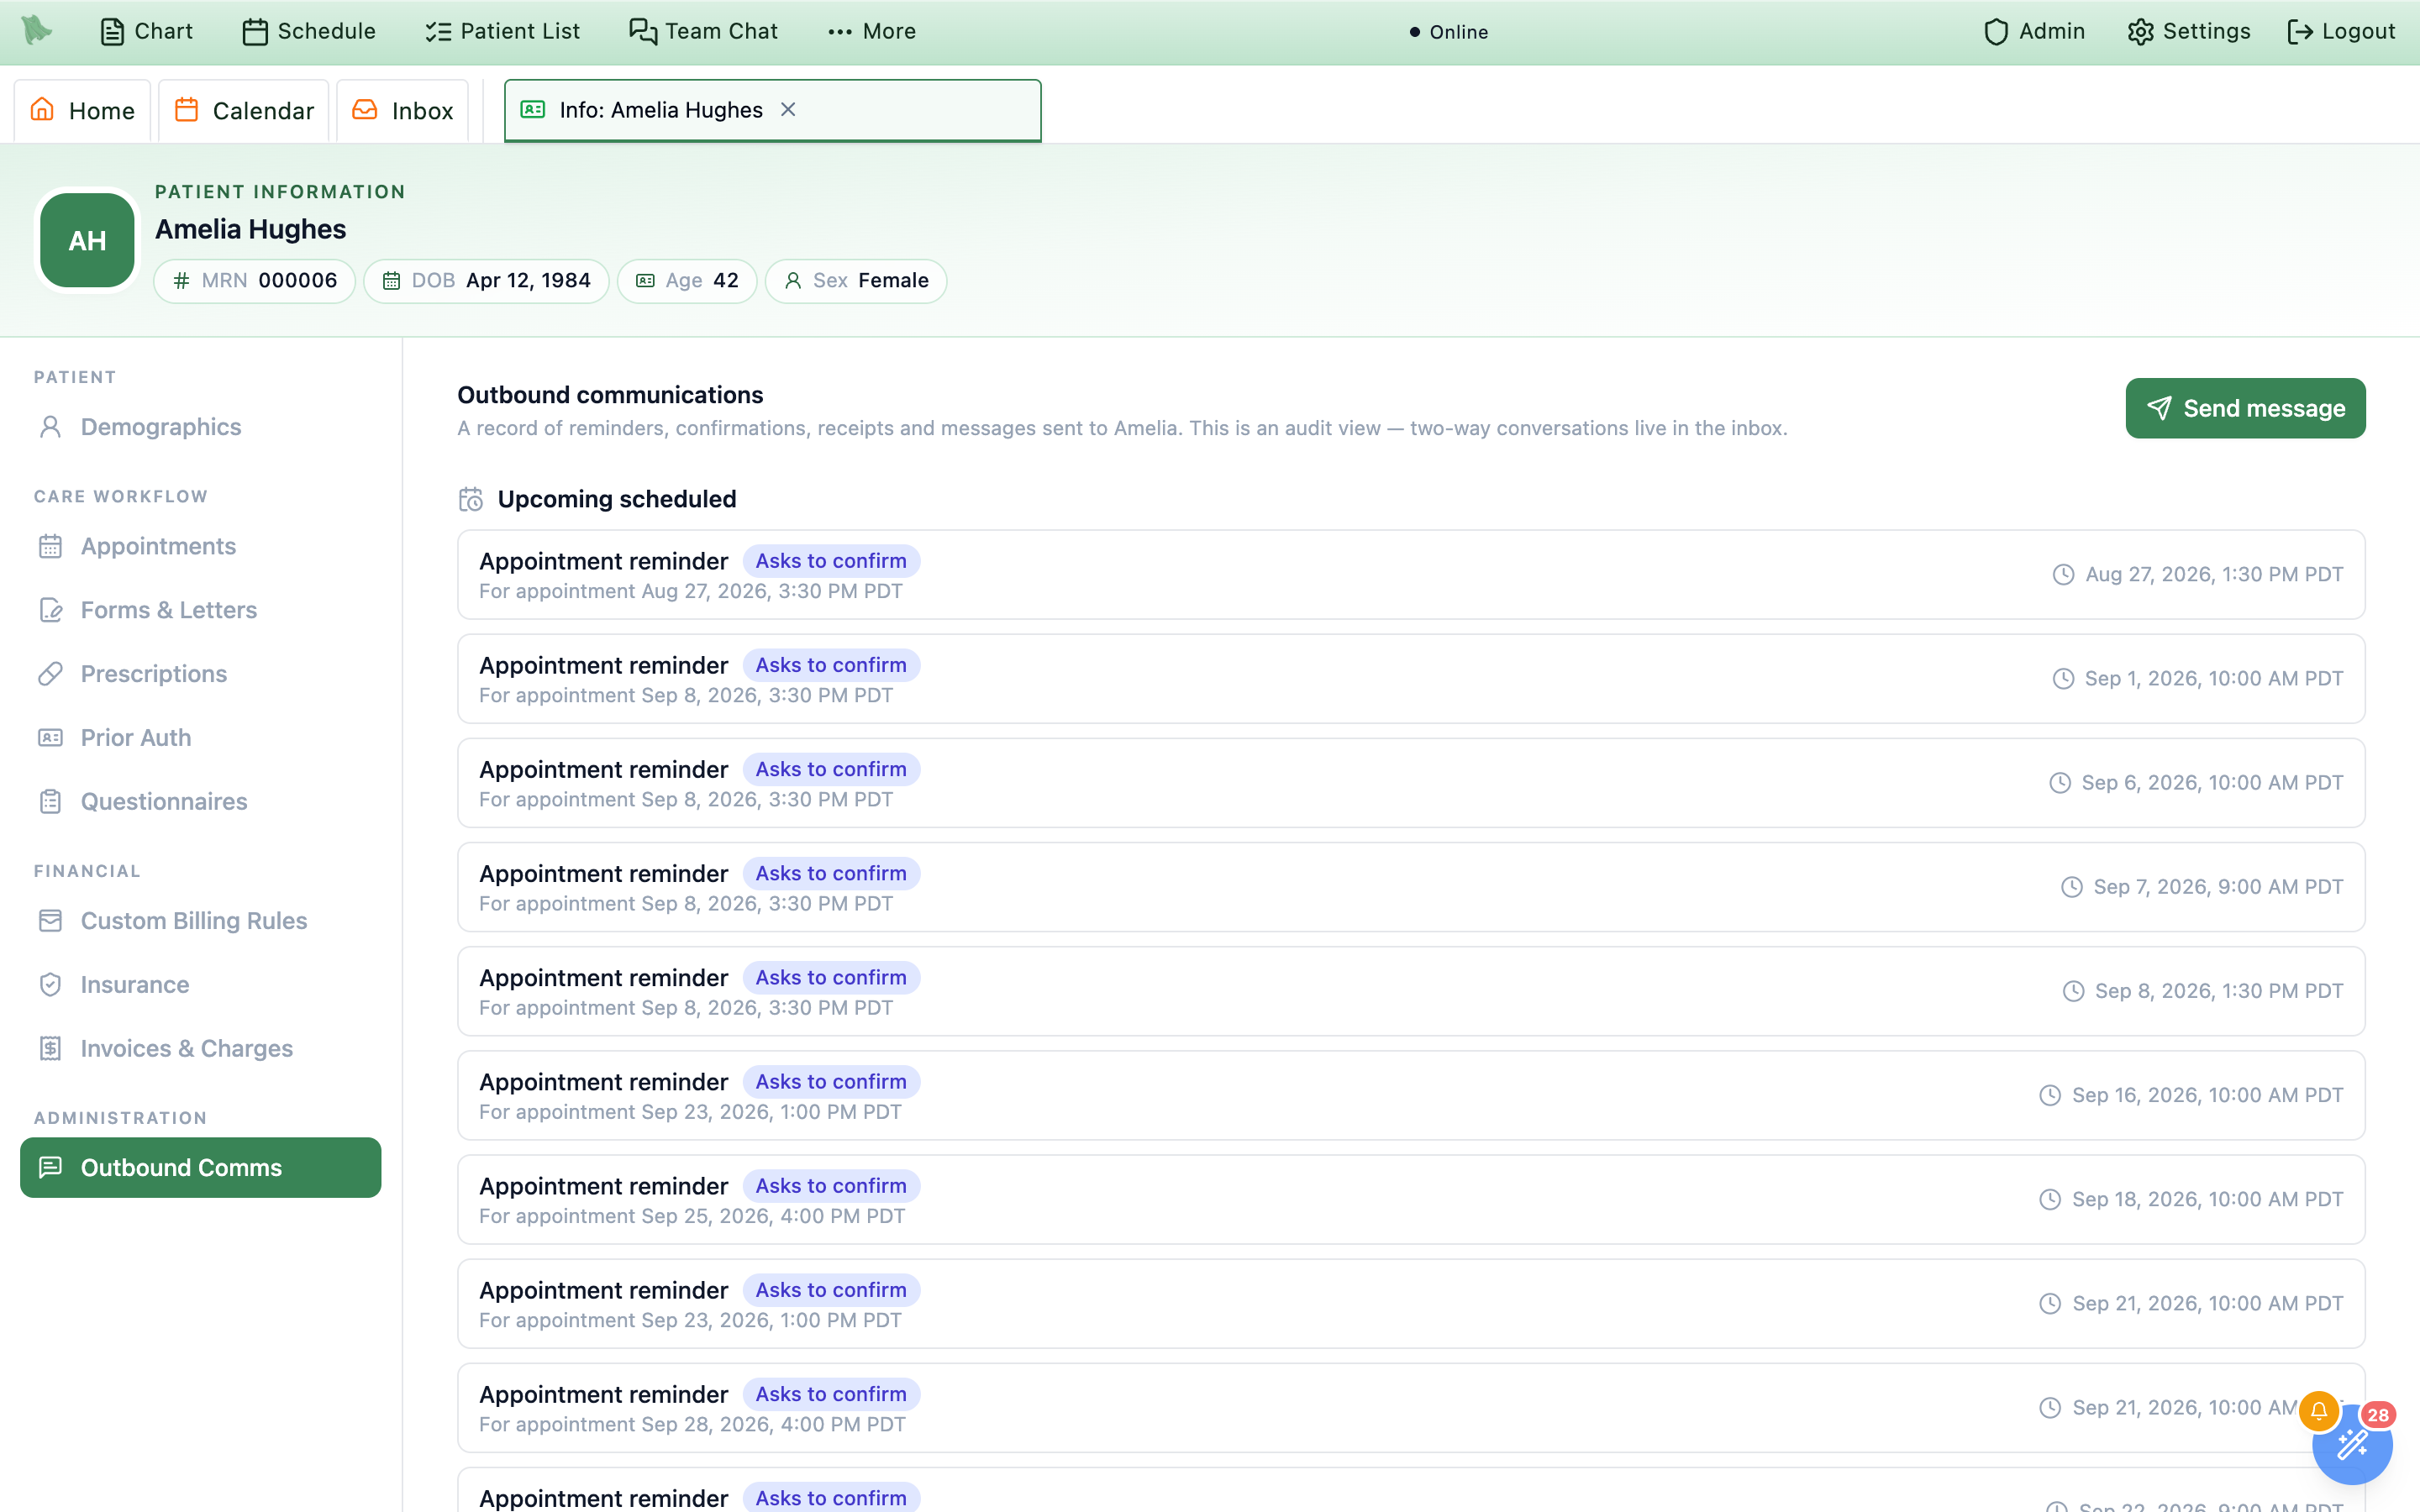
Upcoming scheduled lists what is already queued, with the projected send time on the right.-
Check what is still coming.
Upcoming scheduledlists the messages already queued for this patient: the message type, an indigoAsks to confirmpill when a reply is expected, aFor appointment {date, time}line when one is attached, and the projected send time. Empty it readsNo reminders are scheduled to go out.These are real queued sends — cadence-only projections are not shown, so this is a floor, not a forecast. Which reminders exist at all is configured under Patient notifications. -
Read the history.
Sent historycarries the total in parentheses. Each row shows the channel (SMS,EMAIL, and so on), the message type, a violetManualpill when a person sent it by hand, the subject on email, and a two-line preview of the body. The bottom line is the send time — always with its time-zone abbreviation, e.g.Aug 26, 2026, 12:33 PM PDT— plus· {n} segmentson SMS. -
Interpret the pills.
On the right of each row: a delivery pill reading
delivered,sent,pending,failed, orbounced, and beneath it, on messages that asked for a reply, a response pill readingConfirmed,Declined,Awaiting reply, orNo response. Afailedrow also prints the carrier’s reason in red —Invalid destination number, for instance. -
Send a one-off message.
Send messageopensSend a one-off message, subtitledTo {first name}. ChooseChannel—EmailorSMS— add an optionalSubjecton email, and write theMessage, capped at 2,000 characters with a live{n}/2000counter. The closing note reads “This is a one-way message. If the patient replies, their response lands in the inbox.” ThenSend.
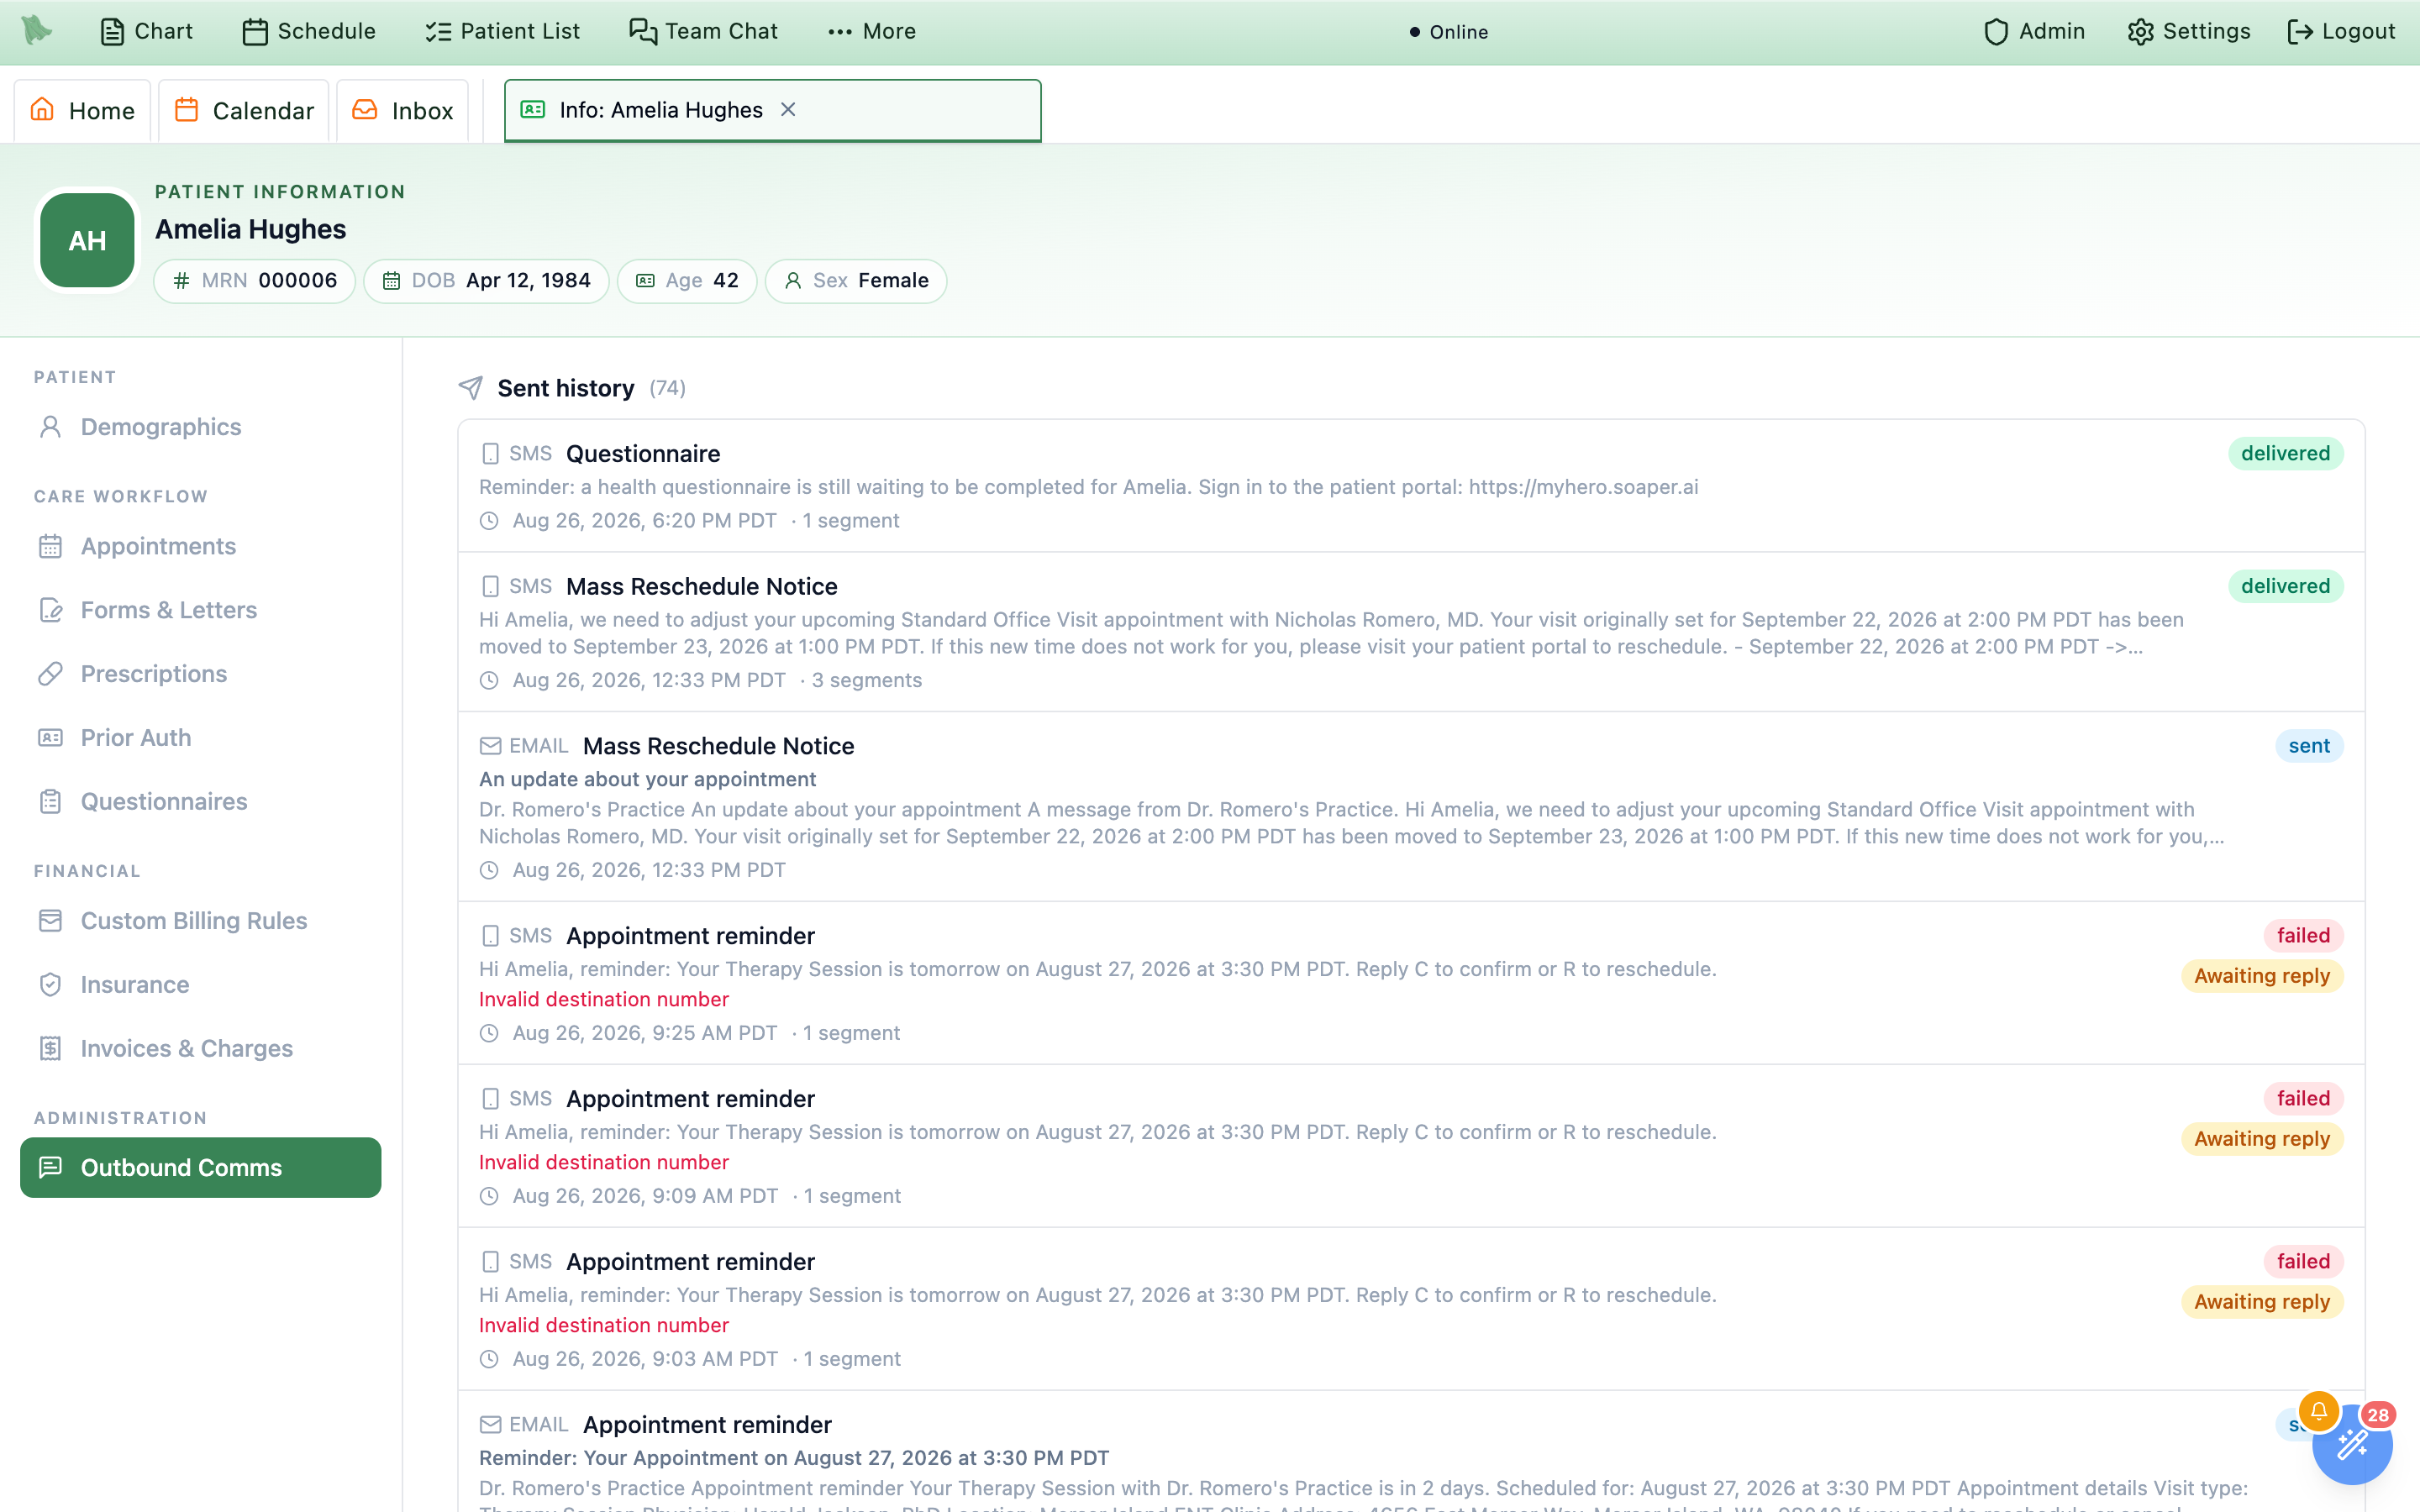
Some patient states stop outreach. When they do, a banner sits above both sections quoting the reason — “This patient is discharged from the practice; automated communications are suppressed”, for example — and spells out the consequence: reminders, follow-up prompts, questionnaires, surveys, campaigns, balance reminders, and statements will not be sent, and either “A message you send manually from here (or from the secure inbox) is still delivered” or “Manual messages are also blocked”. A deceased patient falls in the second group and Send message is disabled outright. Setting the patient back to Active resumes everything. Where a suppression is in force, Upcoming scheduled replaces its list with a count of the reminders that will be skipped.
SMS changes the placeholder to a reminder that long texts bill as multiple segments.Send dispatches immediately — and it can cost money. There is no queue, no draft, and no way to recall a message from this tab; the row simply appears in Sent history. SMS is billed per segment, which is why the SMS placeholder reads “Keep it short — long texts are billed as multiple segments” and each sent row prints its segment count. The opt-out warnings — This patient has opted out of SMS. The message will not be delivered. and No phone number on file for this patient. — warn but do not block: the button stays enabled and the failed attempt is still recorded.See or change how a patient wants to be contacted (texts, email, calls, opt-outs)
A patient’s communication preferences (whether they get text messages, which emails, app notifications and automated phone calls, the order to try them, and quiet hours) are shown under Communication preferences in the patient’s Outbound Comms tab. Patients set them in the portal or by replying STOP to a text. When a patient asks you by phone or in person to stop texts or change their email settings, staff can change them here, if the practice allows it.
Read the preferences
Each row shows on or off, with who last changed it and when: the patient, or a staff member by name with how the patient asked. The rows are Text messages, Email: care team messages, Email: reminders and scheduling, Email: payment reminders, App notifications and Phone calls, then Try first (the order Hero tries to reach the patient in), Quiet hours (non-urgent messages wait until they end) and the Patient's time zone. A warning shows when the patient reported a practice email as spam or email to their address bounced.
Let staff change them
A practice administrator opens Admin → Scheduling → Patient Notifications, the Patient Preferences tab, switches on Staff can edit communication preferences, and clicks Save. It is off by default; while it is off the preferences are read-only for everyone.
Change them on the patient’s request
- Open the patient’s
Outbound Commstab and clickChange preferences. You need permission to edit patient demographics; without it the section says it is read-only for you. - Switch channels on or off, reorder
Try first, and setQuiet hours start,Quiet hours endand the time zone as the patient asked. - When you turn texts off, choose how far. No reminders or alerts by text works like the portal switch: notices that an appointment was booked, changed or cancelled still go by text, and staff can turn texts back on later. Stop all texts is a STOP: no texts of any kind, and only the patient can turn texts back on, by replying START or in the portal.
- Record the request. Choose how the patient asked (
Phone call,In person,Secure messageorOther) and tick the box confirming the patient asked for these changes. They are recorded with your name and the time. - Click
Save.
Eligibility history, a separate eligibility payer, and Medicare payers
These parts of the Insurance tab help you see every check Hero ran on a policy, point eligibility checks at the right payer, and pick the right Original Medicare payer.
Every eligibility check of a policy
Open a policy’s View benefits detail. Below the latest result, Eligibility checks (N) opens the full history: “Every check of this policy, newest first, including Billing Hero’s checks of proposed details.” It shows 25 at a time (Show more) and refreshes when a newer result lands.
- Who asked: the staff member’s name (for example {name}, from Pre-visit), an automatic check (Automatic check before the visit, Automatic check when the policy was added, Automatic check after the policy was changed, Urgent care check-in…), or Billing Hero (Billing Hero, approved by {name} when a person approved it).
- The result:
Active coverage,Coverage inactive,Member not found,Name or birth date didn't match,Payer didn't confirm,Setup problem,Payer error,Couldn't check,Skipped, orWaiting for the payer. - The details: when it ran (your practice’s time), which payer was asked, the date of service, the last four digits of the member ID, the clearinghouse, and whether the check was billed.
Billing Hero sometimes asks the payer about details it wants to propose (for example a corrected member ID) before anyone changes the policy. Those rows say so: “Billing Hero asked the payer about proposed details … This check did not change the policy or its eligibility status.” A negative answer there is shown in amber, not red. Billing Hero also adds such a row when it works a claim held or turned back over its member ID or group number: it checks the policy as it is and reads the member ID and group number the payer has for the member (see Member ID and group number). COB checks are not in this list.
Check eligibility with another payer
Some medical groups take the claims while the patient’s health plan answers eligibility. For those patients, keep the medical group as the policy’s payer and tell Hero where to check eligibility:
- Open the section. In the add-policy form or
Edit policy, openAdvanced: check eligibility with another payer. It opens by itself when the chosen payer can’t answer eligibility checks, or when one is already set. - Pick the health plan. Search
Check eligibility with (optional): “Pick the health plan here; claims still go to the payer above.” Pick it from the list; a payer that doesn’t answer electronic eligibility checks is refused. - Save. Saving re-checks eligibility. The policy card then shows Eligibility checked with: {payer} ID {id} under its Files to: line.
It changes only who answers this policy’s eligibility checks: claims and COB checks still go to the policy’s payer. To stop, tick Stop using it: check eligibility with the claims payer again in Edit policy. Patients can’t set it from the portal.
Original Medicare payers and Medicare IDs
- Your practice’s Medicare payer comes first. When your practice has set its
Default Medicare payer(see Medicare claims), payer searches for Original Medicare list it first, markedYour practice's Medicare payer. - A warning when you pick another one. Choosing a different Original Medicare payer shows “Your practice bills Original Medicare through {payer}. Claims and eligibility checks for Original Medicare go to the contractor where your practice sees patients, not where the patient lives.” with
Use {payer} instead. Keep the other one only if your practice really bills this patient’s care there. Medicare Advantage, supplement and railroad plans are never flagged. - Medicare ID format. For an Original Medicare payer, the member ID must be the 11-character Medicare ID: “Medicare ID must have 11 letters and numbers in the format 1EG4-TE5-MK73. Check the Medicare card; B, I, L, O, S and Z are not used.” Dashes and spaces are removed for you. Medicare Advantage, supplement and other private Medicare plans keep the member ID printed on their own card.
- Part B decides Original Medicare coverage. When the payer says only Part A is active, the policy shows
Inactive coverage: Part A alone doesn’t cover office visits.
When the insurer didn’t check that date
Some insurers only answer checks dated close to today. Instead of a red failure, the card shows a blue notice, The insurer didn’t check that date, explaining that this isn’t a problem with the member ID and that Hero re-checks with today’s date. Hero retries once with today’s date and then re-checks such policies once a day while the patient has an upcoming insured visit. These answers never block a booking or hold a claim.
Card photos
Photos of the insurance card, whether scanned by staff, uploaded by the patient in the portal, or brought in from another system, show on the policy card as Card front and Card back thumbnails; click one to see it full size. Staff without access to insurance billing details don’t see them.
Benefit checks: record a payer call, or have Hero call the payer
A benefit check keeps what the insurance company told you on the phone (coverage for a procedure such as a surgery, copay, deductible, prior authorization, and the call reference number) on the patient’s Insurance tab, with the policy. You can type in the result of a call you made, or send a Hero call request (Have Hero call · Beta) so Hero phones the payer and fills in the answers for you.
Turn it on
- Open
Billing → Configuration → Eligibilityand find theBenefit checks by phonecard. A practice administrator or staff allowed to manage billing settings can change it. It is off by default. - Switch on
Benefit checks by phone. This adds theBenefit checkslist to every policy. Turning it off later hides the list but keeps the checks already saved. - Optional: switch on
Hero AI calls (Beta, free while in beta). Staff can then ask Hero to call the payer’s toll-free line during business hours. Hero says it is an automated assistant calling for your practice. If Hero can’t place payer calls for your practice yet, the card says why, and staff can still type in results. - Pick
Who gets calls Hero couldn't finish. These people get an item in their Inbox, listing what is still missing, so they can call the payer themselves. The person who asked always gets it too. Only staff who can see insurance amounts are listed.
Record the result of a call you made
- Open the patient’s
Insurancetab and clickView benefits detailon the policy.Benefit checksis below the eligibility checks. - Click
Add call result. It appears only on an active policy. - Fill in what the payer said. Under
The call:Called at(practice time),Rep nameandCall reference #. UnderThe visit: the visit orDate of service, place and surgeon. UnderCoverage:Plan name,In network,Deductible left ($),Out-of-pocket left ($)and similar amounts. UnderProcedures, one row perCPT codewithPrior auth needed,Auth reference,Copay ($),Plan pays (%)andNotes for this code. Leave anything the payer didn’t say blank. - Click
Save result. The check appears in the list. To correct it later, clickEditon the check andSave changes.
Ask Hero to call the payer (Hero call request)
- Click
Have Hero call · Betain the policy’sBenefit checks. The button shows only on an active policy, when Hero AI calls are on and Hero can place calls for your practice. - Say what to ask about.
Procedure codes (CPT), separated by commas or spaces (for example 55708, 52000), and, if the payer asks for them,Diagnosis codes. - Describe the surgery. Choose an upcoming
Visit(it fills in theDate of surgery, place and surgeon), or enter them yourself:Place of surgery,Place of serviceandSurgeon. - Pick the
Payer phone number. Choose one from the list orType a number. Hero can only call toll-free numbers (800, 833, 844, 855, 866, 877 or 888). Add anything else Hero should ask underAnything else to ask. - Click
Ask Hero to call. Hero calls during business hours. The check showsQueued, thenCalling, and the list updates on its own. While the check is queued or calling,Cancel call(when shown) stops it; you can ask again later.
When the call ends, the check reads Done, Partly done or Couldn't finish, and the person who asked gets an item in Inbox → Notifications (Benefit check done, Benefit check partly done or Benefit check needs a call) that opens the patient’s Insurance tab. A partly done or unfinished check also goes to the people chosen in the settings, with what is still needed.
Get back an insurance card photo that was replaced or overwritten
When a new card scan replaces the photos on a policy, the old front and back photos aren’t deleted. They move to Previous card photos on that policy in the Insurance tab, where you can see them and restore them, for example when a printout or the wrong card was scanned over the real one.
- Open the list. On the policy card, press
Previous card photos (n). Each entry shows the photos with when and by whom they were replaced, in practice time: Replaced by a card scan on Oct 30, 2026, 4:12 PM by {name}, or Replaced when earlier photos were restored …. - Restore. Press
Restore these photos(orRestore this photowhen only one side was replaced). Confirm “Put these photos back on the policy? The photos it shows now move to Previous card photos.” withRestore.
- Nothing is lost by restoring: the photos the policy showed until now become previous photos, and can be restored in turn.
- When you attach a new scan to an existing policy, the review step says what happens first: choosing
Replace the card photosreads “The front and back photos on the policy now move to Previous card photos, where they can be restored.” A scan with no back photo keeps the policy’s back photo. - The list shows only to people who can see card photos (administrators and staff with insurance billing access).
Restorealso needs permission to edit the patient or their insurance (patient-management or claims permission). - Deleted photos, and photos the policy shows again, aren’t listed. The button doesn’t appear on a policy with no previous photos.
Read authorization letters, take back a mistake, and see which visits get the number
These additions to the Prior Auth tab save typing, keep wrong numbers off claims, and show which visits an authorization will be sent on.
Read the payer’s letter instead of typing it
Letter reading starts off. A practice administrator, or staff with the billing-settings permission, turns on Read authorization letters with AI at the top of Billing → Operations → Prior Auths: “Adds Scan authorization letter to each patient’s Prior Auth tab.” Turning it off later keeps the letters already read in the chart.
-
Click
Scan authorization letter. It sits next toAdd authorizationonce the patient has an insurance policy. Read an authorization letter opens:Upload a photo or PDF(a phone photo works, up to 15 MB), or choose a photo or PDF already in the chart under Or choose a document already in the chart. An uploaded letter is also saved to the patient’s documents as Prior authorization letter. - Wait a few seconds while Hero reads it. It reads the first pages of the letter (up to six).
- Check the authorization. Check the authorization shows what Hero filled in: the insurance policy (with how it matched, for example “Matched to {payer} by the member ID on the letter.”), the authorization number, status, effective dates, units requested and approved, the authorized CPT/HCPCS and diagnosis codes, and notes with the approved units per code and the letter’s conditions. Fields marked in yellow (Check this against the letter.) were unclear or missing.
-
Click
Save authorization. Nothing is saved until you do. The letter’s pages stay attached to the authorization.
If Hero can’t read the letter, it says so (“Hero could not read this letter. Try again, or close this and type it in.”) and an uploaded letter is still kept in the patient’s documents.
From a fax. Once a fax is filed to a patient’s chart as a Prior Authorization document, its detail pane in the Fax inbox offers Add authorization from this fax under Open chart (letter reading must be on). It reads the fax’s pages straight away and opens the same check-and-save form; afterwards “Authorization saved. It is in the patient’s Prior Auth tab.”
Entered in error
An authorization added by mistake (a placeholder number, the wrong patient’s letter) is taken back with the ban icon next to its pencil, Entered in error. This replaces setting its status to Denied or Expired: an expired authorization can still be sent on claims for visits inside its dates.
- Click the ban icon. Mark as entered in error? explains: “It stays on {first name}’s list, marked ‘Entered in error’, but its number is never sent on a claim, its visits aren’t counted, and no expiry alert is raised for it. Its open alerts are closed. This can’t be undone; add a new authorization if you need one.”
- Say
What was wrong?(required), then clickMark entered in error.
The row moves to the bottom, struck through, with Marked entered in error on {date}: {reason}. Never sent on a claim. It can’t be edited, and it drops out of every bucket and count in the Prior Auths queue. Once any visit has used one of its units, the button is disabled (“… its number may be on a claim. Edit it instead.”): correct that authorization with the pencil.
Numbers Hero refuses
The authorization number is sent on claims, so Hero refuses words in its place: “Enter the authorization number the payer gave you. Words like ‘error’, ‘N/A’, ‘pending’ or ‘TBD’ are not authorization numbers, and the number is sent on claims.” Also refused: all zeros or X’s, punctuation only, and answers such as none, see letter or no auth required. Real numbers that only start with such a word (for example PEND-0042) are fine. Numbers are at most 50 characters. If the payer hasn’t given you a number yet, add the authorization when it does.
Which visits get the authorization number
Hero matches an authorization to a visit when the claim is built: the same policy, an Approved status (or Expired, when the visit falls inside its dates), the visit inside the effective dates, and, when the authorization lists Authorized CPT / HCPCS codes, a billed code on that list. “Only visits that bill one of these codes get this authorization number and use an approved unit.” Diagnoses never decide: Authorized diagnosis codes are for reference, and a visit coded with a different diagnosis still gets the number, with a warning on its claim, The authorization lists a different diagnosis. The warning never stops the claim.
Check visits on an authorization lists the patient’s recent and upcoming visits and says, for each, whether the number will be sent and why not, for example “Will be sent on the Oct 14 visit.”, “Will be sent on the {day} visit only if it bills {codes}.”, or “Won’t be sent on the {day} visit: the visit is after the end date.” It also warns when the approved visits are used up.
A replaced authorization expires quietly
When a newer approved or pending authorization on the same policy picks up where an ending one stops (and covers its codes), Hero sends no “expiring soon” or “expired” alert for the old one. At its end date it turns Expired with a note, Replaced by authorization {number}; this one ended {date}., and leaves the queue’s Expiring and Expired lists. An authorization that ends with no replacement still alerts as before.
More demographics: race, ethnicity, language, sexual orientation, gender identity and more
More demographics records the details that the standard Demographics card keeps to one plain answer: several races and ethnicities with detailed choices, a preferred language from the full list, sexual orientation and gender identity, a sex for clinical use, name prefix and suffix, previous names and addresses, tribal affiliation, occupation, phone types and date of death. Each answer is saved with a standard code, so it travels correctly when the record is shared with another practice or exported.
-
Turn it on.
A practice administrator opens
Admin → Additional Features, switches onMore demographics, and clicksSave Changes. It is off by default. The pronoun choices also needPatient pronounsturned on. -
Open it.
In Patient Information, choose
More demographicsunderPATIENT(or link to it with?section=more-demographics). It shows four cards:Identity,Background,Life, work and contact, andPrevious names and addresses. A question nobody has answered readsNot recorded. -
Click
Edit. The formEdit more demographicsreplaces the cards, withCancelandSaveat the top. Pick answers from the chips and search boxes (see the table), thenSave. -
Add previous names and addresses.
These save on their own, without
Edit.Add previous nameasks for a first and last name and theKind of name(Previous name,Name at birth / maiden name, orNickname), thenAdd name.Add previous addressasks for the street, city, state and ZIP, thenAdd address. The bin icon on a row removes it.
| Card | Question | Choices |
|---|---|---|
Identity | Name to use, Name prefix, Name suffix | Free text (for example Dr., Jr. or III). |
Sex | Female, Male, Don't know, Prefer not to say. | |
Gender identity | Man or boy, Woman or girl, Transgender man / trans man, Transgender woman / trans woman, Non-binary or genderqueer, Another identity (then type it In the patient’s words), Prefer not to say. | |
Sexual orientation | Straight or heterosexual, Lesbian, gay or homosexual, Bisexual, Something else (then type it in the patient’s words), Don't know, Prefer not to say. | |
Sex for clinical use (reference ranges and settings) | Use female-typical settings and ranges, Use male-typical settings and ranges, Use specified settings (explain in the comment), Unknown, with an optional comment. | |
Pronouns | Only with Patient pronouns on. she/her, he/him, they/them, Other pronouns (then type them, for example ze/zir), Prefer not to say. You can pick more than one. | |
Background | Race | Search (for example Cherokee, Filipino or White) and choose every race that applies. Detailed choices are grouped under the five main categories. Also Prefer not to say and Don't know. |
Ethnicity | Search (for example Puerto Rican or Not Hispanic); several allowed. Also Prefer not to say and Don't know. | |
Preferred language | Search any language, or Prefer not to say. | |
Tribal affiliation | Search federally recognized tribes, then tick Enrolled member if it applies. | |
Life, work and contact | Occupation, Industry, Primary phone type, Secondary phone type, Date of death | Occupation and industry are free text; each phone type is Mobile, Home, or Work. |
Prefer not to say means the patient was asked and declined to answer. It replaces any other choice for that question, and picking a choice replaces it.
Who can use it
- Anyone who can open Patient Information sees the tab once the practice turns it on.
Edit, adding and removing previous names and addresses: physicians, administrators, and staff withpatient.manage. Everyone else reads it.
How it fits with Demographics
- Saving also fills in the matching single answers on Demographics (sex, gender identity, preferred language, and pronouns).
- If someone later changes one of those single answers somewhere else (the Demographics form, the patient portal, an import), that newer answer wins, and More demographics shows it with
(from the single-answer field)until you edit it here again. - Turning the feature off hides the tab; nothing is deleted.
| You see | What to do |
|---|---|
| “Someone else changed these demographics. Cancel and edit again to see their changes.” | Another person saved while you were editing; your changes were not saved. Click Cancel, then Edit again and redo them. |
| “More demographics could not load. Close and reopen the patient to try again.” | Close Patient Information and open it again. |
No More demographics tab | The feature is off for your practice. Ask a practice administrator to turn it on in Admin → Additional Features. |
Keep a list of the patient’s implanted devices
Pacemakers, joint replacements, stents, cochlear implants: Implantable devices lists what the patient has implanted. You scan or paste the device’s UDI (the barcode on the device label or implant card), Hero reads the device ID, lot, serial number and dates from it, and fills in the brand, model, maker, MRI safety and latex information from the FDA device database.
-
Turn it on.
In
Admin → Additional Features, switch onImplantable devicesand clickSave Changes. It is off by default. -
Open the list.
In Patient Information, choose
Implantable devicesunderPATIENT. In the vertical chart layout the same list is anImplantable devicessection in the patient panel, with a count of active devices. Each row shows the device name, the maker and model, and chips such asMRI: MR ConditionalorContains latex; click a row for every detail. -
Add a device.
Click
Add device. InScan or paste the device's UDI, scan the barcode (a scanner fills it in and looks it up) or paste the whole UDI and clickLook up(or press Enter). -
Check what Hero read.
The preview is headed with the device name and lists
Device ID (DI),Lot,Serial,Expires,Made,Issuer, the description,MRI safetyandNatural rubber latex. Add anImplant date (optional), then clickAdd device. -
Mark a device inactive when it is removed.
Mark inactiveon a row keeps it on record but takes it off the active list;Mark activeundoes it.Show all devicesincludes inactive ones;Show active devices onlygoes back.
Not found in the FDA device database (“You can still add it with the details read from the UDI.”), or FDA device details unavailable when the database could not be reached. You can still add the device; only the details read from the UDI itself are saved.| You see | What it means and what to do |
|---|---|
| “This does not look like a UDI. Scan the device barcode or paste the whole UDI.” | Only part of the barcode was entered, or it was not a UDI. Scan again or paste the complete text from the implant card. |
| “This device is already on the patient's list.” | The same device is already recorded. Find it in the list (try Show all devices). |
Add device is greyed out | “Adding devices needs permission to edit the problem list.” Ask an administrator for problem_list.manage (the Medical Assistant and Nurse presets have it). |
No active implanted devices. | Nothing active is recorded; inactive devices are behind Show all devices. |
Physicians and administrators can add devices and change their status. Staff need patient.view to see the list and problem_list.manage to add or change devices. Turning the feature off hides the list; nothing is deleted.
Record the patient’s goals, health concerns and health status
Goals & health concerns keeps three short lists the care team updates over time: what worries the patient or the team (health concerns), what the patient is working toward (goals), and coded answers about functional, disability, cognitive and pregnancy status (health status). Positive answers on a social needs screener can add concerns and goals here in one click (see Questionnaires).
-
Turn it on.
In
Admin → Additional Features, switch onGoals, health concerns and health statusand clickSave Changes. It is off by default. -
Open it.
In Patient Information, choose
Goals & health concernsunderPATIENT. In the vertical chart layout it is also a section in the patient panel; its count is the open concerns and goals. -
Add a health concern.
Add concernopensHealth concern(for example Worried about falls at home); clickAdd concernto save.Resolvecloses one andReopenbrings it back; resolved concerns hide behindShow resolved concerns (N). -
Add a goal.
Add goalasks for theGoal(for example Walk 30 minutes, 5 days a week),Whose goal?(Patient's own goalorSet with the clinician), an optionalTarget date, and, when there are active concerns,For which concern? (optional). Each goal’s status menu offersProposed,Active,On hold,CompletedandCancelled; completed and cancelled goals hide behindShow finished goals (N). -
Record health status.
Record health statusasks for theArea, then a question and its answer, and saves withSave. The newest answer to each question shows;Show earlier answers (N)lists the history with dates.
| Area | Questions | Answers |
|---|---|---|
Functional status | Functional status | Walks independently, Bathes independently, Feeds self independently, Uses the toilet independently, or Describe it in your words. |
Disability status | Has a disability; Deaf or serious difficulty hearing; Blind or serious difficulty seeing, even with glasses; Serious difficulty concentrating, remembering or making decisions; Serious difficulty walking or climbing stairs; Difficulty dressing or bathing; Difficulty doing errands alone | Yes or No. |
Mental and cognitive status | Cognitive function | Normal cognition, Impaired cognition, or Describe it. |
Pregnancy status | Pregnancy status; Pregnancy intention in the next year | Pregnant / Not pregnant; Wants to become pregnant, No desire to become pregnant, Ambivalent about becoming pregnant, Not sure of desire to become pregnant. Both also offer Don't know. |
- Chips.
Social needmarks a concern or goal that came from a social needs screener;Patient's goalmarks a goal the patient set. - Entered by mistake? The
×on a row,Remove (entered in error), takes it off the list. - Who can do what. Physicians and administrators can add and change entries. Staff need
patient.viewto see the section andproblem_list.manageto add or change entries; without it the add links are greyed out with “Adding needs permission to edit the problem list.” - What it does not do. Adding a concern or goal does not add a diagnosis to the problem list; record diagnoses there as usual (see Problems & allergies).
Need help? Email support@heroemr.com.